When Screens Replace Connection: Impact on Children’s Brains
Posted: August 31, 2026 Filed under: ADHD, attention, behavior, cellphone, computer, emotions, Evolutionary perspective, Exercise/movement, healing, health, laptops, lifestyle, neurofeedback, screen fatigue, techstress, Uncategorized | Tags: infant development, neurodevelopment, screeen trauma, screen addiction, serve and return, snesory deprivation, social engagement, synesthesia, touch 1 CommentErik Peper, PhD, BCBa, Stoyan Vezenkov, PhDb, Violeta Manolovab, Lauren Mason, PhDc and Richard Harvey, PhDd
a BiofeedbackHealth, Berkeley, CA; b Center for Applied Neuroscience Vezenkov, Sofia, Bulgaria; c Mason-White Consulting, La Mesa, CA, USA; d San Francisco State University, San Francisco, CA, USA

Why are top tech CEOs strictly limiting their own children’s screen time while digital devices increasingly dominate classrooms and homes? In this latest post, When Screens Replace Connection: The Impact on Children’s Brains, we examine the physiological realities behind the growing mental-health challenges facing young people. We explore how excessive screen exposure may contribute to traits associated with ASD, ADHD, and emotional dysregulation, including through mechanisms such as “screen-induced dysregulation” and the erosion of vital “serve-and-return” interactions between children and caregivers.
Drawing on psychophysiological research, the article investigates how digital media can disrupt the human “social engagement system.” When face-to-face eye contact, vocal prosody, physical touch, movement, and responsive interaction are replaced by rapid 2D stimulation, developing systems involved in attention, attachment, and stress regulation may be affected.
It includes practical, evidence-based strategies for families, educators, and communities to restore balance through embodied connection, shared presence, movement, and time in nature. Rather than rejecting technology altogether, we advocate for more intentional use: fewer dependency-forming screens and more opportunities for responsive caregiving and real-world connection. The blog asks an essential question: Are we giving children more digital stimulation than human connection—and what might they be losing as a result?
*********************************
“So, your kids must love the iPad?” I asked Mr. Jobs, trying to change the subject. The company’s first tablet was just hitting the shelves. “They haven’t used it,” he told me. “We limit how much technology our kids use at home” (Bilton, 2014).
“Peter Thiel and other tech billionaires are publicly shielding their children from the products that made them rich” (Quiroz-Gutierrez, 2026).
Many of us are aware that something has shifted in the way we live, learn, and relate to one another. Screens—once tools of convenience—have become our primary portals for information, education, and social connection. Yet this shift comes with an unintended cost. The social psychologist Jonathan Haidt (2024) compellingly documents in his book, The Anxious Generation, that the rapid rise in screen use, especially social media content, parallels a striking decline in the self-reported mental health of young people (Haidt, 2024).
Beginning in the early 2000s, general rates of anxiety, depression, loneliness, and self-harm among adolescents have increased (Haidt, 2022). The trend did not start with the COVID-19 pandemic; rather, it preceded it by more than a decade. Facebook was launched in 2004, and the iPhone—ushering in the era of constant connectivity—arrived in 2007. Social media content combined with omnipresent technological innovations fundamentally reshaped how people, and especially young people experience the world: less face-to-face interaction, increasingly curated online identities, as well as a constant stream of social comparisons and forms of stimulation aimed at engaging developing brains (Swingle, 2019).
From a psychophysiological perspective, human beings evolved to regulate physical stress along with their emotional reactions without social media content. Instead the human ‘social engagement system’ linking heart, lungs and facial expressions (e.g. Ventral Vagal Complex) (Porges, 2011) along with direct social contact that includes eye gaze, touch, and shared presence regulate stress and emotional reactions such as release of hormones (e.g. vasopressin and oxytocin) (Eckstein, Mamaev, Ditzen, & Sailer, 2020; Atzil et al., 2018). When ‘social engagement’ behaviors are replaced by screen-mediated interactions, the body loses key cues for safety and connection (Haidt, 2022). The result can be a subtle but chronic activation of stress responses, contributing to emotional dysregulation, sleep disruption, reduced resilience, and an increase in serious psychologic distress, depression and suicidal thoughts, as shown in Figure 1 (Braghieri et al, 2022).
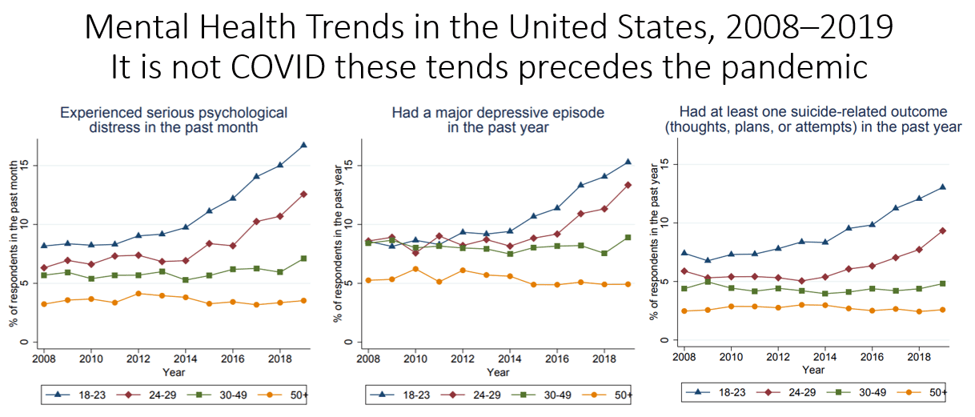
Figure 1. Mental health trends in the United States by age group in 2008–2019. The data come from the National Survey on Drug Use and Health. From: Braghieri, L., Levy, R., & Makarin, A. (2022). Social media and mental health. American Economic Review, 112(11), 3660–3693. https://doi.org/10.1257/aer.20211218
As screens become more prevalent and are increasingly incorporated into TK–12 education, with some municipalities enrolling children as young as 3.5 years of age, the promise of improved social engagement learning often fails to be realized. There is a parallel in reduced levels of intellectual attainment. For most students—outside of small groups who already perform at very high levels—math and reading scores have steadily declined since the introduction of social media content post COVID-2019 (Kus, 2025). In the United States, math scores are at their lowest levels in decades, according to the National Assessment of Educational Progress (NAEP). There was also a meaningful decline in overall science scores for 8th graders, with almost 40% of students below a ‘basic’ level of proficiency and a similar decline in math and reading scores for 12th graders in 2024 compared to 2019 representing what has been called the largest achievement gap in decades (NAEP, 2022; Harris, 2025),.
The findings related to deficits of social engagement and academic achievement do not mean that technology use is inherently harmful. Rather, they highlight a mismatch between our biological needs and our digital habits of engaging with dependency-forming content delivered by technology. Just as we learned to balance nutrition, movement, and rest for our well-being, we now face the challenge of consciously shaping our relationship with screens (Peper et al., 2020). Reintroducing embodied experiences— movement and dance, real-world social interactions, and time spent with others in nature—can help restore physiological balance and emotional flourishing by amplifying the social engagement system which evolved over millennia.
Although some have suggested that screen addiction may be overestimated (Anderson & Wood, 2025), many people report concern about the effects on young adults from exposure to digital dependency-forming content, this content delivered on screens and rapid digital displays may be even more harmful to infants and toddlers (Amirthalingam, & Khera, 2024; Reinecke, Gilbert, & Eden, 2022). The brains of young children are still developing and forming new neural connections and pathways in response to these ‘digital-engagement’ stimuli. There are two major risk factors:
- Caregivers being physically present but not attending to or communicating with the infant or toddler, and
- The remodeling of infants’ and toddlers’ brains through exposure to screens and their content.
- Caregivers being physically present but not attending to or communicating with the infant or toddler
Being physically nearby a child however attending to content on a screen rather than attending to the infant or toddler results in potential for experiencing feeling left out, ignored or abandoned and misses opportunities for personal, dynamic, interactive social feedback. Analogously, there may be a process that is similar for college students who report feeling neglected when they are engaged in a conversation that becomes interrupted by a phone notification (Peper & Harvey, 2018).
Infant development and communication are a dyadic feedback process (e.g., behavioral and neural synchronization or coupling; the “Serve and Return” Framework) which is essential for healthy brain architecture in which the caregiver and infant respond to each other rather than to digital content (Carozza & Leong, 2021; Ilyka, Johnson & Lloyd-Fox, 2021; Theyer & Wijeakumar, 2025). Because brains continue to mature for at least two or more decades, college students are likely also benefitting from increased social engagement rather than digital media engagement.
For example, dynamic social engagement is often studied through the lens of serve-and-return interactions (Chen et al., 2023; Komanchuk et al., 2023). If communication pathways are not activated, then the biological foundation for social and emotional skills may not develop fully (Shonkoff & Phillips, 2000). Infants and young children may learn that their needs are not consistently met, leading to “avoidant” or “disorganized” attachment styles. This can manifest later in life as difficulty trusting others or difficulty regulating one’s own emotions (Gunnar & Quevedo, 2007). Spoken languages and social cognitions are learned through mirroring and feedback loops. Without active participation during language acquisition—when babies learn the rhythm of conversation and the meaning of sounds by watching their caregivers’ responses—their vocabulary growth and verbal communication are often significantly delayed. These children may also lack social understanding as they can struggle to interpret social cues or develop empathy later on (Kuhl, 2007; National Scientific Council on the Developing Child, 2012; National Scientific Council on the Developing Child, 2026).
When a caregiver does not respond to the subtleties of the infant’s communication, the infant may be unable to learn effectively and may also feel frustrated. The developmental harm of inattention while physically present has been graphically shown by the research of Dr. Edward Tronick in the Still Face Experiment, as demonstrated in the following two videos (Still face with mother: https://www.youtube.com/watch?v=YTTSXc6sARg ; Still face with dad: https://www.youtube.com/watch?v=7Pcr1Rmr1rM(Tronick, 2007; Weinberg, et al., 2008).
The extreme harm of neglect along with lack of social engagement including non-verbal feedback has previously been demonstrated in the research by Harry Harlow’s 1950s–1960s experiments on rhesus monkeys, who were placed with wire or cloth surrogate mothers rather than real mothers. These studies showed that infant attachment is initially and primarily driven by comfort and warmth interactions. More importantly, adult monkeys, when raised in isolation or with artificial mothers, were socially incompetent, often unable to interact or mate, and exhibited severe behavioral issues (Harlow et al., 1965).
Similar findings have been observed with human infants. For example, following the political transfer and fall of Romanian leader Nicolae Ceaușescu in 1989, it was revealed that over 100,000 children in Romanian institutions faced extreme physical, cognitive, and emotional neglect. Confined to cribs with minimal human contact, these babies suffered severe developmental delays, structural brain changes, and profound attachment issues, often exhibiting self-stimulatory behaviors (Nelson et al., 2023).
It is important to acknowledge that parents and caregivers do not typically go to the extremes seen in Harlow’s rhesus monkeys or the neglected Romanian infants; however, implicit neglect can occur when the caregiver is not attentive to their children and are instead absorbed in their screen content. Engaging in dynamic serve-and-return interactions with the infant reduces a risk factor for healthy infant development. The solution is obvious: attend to and interact with people, especially infants and young children in a serve-and-return style. When interacting with infants, be present:
- Put your cellphone away and engage dynamically with the infant and children.
- Do not give a screen to an infant as a distraction. Instead, play with and attend to the child while sharing responsibilities as primary caregivers with others in a household or community.
2. The remodeling of infants’ and toddlers’ brains through exposure to screens
Over the past decade, through their clinical and research work at the Vezenkov Center for Applied Neuroscience in Sofia and Weinheim, Drs. Vezenkov and Manolova have arrived at a position that may sound strong at first hearing but which, in our view, is now unavoidable: in a substantial subgroup of young children presenting with severe disorders with features that are like autism spectrum disorder (ASD-like), Attention Deficit Hyper-Activity Disorder (ADHD-like), Oppositional Defiant Disorder (ODD-like), or Pervasive Developmental Disorder (PDD-like) features, there are no observations of a primary neurodevelopmental disorder. Rather there is a clinical signature of early screen addiction (Vezenkov & Manolova, 2025a), screen trauma (Manolova & Vezenkov, 2025a), and may be called ‘reversed development’ (Manolova & Vezenkov, 2025c). Importantly, treating these children for screen addiction and screen trauma, the clinical picture changes, and in many cases the original ASD or ADHD diagnosis is lifted. This is a clinical hypothesis derived from repeated observations and consistent therapeutic outcomes — offered as a framework that is testable, falsifiable, and one that can be described as clinically urgent.
Screen addiction is not screen time
The first conceptual step is to separate screen addiction from screen time. Severe early screen addiction is not simply indexed by hours in front of a device. Rather, (a) compulsive seeking of high-intensity, low-social-density visual or sensory stimulation combined with (b) cycles of soothing and crash as well as (c) a shift of interest away from human faces toward objects, colors, shapes, and repetitive sensory patterns along with (d) a collapse of joint attention and eye-to-eye play. Removing the device produces withdrawal — crying, hysteria, aggression, or shutdown — not because the child is willful, but because what has been removed is the child’s regulatory prosthesis.
Three learning systems (e.g. identified as ‘System 0, 1 and 2 described below) frame and organize behavior during clinical care. Drawing on Kahneman, System 2 is the slow human system: language, reflective thinking, social context, values, and the capacity to delay action (Kahneman, 2011; Khalil & Brüne, 2025). System 1 is the fast system: automatisms, immediate reward, and reinforcement through the dopaminergic reward circuitry. A third is System 0, drawing on Rizzolatti’s work on mirror neurons — the biological bridge between “I see” and “I do” in human encounters (Rizzolatti & Sinigaglia, 2016). In healthy development, the three systems work together. In screen-dominant development, System 1 wins and closes an addiction loop, System 2 stalls, and System 0 is hacked: human mirroring is replaced by immersion in the object world. Mirror neurons are not damaged in these children; they are retuned, away from faces and toward screens.
The developing brain: sensitive windows and the arrest of pruning
The first six years of life are a period of intense synaptogenesis, reorganization, and myelination. The brain calibrates itself to the environment — deciding which sounds are meaningful, which faces matter, and which rhythms feel safe. The dominant cortical frequency accelerates from delta in the newborn to roughly 10 Hz at age nine, at approximately one hertz per year (Freschi et al., 2022; Wilkinson et al., 2024). Behind this gradient lies a series of sensitive windows in which the child’s experiences shape what the brain becomes.
When the environment is rich in human movement, touch, eye contact, prosody, and rhythm, the brain prunes excess connections and strengthens those that support attention, language, and self-regulation. When the environment is dominated by fast, repetitive audiovisual stimulation, the brain strengthens those pathways instead. The auditory and visual sensory systems become hypertrophic at the expense of executive motor loops, affect, and speech, producing the splitting and fragmentation of cortical function described below.
A second key point is pruning. The hypermnesic period around 18–36 months should normally be followed by reorganization and selection (Gonzalez-Escamilla et al., 2018; Sakai, 2020). In severe early screen addiction, this process does not unfold normally. Development does not simply slow; it freezes. Children enter what we term addictive homeostasis — a state actively defended against change. In clinical settings, we observe twelve-year-olds who have not yet shed their primary teeth, as well as delayed acquisition of bowel and bladder control. The child may accumulate fragments — words, scripts, colors, routines — without integrating them into a language system or socially meaningful behavior. The result is not delay but a traumatization and deformation of development that cannot self-correct without specialized intervention.
Biomarkers: the physiological signature of screen addiction
If this framework is to be taken seriously, it must leave physiological traces. In our work it does so consistently across several hundred qEEG and HRV recordings in children, adolescents, and adults (Vezenkov & Manolova, 2025a). We observe four broad classes of biomarkers in early screen addiction:
- Altered cortical activity in opposing directions across networks. Some leads show slowing — theta and/or alpha peaks in central, frontal, and frontopolar sites — while others show acceleration, with SMR, beta1, or beta2 bursts in central, parietal, and occipital sites. Similar findings have also been reported by Law et al. (2023). The two patterns coexist and produce what we call cortical splitting. Other researchers have observed similar effects in which EEG results suggested a higher connectivity in theta vs. beta bands in the screen group, but not in the control group (Zivan et al., 2019). Their results support the negative relationship between screen exposure and attention-related patterns generated from EEG in typically developing preschool children.
- Reversed hemispheric asymmetry, with dominant alpha or theta rhythms in the left hemisphere — the inverse of the typical pattern.
- Functional fragmentation: each cortical site behaves as if running on its own clock, with frequency differences between leads often greater than 1.5 Hz. High local coherence coexists with weak long-range coherence, indicating disrupted connectivity. This pattern is most pronounced when onset of screen exposure is between 0 and 3 years.
- Autonomic dysregulation, expressed in HRV as sympathicotonia, dorsal vagotonia, or unstable mixed patterns — rather than the ventral vagal balance associated with secure attachment and social engagement (Porges, 2011; Pankova et al., 2021). In the clinic it has been observed that the age of onset of severe screen exposure leaves a signature in the dominant cortical frequencies. Onset before 18 months tends to be associated with peaks at 2–3 Hz; 18–30 months with 3–4 Hz; 30–36 months with 4–5 Hz. This remains a practice-derived hypothesis rather than an established rule, but it aligns strikingly with parental histories. The biomarker profile does not, on its own, constitute a diagnosis. Together, however, these markers outline a recognizable physiological spectrum from nonverbal dorsal-freeze states to verbal, high-functioning children with autistic traits.
Screen trauma: why detox alone is not enough
Parents and clinicians often assume that simply removing screens will return the child to a typical developmental trajectory. In many cases it does not. Even after weeks or months of complete digital detox, the child remains anchored in infantile, sensory-dominant patterns. During clinical work, we have come to call this state screen trauma (Manolova & Vezenkov, 2025a).
Screen trauma is what state-dependent learning looks like when the state in which learning was acquired was screen-induced dysregulation. The anchors are physiological: persistent primitive reflexes, atypical vestibular and postural patterns, sensory disintegration, cortical fragmentation, and a vision-dominant mode of processing. Functioning is tuned to stereotyped, repetitive stimuli — which the world outside the screen does not provide. Removing the screen removes the trigger but leaves the architecture in place. Recovery requires therapeutic work that lifts these anchors sequentially.
Pathological screen-induced reflexes: SIPVR and SIPECR
Two clinical reflexes have been identified that serve as among the most useful sensitive markers for screen trauma. Both are present in screen-addicted children and absent in typically developing peers, and both resolve with therapy and re-emerge with screen re-exposure, confirming their conditioned, environmental nature:
The Screen-Induced Pathological Vestibular Reflex (SIPVR) is elicited by a controlled backward tilt or inversion of the child (Vezenkov & Manolova, 2025c). An affected child shows arching backward, reaching out to grasp support, trembling and panic, full-body muscular stupor while desperately seeking support, and intense fear of falling — disproportionate to the postural challenge. In typically developing children, the same maneuver elicits play, laughter, or rapid adaptation. The reflex is highly sensitive in children up to age twelve. The SIPVR can be seen in the following video: https://youtu.be/_9PKtanDClU?si=KNicSRlDqEAutBQihttps://youtu.be/_9PKtanDClU?si=KNicSRlDqEAutBQ
The Screen-Induced Pathological Eye-Covering Reflex (SIPECR) is elicited by briefly covering the child’s eyes with hands, a mask, or a cloth (Vezenkov & Manolova, 2025d). Affected children respond with intense panic, screaming, agitation, and in severe cases aggression toward caregivers or self-injurious behavior such as head-banging. Episodes can persist for ten to thirty minutes and do not de-escalate while the visual occlusion remains. The SIPECR reflex was observed in 275 of 285 children evaluated at our center (96.5%). Unlike a startle reflex, it is provoked by the removal rather than the onset of stimulation; unlike nyctophobia, it persists when the child is enclosed under a translucent cloth in the presence of a caregiver, demonstrating that the trigger is not darkness itself but the loss of familiar visual cues. SIPECR is not observed in typical development and, alongside SIPVR, helps differentiate screen trauma from primary neurodevelopmental conditions.
Sensory disintegration versus sensory deprivation
These reflexes acquire their full meaning within a broader framework we have proposed for distinguishing the screen-induced ASD-like phenotype from primary visual impairment (Vezenkov & Manolova, 2025e). Both groups can present with stereotypies, social withdrawal, atypical orienting, and spatial insecurity, yet the underlying sensory architectures are opposite.
In early blindness, the core problem is sensory deprivation: visual input is absent, and the brain compensates by re-weighting toward vestibular and proprioceptive channels. Stereotypic movements — the so-called “blindisms” — function here as self-calibration, generating the bodily anchors that vision would normally provide. In screen-induced ASD-like states, the core problem is sensory disintegration: visual input is present but pathologically dominant — what we describe as “2D-locked” vision — and actively suppresses vestibular and proprioceptive feedback. The child’s sense of safety, arousal regulation, and attention all run through a single hyper-dominant channel. This explains why SIPVR and SIPECR appear in this group and not in blindness: when vision is suppressed (eyes covered) or contradicted (body inverted), the child’s only working regulatory channel is disabled, producing existential panic. It also explains why post-rotatory nystagmus is often absent in these children despite hours of self-induced spinning — the dominant visual system inhibits the vestibular response that should follow. Critically, while deprivation requires lifelong adaptation, disintegration is environmentally induced and, in most cases, reversible.
Screen-induced synesthesia and cue-dependent behavior
A further consequence of disrupted synaptic pruning during periods of audiovisual hyperstimulation is the emergence of screen-induced synesthesia and cue-dependent behavior (Manolova & Vezenkov, 2025b). Where pruning would normally eliminate weak cross-modal connections, persistent overstimulation preserves them as parasitic links between sensory modalities — a child sweats profusely on seeing a dog, scratches on seeing a particular color, perceives the mother as “blue” and the father as “green” and avoids “green people,” or arranges objects in fixed color-coded matrices and self-injures if the arrangement is disturbed. Modern animation and games — with their tightly synchronized audiovisual markers and the well-described Game Transfer Phenomena — appear to actively cultivate such cross-modal anchoring as an immersive design feature. In the developing brain, these become persistent neurosensory dependencies.
The clinical counterpart is cue-dependent behavior, in which physiological functions become locked to specific external stimuli. Children may eat only in the presence of a particular cartoon, urinate only when seeing a yellow image, defecate only while singing a specific theme song, or fall asleep only with a light on or a swing in motion. This is not stubbornness, nor classical ASD rigidity — it is a neurological inability to initiate the program without its acquired sensory key. In a quasi-experimental observation across our three index cases, both the synesthetic responses and the cue-dependent behaviors disappeared during five months of comprehensive screen-addiction therapy, supporting their environmental origin and reversibility.
Reversed development and the question of recovery
‘Reversed development’ refers to a condition in which evolutionarily older survival programs come to dominate higher human regulatory systems — not as fate, but as strategy. Within the Unified Trauma–Addiction Functioning (UTAF) model, this corresponds to the inversion of the normal autonomic hierarchy into a “dark matryoshka,” in which the same regulatory layers — ventral vagal, sympathetic, dorsal vagal, and enteric — operate in mirrored form, oriented inward toward an intrauterine-like illusion of safety rather than outward toward human co-regulation (Manolova & Vezenkov, 2025c). Stereotyped movements, rigid ritualism, demand for predictability at any cost, withdrawal of gaze from people toward objects: these are not “non-human” features, they are deeply human defenses deployed when the social world has become too complex to navigate. Other people are no longer experienced as partners in development but as instruments for maintaining a narrow, pathological homeostasis.
The dark paradox is that this homeostasis confers real short-term advantages — reduced uncertainty, lower complexity, immediate predictability, protection from overload. That is precisely why it is so stable, and why parents often describe their children as having “superpowers”: rare illness, hypermnesia, extraordinary visual recall, remarkable consistency within narrow routines. What is sometimes celebrated as neurodiversity may, in these cases, reflect the stabilization of older, narrower modes of functioning — efficient in their own way, but costly in relation to human reciprocity, language, and growth.
The clinically important news, however, is that these disturbances are functional, reversible, modifiable, and in many cases compatible with full recovery — provided that therapy addresses the whole system: total digital detox; containment of the older defensive programs; sequential lifting of developmental anchors including SIPVR and SIPECR, with parallel resolution of induced synesthesias and cue-dependent behaviors; sensory restart and re-engagement of cortical activity; reconnection of the child with therapist and parent; language development in social context; and parallel therapy with the parents. No child recovery occurs without therapeutic work with the parents.
Foundational papers have been peer-reviewed on this framework — biomarkers, the neurobiology of recovery, screen trauma, the SIPVR, the SIPECR, screen-induced synesthesia, the unified trauma–addiction functioning model, and the sensory disintegration framework — across the first issues of the journal Nootism (https://www.nootism.eu/), where the case reports and quantitative data underlying the claims above can be examined in detail.
Across the globe, there is a growing awareness that social media and other dependency-forming content delivered on screens are detrimental for young people’s development. Numerous countries have already implemented or are currently prioritizing regulations to limit screen time in young people.
China in 2019 began to set time limits and curfew on gaming. By 2021, the maximum limit on gaming was set to 3 hours/week. By 2023, they limited digital device and cellphone use for children less than 8 years of age to 40 minutes per day, children less than 16 to 1 hour per day and those aged 18 to a maximum of 2 hours per day on the phone, and no access to internet or mobile devices from 22:00 to 6:00 am (Soo, 2023).
Sweden in 2026 is reversing its “digital-first” education policy, shifting back to traditional learning tools to combat declining literacy and attention spans. They are aiming to ban smartphones in schools by August 2026, limiting screen time in favor of paper, pens and books (Champion-Osselin, 2025.
England in 2026 also banned mobile phone use in schools, and in the UK, new guidance recommends that children under five should spend no more than one hour on screens each day and should refrain from watching any fast-paced, social-media style videos whatsoever (Editorial, 2026).
Denmark in 2025 plans to ban social media for children under the age of 15 (Hubenko, 2025)..
Australia in 2025 legislated a ban that makes it unlawful for social media platforms to allow users under the age of 16 to maintain accounts (UN, 2025, December 10).
USA in 2026 numerous local cities or states are implementing bans on cell phones and screen usage. New Jersey prohibits cellphones and internet enabled devices throughout the school day and Los Angeles is the first US school district to limit classroom screen time (NJSBA, 2026; Ede-Osifo, 2026).
Given the lobbying power of technology and media companies, combined with the USA constitutional right for free speech, it is unlikely that screen time will be limited at the national level (Kang, 2024). With no regulations, the USA will continue to allow screen and digital media to harm children. This is not the first time that a lack of government oversight has perpetuated harm: the failure to ban smoking despite overwhelming negative impacts also persists (Action on Smoking and Health, 2020). Thus, screentime guidelines and regulations must be developed and implemented at the local level (school boards, cities, counties, or state) and within family and social groups.
Recommendations
The international landscape surveyed above shows growing recognition that screen exposure in childhood is a public-health concern, but national policies remain a patchwork — varying widely across age thresholds, scope (school, social media, gaming), and enforcement. The recommendations we offer below reflect the convergence of three streams: international policy precedent, the psychophysiological literature on stress and attachment, and our own clinical experience with several hundred children across the screen-addiction and screen-trauma spectrum (Swingle, 2016; Peper et al., 2020; Petrov et al., 2025; Novoli et al., 2025).
A core distinction underpins everything that follows. We differentiate between euthymic screen time (EST) and hedonic screen time (HST). EST refers to screen engagement that supports cognitive activity, psycho-emotional balance, and autonomic stability without leading to compulsive use — a focused educational task with a defined endpoint, used in social context. HST refers to screen engagement aimed at pleasure, emotional regulation, or stress avoidance — animations, gaming, social media, short-form video, pornography, and gambling. HST is the form most strongly associated with the development of screen addiction and screen-induced trauma. The two are not interchangeable, and recommendations that conflate them — such as generic “two hours of screen time” rules — miss the mechanism that matters.
For families and caregivers.
Ages 0–3 years. No screen exposure of any kind. This is the period of most intense synaptogenesis, language acquisition, and attachment formation; it is also the developmental window in which screen exposure produces the most severe and least reversible damage we observe clinically. We agree with WHO guidance for children under two and extend it through age three (World Health Organization, 2019). Screens should not be used as pacifiers, feeding aids, or to occupy the child while the caregiver attends to something else.
Ages 3–9 years. Screen exposure is not necessary for typical development, and there is no evidence that screen use in this age band confers benefits that cannot be obtained through embodied alternatives — physical play, reading aloud, time in nature, music, drawing, and social interaction with adults and peers. We therefore recommend zero screen use as the default for this age range, with euthymic exceptions (educational, brief, supervised, in social context) reserved for genuine necessity.
Ages 9–12 years. Limited euthymic screen time may be carefully introduced — up to 2 hours per week in the presence of an adult, distributed across non-consecutive days. A feature film or documentary (excluding animations, VR, augmented reality, and short-form video) of up to 90 minutes once every two weeks may be permitted as supervised hedonic exposure. The principle is gradual, accompanied introduction rather than a sudden expansion.
Ages 12–18 years. Up to 5 hours per week of EST, with no more than 60 minutes on any single day; up to 2 hours per week of HST, again excluding animations, gaming, social media, pornography, and gambling. We support the legislative direction of Australia, France, and Spain in raising the minimum age for social media accounts and would set the threshold at 16 years of age minimum.
Ages 18+. EST can be largely unrestricted; HST should remain capped at roughly 3 hours per week, again excluding the high-risk categories where addictive functioning most readily develops.
Five practical principles apply across all age groups.
- Measure screen time in hours per week, not per day, to allow flexibility.
- Maintain at least two digital-fasting days per week; keep them flexible rather than fixed, to avoid building rigid screen-use rituals.
- No screen use at night, stopping at least two hours before sleep.
- Caregivers’ own screen use is part of the child’s environment — modelling matters, and a parent absorbed in a phone is, from the infant’s perspective, a Still Face.
- Screen access is not a child’s right but a developmental risk factor; it is the adults’ job to manage it.
For children with established screen addiction or screen trauma
The recommendations above are designed for children whose nervous systems have not yet been reorganized around screen-induced dysregulation. Once early screen addiction or screen trauma has formed — recognizable through the biomarkers, reflexes, and clinical patterns described in Section 2 — generic time limits no longer apply and may even be misleading. As little as fifteen minutes of daily exposure can be sufficient to reactivate established traumatic neural patterns (Petrova et al., 2025). At this point, the child requires:
- Objective clinical assessment of severity (qEEG, HRV, SIPVR/SIPECR screening, developmental and behavioral evaluation).
- Complete digital detox of at least two years, beginning immediately.
- Targeted therapy that lifts developmental anchors sequentially and rebuilds the regulatory hierarchy from below upward.
- Parallel therapeutic work with the parents, including assessment for parental screen addiction. There is no recovery in a child whose immediate environment continues to model and provide screen-based regulation.
This guidelines above are thought of as a clinical pathway, not only as a behavioral guideline, but also as a pathway that requires trained professionals.
For schools and educators
The empirical record on educational technology in early and primary education has not delivered on its promises — math and reading scores have declined while screen use in classrooms has risen, as the U.S. NAEP data and Sweden’s recent reversal of its “digital-first” education policy make plain. We therefore recommend:
- No personal mobile devices on school premises during the school day for children under 16, including breaks and recess. Storage policies (lockers, locked pouches, collected at entry) work better than “off but in pocket” rules; the policies in the Netherlands, Hungary, Brazil, and Belgium offer functional templates.
- No tablets or laptops in early childhood education (nursery, kindergarten) and minimal use in primary education, restricted to specific, time-bounded, teacher-supervised purposes.
- Pilot any educational technology with longitudinal evaluation before broad adoption — Finland’s approach of legislating limits in parallel with a nationwide impact study is the right template.
- Train educators to recognize signs of screen-induced dysregulation. The ASD-like, ADHD-like, and ODD-like presentations described in Section 2 are increasingly common in classrooms and increasingly attributable, in our clinical experience, to early screen exposure rather than to primary neurodevelopmental conditions.
For policymakers, public health, and society
A whole-of-government and whole-of-society approach is required. We propose five priorities:
- Treat screen exposure of children aged 0–3 as a child-safeguarding matter, not merely as a private parenting choice. Where parental behavior produces moderate to severe psycho-physical harm, child protection services and public-health authorities should have legal standing to intervene, on the same logic that already applies to other forms of caregiver-mediated harm. Taiwan’s 2015 legislation classifying excessive child screen use as a public-health violation, and the legal framework Australia introduced in 2024, point in this direction.
- Set 16 as a minimum age for social media accounts and short-form video platforms, with effective age verification — following the Australian, Spanish, and emerging Danish models.
- Require platforms to provide a verified “minor mode” with parental oversight, time caps, and night curfews, on the Chinese model — without endorsing the broader framework of state surveillance that accompanies it in that jurisdiction.
- Fund clinical and research infrastructure for the assessment and treatment of screen addiction and screen trauma, including training of biofeedback and neurofeedback clinicians and family-based therapy programs.
- Recognize screen addiction in adults — including parents and educators — as a risk factor for the children in their care and integrate brief screening into routine pediatric and family-health encounters.
The set of recommendations described are straight forward however not easy to implement, particularly because digital dependency is stubbornly reinforced for commercial reasons and therefore resistant to change. Legislators will be opposed by the platforms whose business models depend on engagement, and they will be uncomfortable for families and institutions that have organized daily life around screens. The relevant question is whether the harms documented across the international epidemiological, neuroscientific, and clinical literature — and assembled in this paper — are now sufficient enough to justify a proportionate response.
Additional recommended blogs
References
Action on Smoking and Health. (2020). Tobacco control in the United States: Failure to protect the right to health. Tobacco Prevention & Cessation, 6, 34. https://doi.org/10.18332/tpc/122543
Amirthalingam, J., & Khera, A. (2024). Understanding social media addiction: A deep dive. Cureus, 16(10), e72499. https://doi.org/10.7759/cureus.72499
Anderson, I. A., & Wood, W. (2025). Overestimates of social media addiction are common but costly. Scientific Reports, 15, 39388. https://doi.org/10.1038/s41598-025-27053-2
Atzil, S., Gao, W., Fradkin, I., & Barrett, L. F. (2018). Growing a social brain. Nature Human Behaviour, 2(9), 624–636. https://doi.org/10.1038/s41562-018-0384-6
Braghieri, L., Levy, R., & Makarin, A. (2022). Social media and mental health. American Economic Review, 112(11), 3660–3693. https://doi.org/10.1257/aer.20211218
Bilton, N. (2014, September 10). Steve Jobs was a low tech parent. The New York Times. Accessed April 27, 2026. https://www.nytimes.com/2014/09/11/fashion/steve-jobs-apple-was-a-low-tech-parent.html
Carozza, S., & Leong, V. (2021). The role of affectionate caregiver touch in early neurodevelopment and parent–infant interactional synchrony. Frontiers in Neuroscience, 14, 613378. https://doi.org/10.3389/fnins.2020.613378
Champion-Osselin, Y. (2025, August 2025). Screens In Classrooms? A Serious Swedish Debate Spreads Worldwide. Worldcrunch. Accessed April 27, 2026. https://worldcrunch.com/culture-society/sweden-phones-in-schools/
Chen, Y., Cabrera, N. J., & Reich, S. M. (2023). Mother–child and father–child “serve and return” interactions at 9 months: Associations with children’s language skills at 18 and 24 months. Infant Behavior and Development, 73, 101894. https://doi.org/10.1016/j.infbeh.2023.101894
Eckstein, M., Mamaev, I., Ditzen, B., & Sailer, U. (2020). Calming effects of touch in human, animal, and robotic interaction: Scientific state-of-the-art and technical advances. Frontiers in Psychiatry, 11, 555058. https://doi.org/10.3389/fpsyt.2020.555058
Ede-Osifo, U. (2026, April 22). Los Angeles school board votes to set limits on classroom screen time. The Guardian. Accessed April 27, 2026. https://www.theguardian.com/us-news/2026/apr/22/los-angeles-school-district-screen-time
Editorial. (2026, April 27). The Guardian view on screens in schools: big tech is finally under the microscope. The Guardian. Accessed April 27, 2026. https://www.theguardian.com/commentisfree/2026/apr/27/the-guardian-view-on-screens-in-schools-big-tech-is-finally-under-the-microscope?
Freschl, J., Azizi, L. A., Balboa, L., Kaldy, Z., & Blaser, E. (2022). The development of peak alpha frequency from infancy to adolescence and its role in visual temporal processing: A meta-analysis. Developmental Cognitive Neuroscience, 57, 101146. https://doi.org/10.1016/j.dcn.2022.101146
Gonzalez-Escamilla, G., Muthuraman, M., Chirumamilla, V. C., Vogt, J., & Groppa, S. (2018). Brain networks reorganization during maturation and healthy aging: Emphases for resilience. Frontiers in Psychiatry, 9, 601. https://doi.org/10.3389/fpsyt.2018.00601
Gunnar, M. R., & Quevedo, K. (2007). The neurobiology of stress and development. Annual Review of Psychology, 58, 145–173. https://doi.org/10.1146/annurev.psych.58.110405.085605
Haidt, J. (2022). Teen Mental Health Is Plummeting, and Social Media is a Major Contributing Cause, 117th Congress, (May 4, 2022) (Testimony of Testimony of Jonathan Haidt
Professor of Ethical Leadership, New York University – Stern School of Business
Before the Senate Judiciary Committee, Subcommittee on Technology, Privacy, and the Law.) https://www.judiciary.senate.gov/imo/media/doc/Haidt%20Testimony.pdf
Haidt, J. (2024). The Anxious Generation: How the Great Rewiring of Childhood Is Causing an Epidemic of Mental Illness. Penguin Press. https://www.amazon.com/Anxious-Generation-Rewiring-Childhood-Epidemic/dp/B0C9N2L56X
Harlow H. F., Dodsworth R. O., & Harlow M. K. (1965). Total social isolation in monkeys. Proceedings of the National Academy of Sciences of the United States of America. Retrieved from
https://www.ncbi.nlm.nih.gov/pmc/articles/PMC285801/pdf/pnas00159-0105.pdf
Harris, S. (2025). Nation’s Report Card Shows Declines in 8th-Grade Science and 12th-Grade Math and Reading; Last in a Series of Post-Pandemic NAEP Data. National Assessment Governing Board. Retrieved April 29, 2026. https://www.nagb.gov/news-and-events/news-releases/2025/declines-in-8th-grade-science-and-12th-grade-math-and-reading.html
Ilyka, D., Johnson, M. H., & Lloyd-Fox, S. (2021). Infant social interactions and brain development: A systematic review. Neuroscience & Biobehavioral Reviews, 130, 448–469. https://doi.org/10.1016/j.neubiorev.2021.09.001
Kahneman, D. (2011). Thinking Fast and Slow. Farrar, Straus and Giroux. https://www.amazon.com/Thinking-Fast-Slow-Daniel-Kahneman/dp/0374533555
Kang, C. (2024, October 7). The tech lobbying group helping to broaden the First Amendment’s reach. The New York Times, October 7, 2024. Retrieved May 6, 2026. https://www.nytimes.com/2024/10/07/technology/netchoice-free-speech-meta-google.html
Khalil, R., & Brüne, M. (2025). Adaptive decision-making “fast” and “slow”: A model of creative thinking. European Journal of Neuroscience, 61(5), e70024. https://doi.org/10.1111/ejn.70024
Komanchuk, J., Letourneau, N., Duffett-Leger, L., & Cameron, J. L. (2023). History of “serve and return” and a synthesis of the literature on its impacts on children’s health and development. Issues in Mental Health Nursing, 44(5), 406–417. https://doi.org/10.1080/01612840.2023.2192794
Kuhl, P. K. (2007). Is speech learning “gated” by the social brain? Developmental Science, 10(1), 110–120. https://doi.org/10.1111/j.1467-7687.2007.00572.x
Kuş, M. (2025). A meta-analysis of the impact of technology-related factors on students’ academic performance. Frontiers in Psychology, 16, 1524645. https://doi.org/10.3389/fpsyg.2025.1524645
Law, E. C., Han, M. X., Lai, Z., Lim, S., Ong, Z. Y., Ng, V., Gabard-Durnam, L. J., Wilkinson, C. L., Levin, A. R., Rifkin-Graboi, A., Daniel, L. M., Gluckman, P. D., Chong, Y. S., Meaney, M. J., & Nelson, C. A. (2023). Associations between infant screen use, electroencephalography markers, and cognitive outcomes. JAMA Pediatrics, 177(3), 311–318.
Manolova, V. R., & Vezenkov, S. R. (2025a). Screen trauma – Specifics of the disorder and therapy in adults and children. Nootism, 1(1), 37–51. https://doi.org/10.64441/nootism.2NCSC.3
Manolova, V. R., & Vezenkov, S. R. (2025b). Are screen-induced synesthesia and screen-induced cue-dependent behavior contributing factors in the misdiagnosis of ASD among children with screen addiction? Nootism, 1(3), 11–16. https://doi.org/10.64441/nootism.1.3.2
Manolova, V. R., & Vezenkov, S. R. (2025c). Unified trauma–addiction functioning model. Nootism, 1(4), 4–24. https://doi.org/10.64441/nootism.1.4.1
NAEP. (2022). 2022 Age 9 Long-Term Trend Reading and Mathematics Highlights Report. (2022). U.S. Department of Education, Institute of Education Sciences. Retrieved September 12, 2022, from https://www.nationsreportcard.gov/highlights/ltt/2022/.
National Scientific Council on the Developing Child. (2012). The Science of Neglect: The Persistent Absence of Responsive Care Disrupts the Developing Brain: Working Paper 12. https://developingchild.harvard.edu/wp-content/uploads/2024/10/The-Science-of-Neglect-The-Persistent-Absence-of-Responsive-Care-Disrupts-the-Developing-Brain.pdf
National Scientific Council on the Developing Child. (2026). Finding the Balance: Transforming How We Think About the Body’s Response to Stress in Early Childhood: Working paper 16. National Scientific Council on the Developing Child Harvard University. Retrieved April 29, 2026. https://developingchild.harvard.edu/wp-content/uploads/2026/04/HCDC_WP18_InBrief_R5C.pdf
Nelson, C. A., Fox, N. A., & Zeanah, C. H. (2023). Romania’s abandoned children: The effects of early profound psychosocial deprivation on the course of human development. Current Directions in Psychological Science, 32(6), 515–521. https://doi.org/10.1177/09637214231201079
NJSBA. (2026, January 13). Governor Murphy signs cell phone ban into law.
New Jersey School Boards Association. School Board Notes, ( XLIX)2. https://www.njsba.org/news-information/school-board-notes/governor-murphy-signs-cell-phone-ban-into-law/
Peper, E. & Harvey, R. (2018). Digital addiction: increased loneliness, depression, and anxiety. NeuroRegulation. 5(1),3–8. doi:10.15540/nr.5.1.3 http://www.neuroregulation.org/article/view/18189/11842
Peper, E., Harvey, R., & Faass, N. (2020). TechStress: How technology is hijacking our lives, strategies for coping and pragmatic ergonomics. North Atlantic Books. https://www.amazon.com/Beyond-Ergonomics-Prevent-Fatigue-Burnout/dp/158394768X
Petrov, P. P., Dimova, V. R., Manolova, V. R., & Vezenkov, S. R. (2025). Screen time and policy approaches to digital media use in nurseries, kindergartens, and schools worldwide: A critical analysis. Nootism, 1(2), 41–50. https://doi.org/10.64441/nootism.1.2.4
Petrova, S. N., Manolova, V. R., & Vezenkov, S. R. (2025). Reintroducing screens: Severe regression and symptom aggravation in children with ASD/screen addiction. Nootism, 1(1), 59–65. https://doi.org/10.64441/nootism.2NCSC.5
Porges, S. W. (2011). The polyvagal theory: Neurophysiological foundations of emotions, attachment, communication, and self-regulation. W. W. Norton. https://www.amazon.com/Polyvagal-Theory-Neurophysiological-Communication-Self-regulation/dp/0393707008
Quiroz-Gutierrez, M. (2026, February 21). Peter Thiel and other tech billionaires are publicly shielding their children from the products that made them rich. Fortune. Accessed April 27, 2026. https://fortune.com/2026/02/21/peter-thiel-bill-gates-steve-jobs-steve-chen-tech-billionaires-publicly-shielding-their-children-from-tech-products-social-media/
Reinecke, L., Gilbert, A., & Eden, A. (2022). Self-regulation as a key boundary condition in the relationship between social media use and well-being. Current Opinion in Psychology, 45, 101296. https://doi.org/10.1016/j.copsyc.2021.12.008
Rizzolatti, G., Sinigaglia, C. The mirror mechanism: a basic principle of brain function. Nat Rev Neurosci 17, 757–765 (2016). https://doi.org/10.1038/nrn.2016.135
Sakai, J. (2020). How synaptic pruning shapes neural wiring during development and, possibly, in disease. Proceedings of the National Academy of Sciences of the United States of America, 117(28), 16096–16099. https://doi.org/10.1073/pnas.2010281117
Shonkoff, J. P., & Phillips, D. A. (Eds.). (2000). From neurons to neighborhoods: The science of early childhood development. National Academies Press. https://doi.org/10.17226/9824
Soo, Z. (2023, January 19). China keeping 1 hour daily limit on kids’ online games. AP News. Accessed April 27, 2026. https://apnews.com/article/gaming-business-children-00db669defcc8e0ca1fc2dc54120a0b8
Swingle, M. K. (2019). I-Minds-: How and why constant connectivity is rewiring our brains and what to do about it. New Society Publishers. https://www.amazon.com/i-Minds-Constant-Connectivity-Rewiring-Brains/dp/0865719012
Theyer, A., & Wijeakumar, S. (2025). Brain–behavior associations during interactions between caregivers and infants. Infancy, 30(5), e70044. https://doi.org/10.1111/infa.70044 Tronick, E. (2007). Still Face Experiment Dr Edward Tronick. YouTube. Retrieved April 29, 2026. https://www.youtube.com/watch?v=YTTSXc6sARg
UN. (2025, December 10). Social media: Age-related bans won’t keep kids safe, UNICEF warns. United Nations-UN News. Accessed April 27, 2026. https://news.un.org/en/story/2025/12/1166557
Vezenkov, S. R., & Manolova, V. R. (2025a). Screen addiction – Biomarkers, developmental damage and recovery. Nootism, 1(1), 6–18. https://doi.org/10.64441/nootism.2NCSC.1
Vezenkov, S. R., & Manolova, V. R. (2025b). Neurobiology of autism / early screen addiction recovery. Nootism, 1(1), 19–36. https://doi.org/10.64441/nootism.2NCSC.2
Vezenkov, S. R., & Manolova, V. R. (2025c). Screen-induced pathological vestibular reflex: A specific marker of early screen addiction. Nootism, 1(2), 5–10. https://doi.org/10.64441/nootism.1.2.1
Vezenkov, S. R., & Manolova, V. R. (2025d). Screen-induced pathological eye-covering reflex in children with early screen addiction. Nootism, 1(3), 5–10. https://doi.org/10.64441/nootism.1.3.1
Vezenkov, S. R., & Manolova, V. R. (2025e). Sensory disintegration versus sensory deprivation: Vestibular–visual dynamics and shared behavioral phenotypes in ASD and early blindness. Nootism, 1(6), 4–12. https://doi.org/10.64441/nootism.1.6.1
Weinberg, M. K., Beeghly, M., Olson, K. L., & Tronick, E. (2008). A still-face paradigm for young children: 2½-year-olds’ reactions to maternal unavailability during the still-face. Journal of Developmental Processes, 3(1), 4–22. https://pmc.ncbi.nlm.nih.gov/articles/PMC3289403/
Wilkinson, C. L., Yankowitz, L. D., Chao, J. Y., Gutiérrez, R., Rhoades, J. L., Shinnar, S., Purdon, P. L., & Nelson, C. A. (2024). Developmental trajectories of EEG aperiodic and periodic components in children 2–44 months of age. Nature Communications, 15(1), 5788. https://doi.org/10.1038/s41467-024-50204-4
World Health Organization. (2019, April 24). To grow up healthy, children need to sit less and play more. https://www.who.int/news/item/24-04-2019-to-grow-up-healthy-children-need-to-sit-less-and-play-more#
Zivan, M., Bar, S., Jing, X., Hutton, J., Farah, R., & Horowitz-Kraus, T. (2019). Screen-exposure and altered brain activation related to attention in preschool children: An EEG study. Trends in Neuroscience and Education, 17, 100117. https://doi.org/10.1016/j.tine.2019.100117
Download the complete article: https://peperperspective.com/wp-content/uploads/2026/08/0-when-screens-replace-connections-2026-05-07.pdf
Hope for dry eyes and eye strain
Posted: March 2, 2026 Filed under: attention, behavior, Breathing/respiration, computer, digital devices, emotions, health, Pain/discomfort, relaxation, screen fatigue, self-healing, stress management, techstress, Uncategorized, vision, zoom fatigue | Tags: behavioral optometry, blinking, digital eye strain, dry eyes, eyes, ophthalmology, optometry, prarasympathetic regulation 1 CommentAdapted from: Peper, E., Yoshino, A., & Harvey, R. (2026). Hope for dry eyes and eye strain: How breathing-blinking patterns Influence dry eye experience. Biofeedback. 54(1), 25-30. https://doi.org/10.5298/1081-5937-54.01.25
Many times during the day, I let my shoulders and face relax, and with each exhalation I feel the upper eyelids slightly dropping down at the same time as I am relaxing my jaw and mouth while sitting tall. I sense my tongue and throat sinking and feeling an increase in the space between my upper and lower molars. At the same time, I sense my eyes becoming soft and sinking down as my face muscle relax and are pulled down by gravity while sensing a gentle smile. My eyes are not trying to focus on anything. I continue to breathe slowly allowing a pause before inhaling and feel totally safe and at peace. While doing this, I sense moisture at the lower eyelids. After I have inhaled and as I exhale, I slowly open my eyes, and return to my work. My eyes feel slightly moist and as I blink, the eyelids glide smoothly over the corneal surface.
Background
Dry eyes and eye strain are far more common than most people realize. More than 50% of adults in the United States and Europe experience irritated or burning eyes, dryness, eye strain, headaches, tired or heavy eyes, sensitivity to bright light, and general eye discomfort (Wozniak et al., 2025). The prevalence increases with age and is higher among people who smoke, wear contact lenses, or spend excessive time looking at screens—typically more than six hours per day (Uchino et al,, 2013).
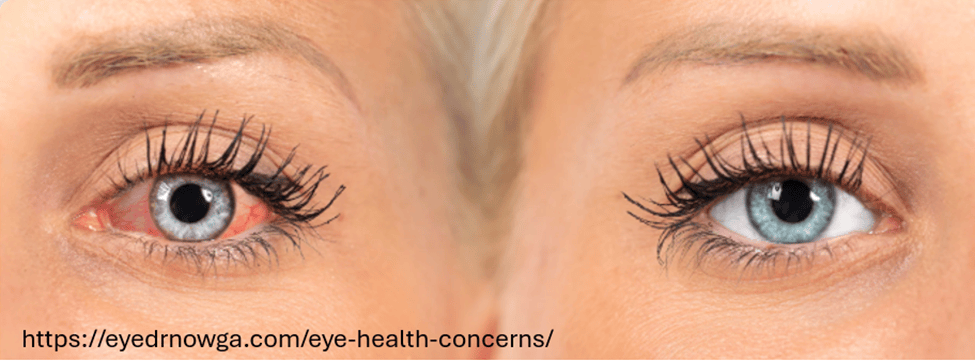
Prolonged, intense screen use—often referred to as digital eye strain or computer vision syndrome—occurs when people focus and concentrate, and the muscles involved with near vision contract and do not relax (Chu et al., 2014). During near vision, the ciliary muscles tighten around the lens to allow near focus, and the medial rectus muscles contract to converge the eyes. These muscles stay contracted and only relax when looking into the distance. This ongoing tension and increased sympathetic activation combined with reduced blinking decrease tearing, and contribute to dry eye symptoms because the tears are not able to provide adequate moisture. As a result, the eyes may become irritated, red and inflamed, which increases eye discomfort (Sheppard & Wolffsohn, 2018; Portello et al., 2012; Sheedy et al., 2003).
When someone is vigilant, fearful, or anticipates a threat, sympathetic activation increases (Ranti et al., 2020) and “eye blink are inhibited at precise moments in time so as to minimize the loss of visual information that occurs during a blink. The more important the visual information is to the viewer, the more likely he or she will be to inhibit blinking” (Ranti et al., 2020).
Without being aware, many people are in a chronic state of vigilance and unknowingly are scanning the world for threats to which they must react. Clinically, I often observe this when guiding clients in relaxation. For example, when I give the instruction, “Let me lift your hand,” some clients immediately lift their hand towards me. This nonverbal response suggests that they are constantly vigilant and are monitoring the world around them—always ready to act instead of trusting that they do not have to act and that the world is safe. In most cases, their breathing pattern tends to be shallow and thoracic.
Would it be possible that this ongoing vigilance,which increases sympathetic arousal contributes to the experience of dry eye syndrome? It could be one factor explaining why women have a higher incidence of dry eye disease as well as anxiety than men since the world is often less safe for women, and they breathe more thoracically and less diaphragmatically (abdominally) than men. Shallow chest breathing is also associated with increased in anxiety (Fugl-Meyer, 1974; Mendes et al., 2020; Wilhelm et al., 2001; Banushi eat al., 2023; McLean et al., 2011; Jalnapurkar, et al., 2018).
Note: The risk of dry eye can also be further increased by a wide range of medical conditions and medications, such as diabetes; glaucoma and glaucoma medications; allergies; autoimmune diseases; arthritis; thyroid disease; high cholesterol; acne treatments; antihistamines; antidepressants; and a history of refractive surgery, conjunctival infections, or corneal abrasions. Dry eye also occurs more frequently in women (Mohamed et al., 2024).
What is usually recommended to resolve dry eyes
The primary and effective first-line treatment to reduce the symptoms of dry eye disease is the use of artificial tears (lubricating eye drops) to provide relief (Maity et al., 2025). Another recommendation to reduce eye strain associated with computer use is to implement the 20/20/20 rule developed by the American Optometric Association–take a 20-second break every 20 minutes and look at something 20 feet away (AOA, 2026). Although the 20/20/20 practice can reduce eye strain and momentarily reduce some of the symptoms associated with dry eye disease especially if the eyes are closed, how we orient, breathe and look may contribute to the experience of dry eye discomfort.
Experience how to evoke dry eyes
Sit comfortably, look around, and observe how your eyes feel. Close your eyes. Now imagine there is a threat. Take a very quick gasp through an open mouth by inhaling into your upper chest and keep breathing very shallowly and irregularly. At the same time, open your eyes wide while being vigilant and looking for danger. Simultaneously, tense your body, inclining it slightly backward as if trying to avoid something. Do not blink, as you may miss the potential threat approaching you (adapted from Lemeignan et al., 1990; Bloch, 2017). A sample physiological recording of this pattern is shown in Figure 1.
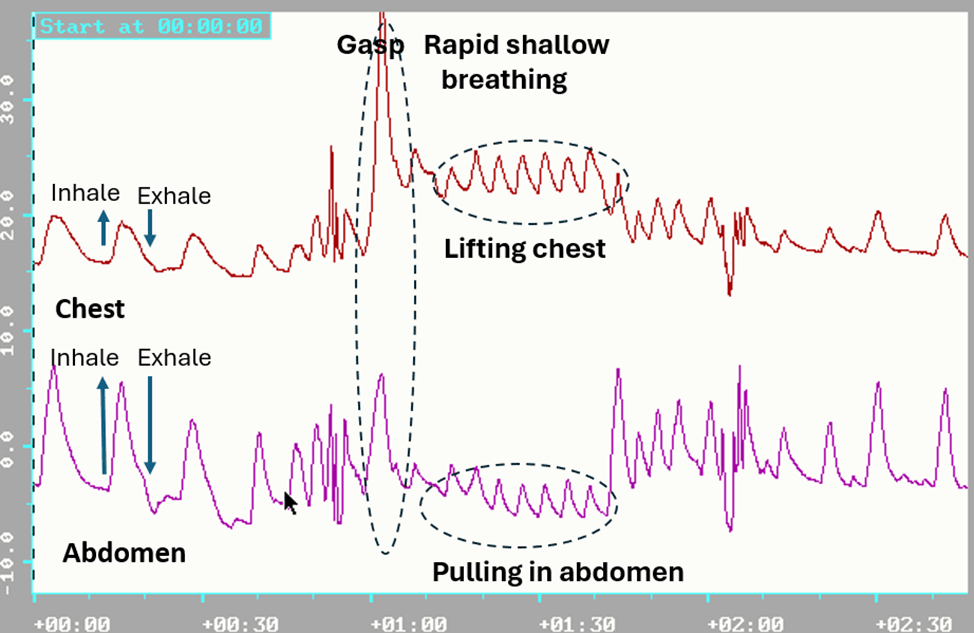
Figure 1. Breathing pattern in response to a threat; a rapid gasp into the chest and pulling the abdomen in to protect while breathing shallowly and rapidly.
Most participants report that almost immediately they feel their eyes getting cooler and after 15 seconds, drier. This facial, breathing, and posture pattern is an exaggeration of the somatic expression of fear that is evoked when we are vigilant and feel unsafe, and it increases sympathetic arousal (Kalawski, 2020).
In most cases, this pattern is automatic, and occurs without awareness, and increases sympathetic activity (Narkiewicz et al., 2006). On the other hand, slow diaphragmatic breathing tends to reduce sympathetic activity (Harada et al., 2014; Lehrer & Gevirtz, 2014). Clinically, the vigilance pattern can often be observed as a person slightly lifts and expands their chest during inhalation and drops and constricts it during exhalation, while breathing shallowly and rapidly without any abdomen expansion or constriction. It is often punctuated with brief breath holding and a reduced blinking rate during concentration.
To investigate these observations more systematically, we compared the practice of gasping while opening the eyes with gentle exhalation while opening the eyes—a pattern that may reduce sympathetic activation and alter the subjective sensation of eye dryness.
Participants: 13 males and 13 females; average age, 39 years
Procedure: While sitting comfortably with their eyes closed, participants were guided through the following two practices:
1.Gasp while opening the eyes
Sit comfortably and look around and observe how your eyes feel. Now close your eyes. Now imagine there is a threat. Take a very quick gasp through an open mouth by inhaling into your upper chest and keep breathing very shallowly and irregularly. At the same time, open your eyes wide while being vigilant and looking for danger. Simultaneously, tense your body, inclining it slightly backward as if trying to avoid something. Do not blink, as you may miss the potential threat approaching you. Repeat three times.
2. Gentle exhalation while opening the eyes
Sit comfortably and look around and observe how your eyes feel. Now close your eyes. Breathe comfortably and inhale by allowing your abdomen to extend and widen while feeling your eyes sinking in their sockets and becoming softer as you gently start exhaling. While gently exhaling, begin to open your eyes very slowly, looking down through your eyelashes without caring what you see, allowing your jaw and face muscles to relax and feeling a slight smile. When you feel the urge to inhale, allow your eyes to close and let your abdomen expand as you inhale slowly. Repeat three times.
After these two practices, the participants filled out a short assessment questionnaire in which they rated how their eyes felt on a scale from -5 (dry), 0 (normal), to 5 (moist/tearing), and rated which eye-opening procedure allowed their eyes to be more relaxed and moist.
Results
92.3% of the participants reported that opening their eyes during exhalation significantly increased eye relaxation and moisture, as shown in Figure 2. A one-way analysis of variance (ANOVA) revealed a significant difference between the inhale condition (M = −0.19, n = 26) and the exhale condition (M = 1.00, n = 25), F(1, 49) = 9.65, p = .003. The experience of eye irritation was correlated (r = 0.64) with the self-rating of experiencing anxiety and fear during the last three months.
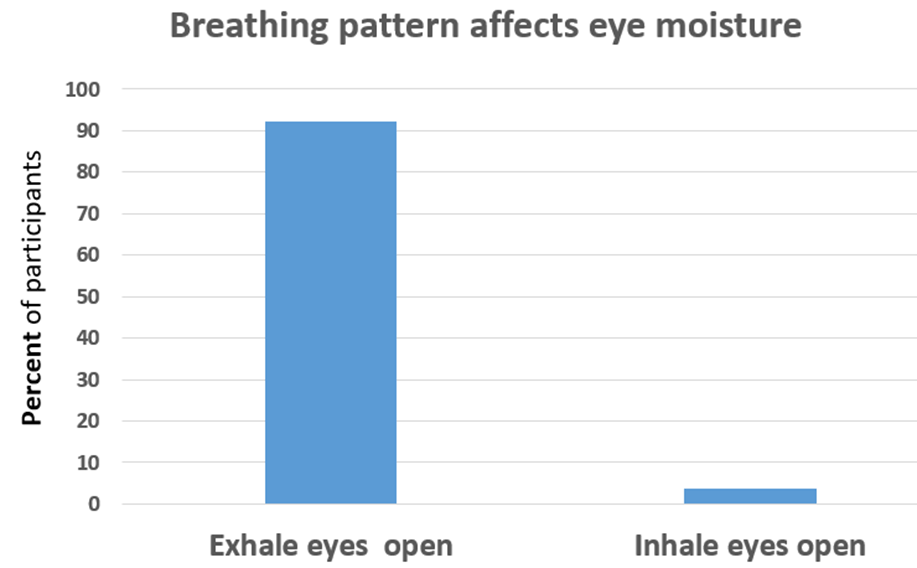
Figure 2. Gently opening the eyes during exhalation increases the experience of moisture and relaxation in the eyes.
Discussion
The results suggest that increased moisture and eye relaxation could be evoked by changing breathing-blinking patterns. Nearly all participants experienced an increase in tearing and eye relaxation; however, long-term benefits most likely occur if the person implements this practice many times during the day. By changing the breathingg-blink pattern and peacefully looking at the world with a smile, one would decrease sympathetic arousal and increase parasympathetic activity. This approach should be taught as the first self-care intervention to reduce eye irritation.
Recommendations to decrease dry eye and improve eye health
- Experience how the two different breathing and eye-opening practices described above affect your eye dryness or moistness.
- When you sense the first onset of minimal eye discomfort or when looking at screens on your computer or cellphone, implement the following practice for about 10 to 15 seconds. Allow your eyelids to close. Be aware of the sensations in your eyes, let your face and jaw relax as if they are being pulled down by gravity while sensing the eyes becoming soft and sinking into their sockets. Breathe diaphragmatically by allowing the abdomen to expand when you inhale. While gently exhaling, slowly open your eyes slightly while looking down with a gentle smile and sensing the moisture beginning to occur in the eyes. Repeat twice.
- During the day, implement the 20/20/20 vision-regeneration practice (every 20 minutes, take a 20-second break and look at something 20 feet away without caring what you see), as shown in Figure 3.
- Read and incorporated the many practices described in the superb book, Vision for Life; Ten Steps to Natural Eye Improvement, by Meir Schneider (2012).

Figure 3. The 20/20/20 rule poster to prevent eye strain (AOA, 2026).
Do these practices many times and be aware of the sensations in your eyes and face. This passive awareness, in conjunction with slower breathing, tends to reduce sympathetic arousal and increase parasympathetic activity, which facilitates increased tearing. As one participant reported when she practiced this:
What a surprise it was when I closed my eyes and breathed slowly and diaphragmatically, and then, as I began to exhale, I very slowly began to open my eyes while looking down and through my eyelashes, while feeling my eyes sink into their sockets. Tearing occurred spontaneously, and my eyes felt lubricated. What a relief. It provided hope that I could help myself instead of only depending on lubricating eye drops whenever my eyes felt dry and irritated.
Two books to maintain and improve vision and reduce techstress
Vision for Life: Ten Steps to Natural Eye Improvement by Meir Schneider (2016) offers many strategies you can immediately incorporate into your daily life to improve and restore your vision. It provides guidelines on how to reverse developing vision issues before they cause damage and how to remedy existing problems, including near- and far-sightedness, lazy eye, as well as more serious conditions such as cataracts, glaucoma, optic neuritis, detached retinas and retinal tears, macular degeneration, and retinitis pigmentosa.

TechStress: How Technology is Hijacking our Lives, Strategies for Coping, and Pragmatic Ergonomics by Erik Peper, Richard Harvey, and Nancy Faass (2020) offers practical tools to avoid the evolutionary traps that trip us up and address the problems associated with technological overuse. It includse effective strategies and practices that individuals can use to optimize their workspace, reduce physical strain, correct posture, and improve vision. It provides fresh insights on reducing stress and enhancing health.

Listen to the expanded podcast based on this blog produced with Google Notebook LM.
Additional blogs that offer strategies to improve vision
References
AOA. (2026). 20/20/20/ to prevent digital eyes strain. American Optometric Association. https://www.aoa.org/AOA/Images/Patients/Eye%20Conditions/20-20-20-rule.pdf
Banushi, B., Brendle, M., Ragnhildstveit, A., Murphy, T., Moore, C., Egberts, J., & Robison, R. (2023). Breathwork interventions for adults with clinically diagnosed anxiety disorders: A scoping review. Brain Sciences, 13(2), 256. https://doi.org/10.3390/brainsci13020256
Bloch, S. (2017). Alba Emoting: A scientific method for emotional induction. Scotts Valley, CA: CreateSpace Independent Publishing Platform. https://www.amazon.com/Alba-Emoting-Scientific-Emotional-Induction/dp/154254884
Chu, C.A., Rosenfield, M., Portello, J.K. (2014). Blink patterns: reading from a computer screen versus hard copy. Optom Vis Sci., 91(3),297-302. https://doi.org/10.1097/OPX.0000000000000157
Craig, J. P., Nichols, K. K., Akpek, E. K., et al. (2017). TFOS DEWS II definition and classification report. The Ocular Surface, 15(3), 276–283. https://doi.org/10.1016/j.jtos.2017.05.008
Dartt, D. A. (2009). Neural regulation of lacrimal gland secretory processes: Relevance in dry eye diseases. Progress in Retinal and Eye Research, 28(3), 155–177. https://doi.org/10.1016/j.preteyeres.2009.04.003
Fugi-Meyer, A.R. (1974). Relative respiratory contribution of the rib cage and the abdomen in males and females with special regard to posture. Respiration, 31(3), 240–251. https://doi.org/10.1159/000193113
Harada, D., Asanoi, H., Takagawa, J., Ishise, H., Ueno, H., Oda, Y., Goso, Y., Joho, S., & Inoue, H. (2014). Slow and deep respiration suppresses steady-state sympathetic nerve activity in patients with chronic heart failure: from modeling to clinical application. American Journal of Physiology-Heart and Circulatory Physiology, 307(8), H1159–H1168. https://doi.org/10.1152/ajpheart.00109.2014
Jalnapurkar, I., Allen, M., & Pigott, T. (2018). Sex differences in anxiety disorders: A review. Journal of Psychiatry, Depression & Anxiety, 4, 011. https://doi.org/10.24966/PDA-0150/100011
Kalawski, J.P. (2020) The Alba Method and the Science of Emotions. Integr. Psych. Behav. 54, 903–919. https://doi.org/10.1007/s12124-020-09525-4
Lehrer, P. M., & Gevirtz, R. (2014). Heart rate variability biofeedback: How and why does it work? Frontiers in Psychology, 5, Article 756. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC4104929/
Lemeignan, M., Guitart, L., & Bloch, S. (1990). Autonomic differentiation of emotional effector pattern of 6 basic emotions. Proceedings of the Fifth International Congress of Psychophysiology, Budapest, July 9–14, 199
Maity, M., Allay, M. B., Ali, M. H., Basu, S., & Singh, S. (2025). Effect of different artificial tears on tear film parameters in dry eye disease. Optometry and Vision Science, 102(1), 37–43. https://doi.org/10.1097/OPX.0000000000002206
McLean, C. P., Asnaani, A., Litz, B. T., & Hofmann, S. G. (2011). Gender differences in anxiety disorders: Prevalence, course of illness, comorbidity and burden of illness. Journal of Psychiatric Research, 45(8), 1027–1035. https://doi.org/10.1016/j.jpsychires.2011.03.006
Mendes, L. P. S., Vieira, D. S. R., Gabriel, L. S., Ribeiro-Samora, G. A., Dornelas de Andrade, A., Brandão, D. C., Goes, M. C., Fregonezi, G. A. F., Britto, R. R., & Parreira, V. F. (2020). Influence of posture, sex, and age on breathing pattern and chest wall motion in healthy subjects. Brazilian Journal of Physical Therapy, 24(3), 240–248. https://doi.org/10.1016/j.bjpt.2019.02.007
Mohamed, Z., Alrasheed, S., Abdu, M., & Allinjawi, K. (2024). Dry eye disease prevalence and associated risk factors among the Middle East population: A systematic review and meta-analysis. Cureus, 16(9), e70522. https://doi.org/10.7759/cureus.70522
Narkiewicz, K., van de Borne, P., Montano, N., Hering, D., Kara, T., & Somers, V. K. (2006). Sympathetic neural outflow and chemoreflex sensitivity are related to spontaneous breathing rate in normal men. Hypertension, 47(1), 51–55. https://doi.org/10.1161/01.HYP.0000197613.47649.0
Peper, E., Harvey, R., & Faass, N. (2020). TechStress: How Technology is Hijacking our Lives, Strategies for Coping, and Pragmatic Ergonomics, North Atlantic Books. https://www.amazon.com/Beyond-Ergonomics-Prevent-Fatigue-Burnout/dp/158394768X
Portello, J.K., Rosenfield, M., Bababekova, Y., et al. (2012). Computer-related visual symptoms in office workers. Ophthalmic and Physiological Optics, 32, 375–82. https://doi.org/10.1111/j.1475-1313.2012.00925.x
Ranti, C., Jones, W., Klin, A. et al. Blink Rate Patterns Provide a Reliable Measure of Individual Engagement with Scene Content. Sci Rep 10, 8267 (2020). https://doi.org/10.1038/s41598-020-64999-x
Schneider, M. (2016). Vision for Life: Ten Steps to Natural Eye Improvement. North Atlantic Books. https://www.amazon.com/Vision-Life-Revised-Eyesight-Improvement/dp/1623170087
Sheedy, J.E., Hayes, J.N., & Engle, J.(2003). Is all asthenopia the same? Optom Vis Sci, 80, 732–9. https://doi.org/10.1097/00006324-200311000-00008
Sheppard, A. L., & Wolffsohn, J. S. (2018). Digital eye strain: prevalence, measurement and amelioration. BMJ open Ophthalmology, 3(1), e000146. https://doi.org/10.1136/bmjophth-2018-000146
Stern, M. E., Gao, J., Siemasko, K. F., Beuerman, R. W., & Pflugfelder, S. C. (2004). The role of the lacrimal functional unit in the pathophysiology of dry eye. Experimental Eye Research, 78(3), 409–416. https://doi.org/10.1016/j.exer.2003.09.003
Swamynathan, S. K., & Wells, A. (2020). Conjunctival goblet cells: Ocular surface functions, disorders that affect them, and the potential for their regeneration. The Ocular Surface, 18(1), 19–26. https://doi.org/10.1016/j.jtos.2019.11.005
Uchino, M., Yokoi, N., Uchino, Y., Dogru, M., Kawashima, M., Komuro, A., Sonomura, Y., Kato, H., Kinoshita, S., Schaumberg, D.A., & Tsubota, K. (2013). Prevalence of Dry Eye Disease and its Risk Factors in Visual Display Terminal Users: The Osaka Study. American Journal of Ophthalmology, 156(4), 759-766.e1, https://doi.org/10.1016/j.ajo.2013.05.040
The epidemiology of dry eye disease: report of the Epidemiology Subcommittee of the International Dry Eye WorkShop (2007). Ocul Surf. , 5(2), 93-107. https://doi.org/10.1016/s1542-0124(12)70082-4
Wilhelm, F. H., Gevirtz, R., & Roth, W. T. (2001). Respiratory dysregulation in anxiety, functional cardiac, and pain disorders: Assessment, phenomenology, and treatment. Behavior Modification, 25(4), 513–545. https://doi.org/10.1177/0145445501254003
Wozniak, P., et al. (2025, September 12–16). Dry eye symptoms, severity, treatment and unmet needs: An analysis of the United States of America and a multinational snapshot (NESTS Study) [Poster presentation]. 43rd Congress of the European Society of Cataract and Refractive Surgeons (ESCRS), Copenhagen, Denmark. https://www.sciencedaily.com/releases/2025/09/250914205829.htm
Ziemssen, F., & Ruprecht, K. W. (2005).Autonomic dysfunction in dry eye syndrome. Ophthalmologe, 102(8), 744–749. https://doi.org/10.1007/s00347-005-1169-1
Ensorcelled: Breaking the Digital Enchantment
Posted: October 7, 2025 Filed under: ADHD, attention, behavior, cellphone, computer, digital devices, education, emotions, healing, health, laptops, techstress, Uncategorized | Tags: anxiety, depression, health, human connection, life, loneliness, media addictdion, mental-health, storytelling 2 Comments
My mom called, “Stop playing on your computer and come for dinner!” I heard her, but I was way too into my game. It felt like I was actually inside it. I think I yelled “Yeah!” back, but I didn’t move.
A few seconds later, I was totally sucked into this awesome world where I was conquering other galaxies. My avatar was super powerful, and I was winning this crazy battle.
Then, all of a sudden, my mom came into my room and just turned off the computer. I was so mad. I was about to win! The real world around me felt boring and empty. I didn’t even feel hungry anymore. I didn’t say anything, I just wanted to go back to my game.
For some, the virtual world feels more real and exciting than the actual one. It can seem more vivid precisely because they have not yet tasted the full, multi-dimensional richness of real human connection, those moments when you feel seen, touched, and understood.
This theme comes vividly alive in my son Eliot Peper’s new novella, Ensorcelled. I am so proud of him. He has crafted a story in which a young boy, captured by the spell of the immersive digital world, discovers that real-life experiences carry far deeper meaning. I won’t give away the plot, but the story creates the experience, it doesn’t just tell it. It reminds us that meaning and belonging arise through genuine connection, not through screens. As Eliot writes, “Sometimes a story is the only thing that can save your life.” It’s a story everyone should read.
The effects of our immersive digital world
Our new world of digital media can take over the reality of actual experiences. It is no wonder that more young people feel stressed and have social anxiety when they have to make an actual telephone call instead of texting (Jin, 2025). They also experience a significant increase in anxiety and depression and feel more awkward initiating in-person social communication with others. The increase in mental health problems and social isolation affects predominantly those who are cellphone and social media natives; namely, those who started to use social media after Facebook was released in 2004 and the iPhone in 2007 (Braghieri et al., 2022).
Students who are most often on their phone whether streaming videos, scrolling, texting, watching YouTube, Instagram or TikTok, and more importantly responding to notifications from phones when they are socializing, report higher levels of loneliness, depression and anxiety as shown inf Figure 1 (Peper & Harvey 2018). They also report less positive feelings and energy when they communicate with each other online as compared to in person (Peper & Harvey, 2024).
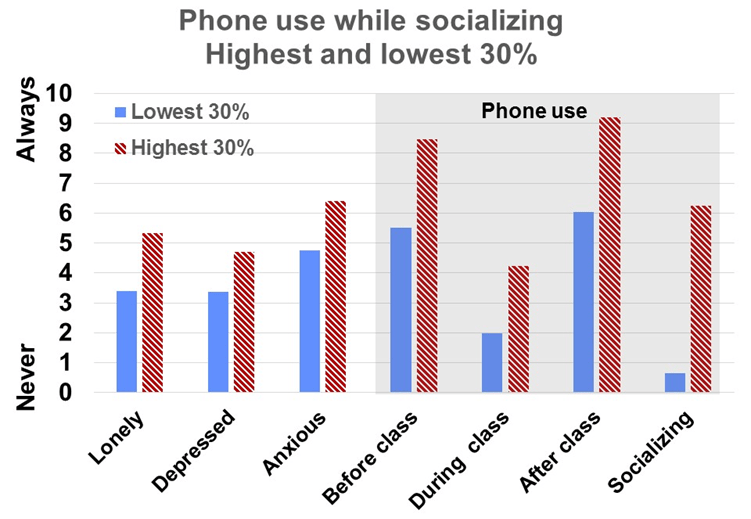
Figure 1. The those with the highest phone use were the most lonely, depressed and anxious (Peper and Harvey, 2018).
Even students’ sexual activity has decreased in U.S. high-school from 2013 to 2023 and young adults (ages 18-44) from 2000-2018 (CDC, 2023; Ueda et al., 2020). Much of this may be due to the reality that adolescents have reduced face-to-face socializing (dating, parties, going out) while increasing their time on digital media (Twenge et al., 2019).
What to do
As a parent it often feels like a losing battle to pull your child, or even yourself, away from the intoxicating digital media, since the digital world is supercharged with AI-generated media. It is all aimed at capturing eyeballs (your attention and time), resulting reducing genuine human social connection. (Peper at al., 2020; Haidt, 2024). To change behavior is challenging and yet rewarding. If possible, implement the following (Peper at al., 2020; Twenge, 2025; Haidt, 2024):
- Create tech-free zones. Keep phones and devices out of bedrooms, the dinner table, and family gatherings. Make these spaces sacred for real connection.
- Avoid screens before bedtime. Turn off screens at least an hour before bed. Replace scrolling with quiet reflection, reading, or gentle stretching. Read or tell actual stories before bedtime.
- Explore why we turn to digital media. Before you open an app, ask: Why am I doing this? Am I bored, anxious, or avoiding something? Awareness shifts behavior.
- Provide unstructured time. Let yourself and your children be bored sometimes. Boredom sparks creativity, imagination, and self-discovery.
- Create shared experiences. Plan family activities that don’t involve screens—cooking, hiking, playing music, or simply talking. Real connection satisfies what digital media only mimics.
- Implement social support. Coordinate with other parents, friends, or colleagues to agree on digital limits. Shared norms make it easier to follow through.
- Model what you want your children to do. Children imitate what they see. When adults practice digital restraint, kids learn that real life matters more than screen life.
We have a choice.
We can set limits now and experience real emotional connection and growth or become captured, enslaved, and manipulated by the corporate creators, producers and sellers of media.
Read Ensorcelled. which uses storytelling, the traditional way to communicate concepts and knowledge. Read it, share it. It may change your child’s life and your own.

Available from
Signed copy by author: https://store.eliotpeper.com/products/ensorcelled
Paperback: https://www.amazon.com/Ensorcelled-Eliot-Peper/dp/1735016535/
Kindle: https://www.amazon.com/Ensorcelled-Eliot-Peper-ebook/dp/B0FLGQC3BS/
References
Braghieri, L., Levy, R., & Makarin, A. (2022). Social Media and Mental Health (July 28, 2022) http://dx.doi.org/10.2139/ssrn.3919760
CDC. (2023). Centers for Disease Control and Prevention. (2023). Youth Risk Behavior Survey: Data summary & trends report 2011–2021. U.S. Department of Health and Human Services. https://www.cdc.gov/healthyyouth/data/yrbs/index.htm
Haidt, J. (2024). The Anxious Generation: How the Great Rewiring of Childhood Is Causing an Epidemic of Mental Illness. New York: Penguin Press. https://www.amazon.com/Anxious-Generation-Rewiring-Childhood-Epidemic/dp/0593655036
Jin, B. (2025). Avoidance and Anxiety About Phone Calls in Young Adults: The Role of Social Anxiety and Texting Controllability. Communication Reports, 1–14. https://doi.org/10.1080/08934215.2025.2542562
Peper, E. & Harvey, R. (2018). Digital addiction: increased loneliness, depression, and anxiety. NeuroRegulation. 5(1),3–8. doi:10.15540/nr.5.1.3 5(1),3–8. http://www.neuroregulation.org/article/view/18189/11842
Peper, E. & Harvey, R. (2024). Smart phones affects social communication, vision, breathing, and mental and physical health: What to do! Townsend Letter-Innovative Health Perspectives, September 15, 2024. https://townsendletter.com/smartphone-affects-social-communication-vision-breathing-and-mental-and-physical-health-what-to-do/
Peper, E., Harvey, R. & Faass, N. (2020). TechStress: How Technology is Hijacking Our Lives, Strategies for Coping, and Pragmatic Ergonomics. Berkeley: North Atlantic Books.
Ueda, P., Mercer, C. H., Ghaznavi, C., & Herbenick, D. (2020). Trends in frequency of sexual activity and number of sexual partners among adults aged 18 to 44 years in the US, 2000–2018. JAMA Network Open, 3(6), e203833. https://doi.org/10.1001/jamanetworkopen.2020.3833
Twenge, J.M. (2025). 10 Rules for Raising Kids in a High-Tech World: How Parents Can Stop Smartphones, Social Media, and Gaming from Taking Over Their Children’s Lives. New York: Atria Books. https://www.amazon.com/Rules-Raising-Kids-High-Tech-World/dp/1668099993
Twenge, J. M., Spitzberg, B. H., & Campbell, W. K. (2019). Less in-person social interaction with peers among U.S. adolescents in the 21st century and links to loneliness. Journal of Social and Personal Relationships, 36(6), 1892-1913. https://doi.org/10.1177/0265407519836170
Addicted to Your Phone? How to Separate from Your Phone for a Healthy Lifestyle
Posted: April 15, 2025 Filed under: ADHD, attention, cellphone, computer, digital devices, educationj, Evolutionary perspective, health, laptops, posture, screen fatigue, self-healing, stress management, techstress, zoom fatigue | Tags: cognitive function, digital detox, health, internet, mental-health, mindfulness, multi-tasking, social isolation, social media, technology 1 CommentFrom: Peper, E. (2025 April 15). Addicted to your phone? How to separate you’re your phone for a healthy lifestyle. Townsend Letter-Innovative Health Perspectives. https://townsendletter.com/addicted-to-your-phone-how-to-separate-from-your-phone-for-a-healthy-lifestyle/; Adapted from the book by Erik Peper, Richard Harvey and Nancy Faass, TechStress-How Technology is Hijacking our Lives, Strategies for Coping and Pragmatic Ergonomics, North Atlantic Press. https://www.amazon.com/Beyond-Ergonomics-Prevent-Fatigue-Burnout/dp/158394768X/

Abstract
In today’s hyper-connected world, technology has subtly ensnared us in evolutionary traps, exploiting innate survival instincts to capture and fragment our attention. Although digital devices offer unprecedented convenience, they simultaneously may harm our mental, physical, and emotional well-being through prolonged screen exposure, digital distraction, and sedentary behavior. The unintended consequences of constant connectivity may increase anxiety, loneliness, and cognitive overload. Social media, Zoom fatigue, and media multitasking reinforce a cycle of passivity and diminished memory retention and attention span, while also reshaping our posture, behavior, and social interactions. The evidence suggests a growing mental health crisis. Yet, with conscious interventions such as digital detoxes, posture awareness, scheduled breaks, and sleep hygiene, we can reclaim our well-being. Rather than reject technology, we must learn to engage with it mindfully, respecting both our evolutionary design and the need for balance in a digital age.
Our Evolutionary Traps with Technology
Maintaining and optimizing health at the computer means re-envisioning our relationship with technology—and reclaiming health, happiness, and sanity in a plugged-in world. We have the ability to control everything from our mobile phones without needing to get up from our seat. Work, social life, and online learning all involve the mobile phone or some type of smart devices.
A convenient little device that is supposed to simplify our lives has actually trapped us into a vicious cycle of relying on it for every single thing we must do. We spend most of our day being exposed to digital displays on our smartphones, computers, gaming consoles, and other digital devices, immersing ourselves in the content we are viewing. From work related emails or tasks, to spending our free time looking at the screen for texting, playing games, and updating social media sites on a play-by-play of what we are eating, wearing, and doing. We click on one hyperlink after the other and create a vicious cycle trapped for hours until we realize we need to move. We are unaware how much time has frittered away without actually doing anything productive and then, we realize we have wasted another day.
Below are some recent estimates of ‘daily active user’ minutes per day that use a screen
• Facebook about an hour per day
• Instagram just under an hour per day
• Texting about 45 minutes per day
• Internet browsing, about 45 minutes per day
• Snapchat, about 30 minutes per day
• Twitter, about 25 minutes per day
Adolescents and college students interact with media for over 40 hours per week, or around six hours per day. That is a lot of hours spent on staring at the screen, which makes it almost impossible not to be distracted by the digital screen. In time, we rehearse a variety of physical body postures as well as a variety of cognitive and behavioral states that impact our physical, mental, emotional, and social health. The powerful audiovisual formats override our desires to do something different, that some of us become enslaved to streaming videos, playing virtual games, or texting. We then tell ourselves that the task that needs to be done, will be finished later. That later becomes never by the end of the day, since the ongoing visual and auditory notifications from our apps interrupt and/or capture our attention. This difficulty to turn away from visual or auditory stimuli roots in our survival instincts.
Each time visual or auditory stimuli occur, we automatically check it out and see if it is a friend or foe, safety or danger. It is such an automatic response that we are unaware we are reacting. The good news is that we all have experienced this compelling effect. Even when we are waiting for a response and the notification has not arrived, we may anticipate or project that there may be new information on our social media accounts, and sometimes we become disappointed when the interval between notifications is long. As one student said, “Don’t worry, they’ll respond. It’s only been 30 seconds.” Anticipating responses from the media can interrupt what we are otherwise doing. Rather than finishing our work or task, we continuously check for updates on social media, even though we probably know that there are no new important messages to which we would have to respond right away. As a result our attention span has decreased from 150 seconds in 2004 to 44 seconds in 2021 (Mark, 2023).
Unfortunately, some forms of social media interactions also lead to a form of social isolation, loneliness–sometimes called phoneliness (Christodoulou, G., Majmundar, A., Chou, C-P, & Pentz, M.A., 2020; Kardaras, 2017). Digital content requires the individual to respond to the digital stimuli, without being aware of the many verbal and nonverbal communication cues (facial expressions, gestures, tone of voice, eye contact, body language, posture, touch, etc.) that are part of social communication (Remland, 2016).
It is no wonder that more and more adolescents are experiencing anxiety, depression, loneliness, and attention deficit disorders due to a constant “digital diet,” which some have argued includes not only media but also junk food. Mental health trends have significantly worsened, particularly since 2013. Pediatric mental health–related emergency department visits increased by 70% from 2011 to 2020, rising from 4.8 million to 7.5 million—a shift from 7.7% to 13.1% of all pediatric emergency visits. The greatest increases were observed among adolescents and across all sexes, races, and ethnicities. Suicide-related visits nearly quintupled from 2011 to 2023, increasing from 0.9% to 4.2% of all pediatric emergency department visits (Bommersbach et al., 2023).
In my class survey of 99 college students, 85% reported experiencing anxiety, 48% neck and shoulder tension, and 41% abdominal discomfort.
For the age groups 18–23 and 24–29—but not for those over 30—the rates of serious psychological distress and major depressive episodes nearly doubled from 2013 to 2019 (Braghieri et al, 2022). During this same period, there was also a significant decline in academic performance, with math scores for 8th graders and reading scores for 4th graders dropping from around 2013 to 2024, except among top-performing students (Mervosh, 2025).
We are not saying to avoid the beneficial parts of the digital age. Instead, it should be used in moderation and to be aware of how some material and digital platforms prey upon our evolutionary survival mechanisms. Unfortunately, most people – especially children – have not evolved skills to counter the negative impacts of some types of media exposure. Parental control and societal policies may be needed to mitigate the damage and enhance the benefits of the digital age.
Zoom Fatigue – How to Reduce it and Configure your Brain for Better Learning
Zoom became the preferred platform for academic teaching and learning for synchronous education during the pandemic. Thus, students and faculty have been sitting and looking at the screen for hours on end. While looking at the screen, the viewers were often distracted by events in their environment, notifications from their mobile phones, social media triggers, and emails; which promoted multitasking (Solis, 2019). These digital distractions cause people to respond to twice as many devices with half of our attention – a process labeled semi-tasking’– meaning getting twice as much done and half as well.
We now check our phones an average of 96 times a day – that is once every 10 minutes and an increase of 20% as compared to two years ago (Asurion Research, 2019). Those who do media multitasking such as texting while doing a task perform significantly worse on memory tasks than those who are not multitasking (Madore et al., 2020). Multitasking is negatively correlated with school performance (Giunchiglia et al, 2018). The best way to reduce multitasking is to turn off all notifications (e.g., email, texts, and social media) and let people know that you will look at the notifications and then respond in a predetermined time, so that you will not be interrupted while working or studying.
When students in my class chose to implement a behavior change to monitor mobile phone and media use and reduce the addictive behavior during a five-week self-healing project, many reported a significant improvement of health and performance. For example one student reported that when she reduced her mobile phone use, her stress level equally decreased as shown in Figure 1 (Peper et al, 2021).
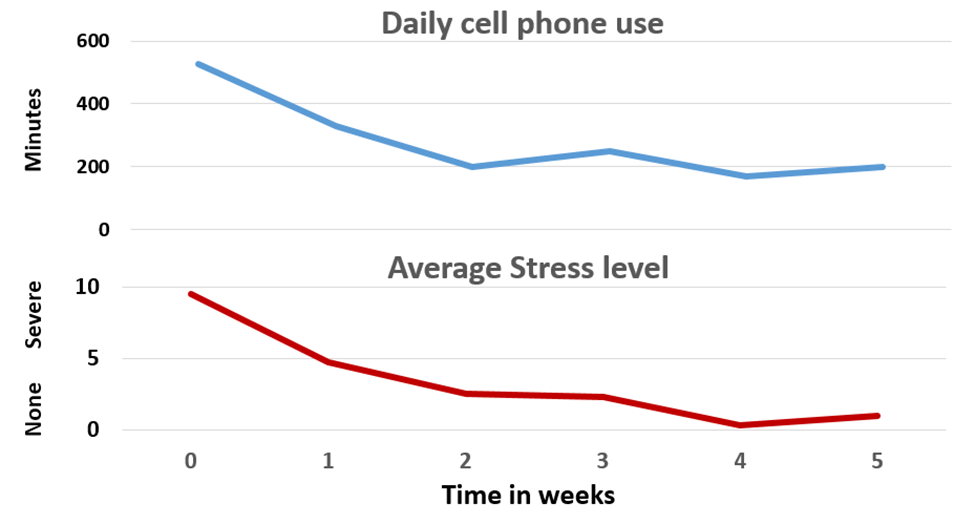
Figure 1. Example of student changing mobile phone use and corresponding decrease in subjective stress level. Reproduced by permission from Peper et al. (2021).
During this class project, many students observed that the continuous responding to notifications and social media affected their health and productivity. As one student reported: The discovery of the time I wasted giving into distractions was increasing my anxiety, increasing my depression and making me feel completely inadequate. In the five-week period, I cut my cell phone usage by over half, from 32.5 hours to exactly 15 hours and used some of the time to do an early morning run in the park. Rediscovering this time makes me feel like my possibilities are endless. I can go to work full time, take online night courses reaching towards my goal of a higher degree, plus complete all my homework, take care of the house and chores, cook all my meals, and add reading a book for fun! –22-year-old College Student
Numerous students reported that it was much easier to be distracted and multitask, check social media accounts or respond to emails and texts than during face-to-face classroom sessions as illustrated by two student comments from San Francisco State University.
“Now that we are forced to stay at home, it’s hard to find time by myself/for myself, time to study, and or time to get away. It’s easy to get distracted and go a bit stir-crazy.”
“I find that online learning is more difficult for me because it’s harder for me to stay concentrated all day just looking at the screen.”
Students often reported that they had more difficulty remembering the material presented during synchronous presentations. Most likely, the passivity while watching Zoom presentations affected the encoding and consolidation of new material into retrievable long-term memory. The presented material was rapidly forgotten when the next screen image or advertisement appeared and competed with the course instructor for the student’s attention. We hypothesize that the many hours of watching TV and streaming videos have conditioned people to sit and take in information passively, while discouraging them to respond or initiate action (Mander, 1978; Mărchidan, 2019).
To reduce the deleterious impact of media use, China has placed time limits on cellphone use, gaming, and social media use for children. On February 2021 Chinese children were banned from taking their mobile phones into school (Wakefield, 2021), on August 2021 Children under 18 were banned from playing video games during the week and their play was restricted to just one hour on Fridays, weekends and holidays (McDonell, 2021) and beginning on September 20, 2021 children under 14 who have been authenticated using their real name can access Douyin, the Chinese version of Tik Tok, for maximum of 40 minutes a day between the hours of 6:00 and 22:00 (BBC, 2021).
Ways to Avoid Zoom
Say goodnight to your phone: It is common for people to use their mobile phone before going to bed, and then end up having difficulty falling asleep. The screen emits blue light that sends a signal to your brain that says it is daytime instead of night. This causes your body to suppress the production of the melatonin hormone, which tells your body that it is time to sleep. Reading or watching content also contributes, since it stimulates your mind and emotions and thereby promotes wakefulness (Hartley et al., 2022). Implement sleep hygiene and stop using your phone or watching screens 30-minutes before going to bed for a better night’s sleep.
Maintaining a healthy vision: We increase near visual stress and the risk of developing myopia when we predominantly look at nearby surfaces. We do not realize that eye muscles can only relax when looking at the far distance. For young children, the constant near vision remodels the shape of the eye and the child will likely develop near sightedness. The solutions are remarkably simple. Respect your evolutionary background and allow your eyes to spontaneously alternate between looking at near and far objects while being upright (Schneider, 2016; Peper, 2021; Peper, Harvey & Faass, 2020).
Interrupt sitting disease: We sit for the majority of the day while looking at screens that is a significant risk factor for diabetes, cardiovascular disease, depression and anxiety (Matthews et al., 2012; Smith et al., 2020). Interrupt sitting by getting up every 30 minutes and do a few stretches. You will tend to feel less sleepy, less discomfort and more productive. As one of our participants reported that when he got up, moved and exercised every 30 minutes at the end of the day he felt less tired. As he stated, “There is life after five,” which meant he had energy to do other activities after working at the computer the whole day. While working time flies and it is challenging to get up every 30 minutes. Thus, install a free app on your computer that reminds you to get up and move such as StretchBreak (www.stretchbreak.com).
Use slouching as a cue to change: Posture affects thoughts and emotions as well as, vice versa. When stressed or worried (e.g., school performance, job security, family conflict, undefined symptoms, or financial insecurity), our bodies tend to respond by slightly collapsing and shifting into a protective position.
When we collapse/slouch, we are more at risk to:
• Feel helpless (Riskind & Gotay, 1982).
• Feel powerless (Westfeld & Beresford, 1982; Cuddy, 2012).
• Recall and being more captured by negative memories (Peper, Lin, Harvey, & Perez, 2017; Tsai, Peper, & Lin, 2016).
• Experience cognitive difficulty (Peper, Harvey, Mason, & Lin, 2018).
When stressed, anxious or depressed, it is challenging to change. The negative feelings, thoughts and worries continue to undermine the practice of reframing the experience more positively. Our recent study found that a simple technique, that integrates posture with breathing and reframing, rapidly reduces anxiety, stress, and negative self-talk (Peper, Harvey, Hamiel, 2019). When you are captured by helpless defeated thoughts and slouch, use the thought or posture as the trigger to take change. The moment you are aware of the thoughts or slouched posture, sit up straight, look up, take a slow large diaphragmatic breath and only then think about reframing the problem positively (Peper, Harvey, Hamiel, 2019).
When we are upright and look up, we are more likely to:
• Have more energy (Peper & Lin, 2012).
• Feel stronger (Peper, Booiman, Lin, & Harvey, 2016).
• Find it easier to do cognitive activity (Peper, Harvey, Mason, & Lin, 2018).
• Feel more confident and empowered (Cuddy, 2012).
• Recall more positive autobiographical memories (Michalak, Mischnat,& Teismann, 2014).
The challenge is that we are usually unaware we have begun to slouch. A very useful solution is to use a posture feedback device to remind us, such as the UpRight Go (https://www.uprightpose.com/). This simple device and app signals you when you slouch. The device attaches to your neck and connects with blue tooth to your cellphone. After calibrating, it provides vibrational feedback on your neck each time you slouch. When participants use the vibration feedback to become aware of what is going on and interrupt their slouch by stretching and sitting up, they report a significant decrease in symptoms and an increase in productivity. As one student reported: “Having immediate feedback on my posture helped me to be more aware of my body and helped me to link my posture to my emotions. Before using the tracker, doing this was very difficult for me. It not only helped my posture but my awareness of my mental state as well.”
https://peperperspective.com/2023/08/30/techstress-building-healthier-computer-habits/
https://peperperspective.com/2024/09/04/cellphones-affects-social-communication-vision-breathing-and-health-what-to-do/
References
Asurion Research (November 19, 2019). Americans Check Their Phones 96 Times a Day. https://www.asurion.com/about/press-releases/americans-check-their-phones-96-times-a-day/#:~:text=Despite%20our%20attempts%20to%20curb,tech%20care%20company%20Asurion1.
BBC (2021, September 20). China: Children given daily time limit on Douyin – its version of TikTok. BBC. Accessed April 12, 2025. https://www.bbc.com/news/technology-58625934
Bommersbach, T.J., McKean, A.J., Olfson, M., & Rhee, T.G. (2023). National Trends in Mental Health-Related Emergency Department Visits Among Youth, 2011-2020. JAMA, (2), 329(17), 1469-1477. https://doi.org/10.1001/jama.2023.4809
Braghieri, Land and Levy, Ro’ee and Makarin, Alexey, Social Media and Mental Health (July 28, 2022). http://dx.doi.org/10.2139/ssrn.3919760
Christodoulou, G. Majmundar, A., Chou, C-P., & Pentz, M.A. (2020). Anhedonia, screen time, and substance use in early adolescents: A longitudinal mediation analysis, Journal of Adolescence, (78), 24-32. https://doi.org/10.1016/j.adolescence.2019.11.007
Cuddy, A. (2012). Your body language shapes who you are. Technology, Entertainment, and Design (TED) Talk. Accessed April 12, 2025. www.ted.com/talks/amy_cuddy_your_body_language_shapes_who_you_are
Giunchiglia, F. Zeni, M., Gobbi, E., Bignotti,E., & Bison, I. (2018). Mobile social media usage and academic performance, Computers in Human Behavior, 82, 177-185. https://doi.org/10.1016/j.chb.2017.12.04
Hartley, S., Royant-Parola, S., Zayoud, A., Gremy, I., & Matulonga, B. (2022). Do both timing and duration of screen use affect sleep patterns in adolescents?. PloS one, 17(10), e0276226. https://doi.org/10.1371/journal.pone.0276226
Kardaras, N. (2017). Glow Kids: How Screen Addiction Is Hijacking Our Kids – and How to Break the Trance. New York: St. Martin’s Griffin. https://www.amazon.com/Glow-Kids-Screen-Addiction-Hijacking/dp/1250146550/
Madore, K.P., Khazenzon, A.M., Backes, C.W. et al. (2020). Memory failure predicted by attention lapsing and media multitasking. Nature, 587, 87–91. https://doi.org/10.1038/s41586-020-2870-z
Mander, J. (1978). Four arguments for elimination of television. New York: William Morrow Paperbacks. https://www.amazon.com/Arguments-Elimination-Television-Jerry-Mander/dp/0688082742/
Mărchidan, A. (2019). More technologized is not more educated,” 2019 11th International Conference on Electronics, Computers and Artificial Intelligence (ECAI), Pitesti, Romania, pp. 1-4, https://doi.org/10.1109/ECAI46879.2019.9041993
Mark, G. (2023). Attention Span: A Groundbreaking Way to Restore Balance, Happiness and Productivity. Toronto, Canada: Hanover Square Press. https://www.amazon.com/Attention-Span-Finding-Fighting-Distraction/dp/1335449418
Matthews, C.E., George, S.M., Moore, S.C., Bowles, H.R. Blair, A.,. Park, I., Troiano, R.P., Hollenbeck, A., & Schatzkin, A. (2012). Amount of time spent in sedentary behaviors and cause-specific mortality in US adults. The American Journal of Clinical Nutrition, (92)@, 437-445. https://doi.org/10.3945/ajcn.111.019620
McDonell, S. (2021, August 30). China to limit children’s online gaming time. BBC World Business Report. Accessed April 12, 2025. https://www.bbc.co.uk/programmes/w172y48xs9s5l56
Mervosh, S. (2025, April 7). The Pandemic is not the only reason U.S. Students are losing ground. New York Times. https://www.nytimes.com/2025/04/07/us/low-performing-students-reasons.html?smid=nytcore-ios-share&referringSource=articleShare
Michalak, J., Mischnat, J., & Teismann, T. (2014). Sitting Posture Makes a Difference—Embodiment Effects on Depressive Memory Bias. Clinical Psychology & Psychotherapy, (21),6, 519-524. https://doi.org/10.1002/cpp.1890
Peper, E. (2021). Resolve Eyestrain and Screen Fatigue. Well Being Journal, (30), Wintger, 24-28. https://www.researchgate.net/publication/345123096_Resolve_Eyestrain_and_Screen_Fatigue
Peper, E., Booiman, A., Lin, I.M., & Harvey, R. (2016). Increase strength and mood with
posture. Biofeedback. 44(2), 66–72. https://doi.org/10.5298/1081-5937-44.2.04
Peper, E., Harvey, R. & Faass, N. (2020). TechStress: How Technology is Hijacking Our Lives, Strategies for Coping, and Pragmatic Ergonomics. Berkeley: North Atlantic Books. https://www.amazon.com/Beyond-Ergonomics-Prevent-Fatigue-Burnout/dp/158394768X
Peper, E., Harvey, R., & Hamiel, D. (2019). Transforming thoughts with postural awareness to increase therapeutic and teaching efficacy. NeuroRegulation, 6(3), 153-169. https://doi.org/10.15540/nr.6.3.1533-1
Peper, E., Harvey, R., Mason, L., & Lin, I.-M. (2018). Do better in math: How your body posture may change stereotype threat response. NeuroRegulation, 5(2), 67–74. http://dx.doi.org/10.15540/nr.5.2.67
Peper, E. & Lin, I-M. (2012). Increase or decrease depression-How body postures influence your energy level. Biofeedback, 40 (3), 126-130. https://doi.org/10.5298/1081-5937-40.3.01
Peper, E., Lin, I-M., Harvey, R., & Perez, J. (2017). How posture affects memory recall and mood. Biofeedback. 45 (2), 36-41. https://doi.org/10.5298/1081-5937-45.2.01
Peper, E., Wilson, V., Martin, M., Rosegard, E., & Harvey, R. (2021). Avoid Zoom fatigue, be present and learn. NeuroRegulation, 8(1), 47–56. https://doi.org/10.15540/nr.8.1.47
Remland, M.S. Nonverbal Communication in Everyday Life 4th Edition. Thousand Oaks, CA: Sage Publications. https://www.amazon.com/Nonverbal-Communication-Everyday-Martin-Remland/dp/1483370259
Riskind, J.H., Gotay, C.C. Physical posture: Could it have regulatory or feedback effects on motivation and emotion?. Motiv Emot 6, 273–298 (1982). https://doi.org/10.1007/BF00992249
Schneider, M. (2016). Vision for Life. Berkeley, CA: North Atlantic Books. https://www.amazon.com/Vision-Life-Revised-Eyesight-Improvement/dp/1623170087
Smith, L., Jacob, L., Trott, M., Yakkundi, A., Butler, L., Barnett, Y., Armstrong, N.C., McDermott, D., Schuch, F., Meyer, J., López-Bueno, R., Sánchez, G.F.L., Bradley, D., Tully, M.A. (2020). The association between screen time and mental health during COVID-19: A cross sectional study, Psychiatry Research, (292). https://doi.org/10.1016/j.psychres.2020.11333
Solis, B. (2019). How Managers Can Help Workers Tackle Digital Distractions. MIT Sloan Management Review, 60(4), 1-3. https://sloanreview.mit.edu/article/how-managers-can-help-workers-tackle-digital-distractions/
Tsai, H. Y., Peper, E., & Lin, I. M.* (2016). EEG patterns under positive/negative body postures and emotion recall tasks. NeuroRegulation, 3(1), 23-27. https://doi.org/10.15540/nr.3.1.23
Wakefield, J. (2021), February 2). China bans children from using mobile phones at school. BBC. Accessed April 12, 2025. https://www.bbc.com/news/technology-55902778
Weisfeld, G.E., Beresford, J.M. Erectness of posture as an indicator of dominance or success in humans. Motiv Emot 6, 113–131 (1982). https://doi.org/10.1007/BF00992459
Cellphones affects social communication, vision, breathing, and health: What to do!
Posted: September 4, 2024 Filed under: ADHD, attention, behavior, Breathing/respiration, cellphone, computer, digital devices, educationj, ergonomics, health, laptops, Neck and shoulder discomfort, posture, screen fatigue, self-healing, stress management, techstress, Uncategorized, vision, zoom fatigue | Tags: communication, myopia, pedestrian deaths, peripheral vision, text neck 7 CommentsAdapted from: Peper, E. & Harvey, R. (2024). Cell phones affects social communication, vision, breathing, and mental and physical health: What to do! TownsendLetter-The Examiner of Alternative Medicine,September 15, 2024. https://townsendletter.com/smartphone-affects-social-communication-vision-breathing-and-mental-and-physical-health-what-to-do/

Abstract
Smartphones are an indispensable part of our lives. Unfortunately too much of a ‘good thing’ regarding technology can work against us, leading to overuse, which in turn influences physical, mental and emotional development among current ‘Generation Z’ and ‘Millennial’ users (e.g., born 1997-2012, and 1981-1996, respectively). Compared to older technology users, Generation Z report more mental and physical health problems. Categories of mental health include attentional deficits, feelings of depression, anxiety social isolation and even suicidal thoughts, as along with physical health complaints such as sore neck and shoulders, eyestrain and increase in myopia. Long duration of looking downward at a smartphone affects not only eyestrain and posture but it also affects breathing which burden overall health. The article provides evidence and practices so show how technology over use and slouching posture may cause a decrease in social interactions and increases in emotional/mental and physical health symptoms such as eyestrain, myopia, and body aches and pains. Suggestions and strategies are provided for reversing the deleterious effects of slouched posture and shallow breathing to promote health.
We are part of an uncontrolled social experiment
We, as technology users, are all part of a social experiment in which companies examine which technologies and content increase profits for their investors (Mason, Zamparo, Marini, & Ameen, 2022). Unlike University research investigations which have a duty to warn of risks associated with their projects, we as participants in ‘profit-focused’ experiments are seldom fully and transparently informed of the physical, behavioral and psychological risks (Abbasi, Jagaveeran, Goh, & Tariq, 2021; Bhargava, & Velasquez, 2021). During university research participants must be told in plain language about the risks associated with the project (Huh-Yoo & Rader, 2020; Resnik, 2021). In contrast for-profit technology companies make it possible to hurriedly ‘click through’ terms-of-service and end-user-license-agreements, ‘giving away’ our rights to privacy, then selling our information to the highest bidder (Crain, 2021; Fainmesser, Galeotti, & Momot, 2023; Quach et al., 2022; Yang, 2022).
Although some people remain ignorant and or indifferent (e.g., “I don’t know and I don’t care”) about the use of our ‘data,’ an unintended consequence of becoming ‘dependent’ on technology overuse includes the strain on our mental and physical health (Abusamak, Jaber & Alrawashdeh, 2022; Padney et al., 2020). We have adapted new technologies and patterns of information input without asking the extent to which there were negative side effects (Akulwar-Tajane, Parmar, Naik & Shah, 2020; Elsayed, 2021). As modern employment shifted from predominantly blue-collar physical labor to white collar information processing jobs, people began sitting more throughout the day. Workers tended to look down to read and type. ‘Immobilized’ sitting for hours of time has increased as people spend time working on a computer/laptop and looking down at smartphones (Park, Kim & Lee, 2020). The average person now sits in a mostly immobilized posture 10.4 hours/day and modern adolescents spent more than two thirds of their waking time sitting and often looking down at their smartphones (Blodgett, et al., 2024; Arundell et al., 2019).
Smartphones are an indispensable part of our lives and is changing the physical and mental emotional development especially of Generation Z who were born between 1997-2012 (Haidt, 2024). They are the social media and smartphone natives (Childers & Boatwright, 2021). The smartphone is their personal computer and the gateway to communication including texting, searching, video chats, social media (Hernandez-de-Menendez, Escobar Díaz, & Morales-Menendez, 2020; Nichols, 2020; Schenarts, 2020; Szymkowiak et al., 2021). It has 100,000 times the processing power of the computer used to land the first astronauts on the moon on July 20, 1969 according to University of Nottingham’s computer scientist Graham Kendal (Dockrill, 2020). More than one half of US teens spend on the average more than 7 hours on daily screen time that includes watching streaming videos, gaming, social media and texting and their attention span has decreased from 150 seconds in 2004 to an average of 44 seconds in 2021 (Duarte, F., 2023; Mark, 2022, p. 96).
For Generation Z, social media use is done predominantly with smartphones while looking down. It has increased mental health problems such as attentional deficits, depression, anxiety suicidal thoughts, social isolation as well as decreased physical health (Haidt, 2024; Braghieri et al., 2023; Orsolini, Longo & Volpe, 2023; Satılmış, Cengız, & Güngörmüş, 2023; Muchacka-Cymerman, 2022; Fiebert, Kistner, Gissendanner & DaSilva, 2021; Mohan et al., 2021; Goodwin et al., 2020).
The shift in communication from synchronous (face-to-face) to asynchronous (texting) has transformed communications and mental health as it allows communication while being insulated from the other’s reactions (Lewis, 2024). The digital connection instead of face-to-face connection by looking down at the smart phone also has decreased the opportunity connect with other people and create new social connections, with three typical hypotheses examining the extent to which digital technologies (a) displace/ replace; (b) compete/ interfere with; and/or, (c) complement/ enhance in-person activities and relationships (Kushlev & Leitao, 2020).
As described in detail by Jonathan Haidt (2024), in his book, The Anxious Generation, the smartphone and the addictive nature of social media combined with the reduction in exercise, unsupervised play and childhood independence was been identified as the major factors in the decrease in mental health in your people (Gupta, 2023). This article focuses less on distraction such as attentional deficits, or dependency leading to tolerance, withdrawal and cravings (e.g., addiction-like symptoms) and focuses more on ‘dysregulation’ of body awareness (posture and breathing changes) and social communication while people are engaged with technology (Nawaz,Bhowmik, Linden & Mitchell, 2024).
The excessive use of the smartphones is associated with a significant reduction of physical activity and movement leading to a so-called sedentarism or increases of sitting disease (Chandrasekaran & Ganesan, 2021; Nakshine, Thute, Khatib, & Sarkar, 2022). Unbeknown to the smartphone users their posture changes, as they looks down at their screen, may also affect their mental and physical health (Aliberti, Invernizzi, Scurati & D’lsanto, 2020).
(1) Explore how looking at your smartphone affects you (adapted from: Peper, Harvey, & Rosegard, 2024)
For a minute, sit in your normal slouched position and look at your smartphone while intensely reading the text or searching social media. For the next minute sit tall and bring the cell phone in front of you so you can look straight ahead at it. Again, look at your smartphone while intensely reading the text or searching social media.
Compare how the posture affects you. Most likely, your experience is similar to the findings from students in a classroom observational study. Almost all experienced a reduction in peripheral awareness and breathed more shallowly when they slouched while looking at their cellphone.
Decreased peripheral awareness and increased shallow breathing that affects physical and mental health and performance. The students reported looking down position reduces the opportunity of creating new social connections. Looking down my also increases the risk for depression along with reduced cognitive performance during class (Peper et al., 2017; Peper et al., 2018).
(2) Explore how posture affects eye contact (adapted from the exercise shared by Ronald Swatzyna, 2023)[2]
Walk around your neighborhood or through campus either looking downwards or straight ahead for 30 minutes while counting the number of eye contacts you make.
Most likely, when looking straight ahead and around versus slouched and looking down you had the same experience as Ronald Swatzyna (2023), Licensed Clinical Social Worker. He observed that when he walked a three-mile loop around the park in a poor posture with shoulders forward in a head down position, and then reversed direction and walked in good posture with the shoulders back and the head level, he would make about five times as many eye contacts with a good posture compared to the poor posture.
Anecdotal observations, often repeated by many educators, suggest before the omnipresent smartphone, students would look around and talk to each other before a university class began. Now, when Generation Z students enter an in-person class, they sit down, look down at their phone and tend not to interact with other students.
(3) Experience the effect of face-to-face in-person communication
During the first class meeting, ask students to put their cellphones away, meet with three or four other students for a few minutes, and share a positive experience that happened to them last week as well as what they would like to learn in the class. After a few minutes, ask them to report how their energy and mood changed.
In our observational class study with 24 junior and senior college students in the in-person class and 54 students in the online zoom class, almost all report that that their energy and positive mood increased after they interacted with each other. The effects were more beneficial for the in-person small group sharing than the online breakout groups sharing on Zoom as shown in Figure 1.
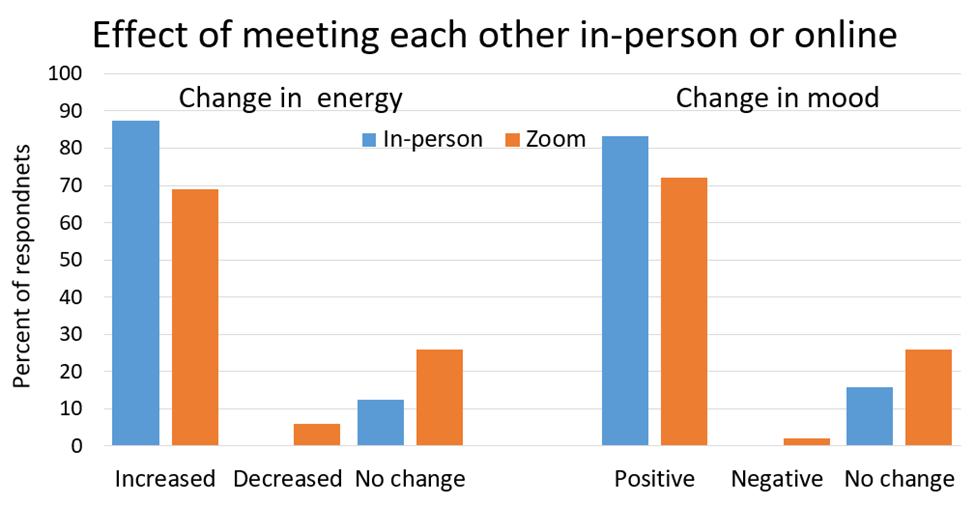
Figure 1. Change in subjective energy and mood after sharing experiences synchronously in small groups either in-person or online.
Without direction of a guided exercise to increase social connections, students tend to stay within their ‘smartphone bubble’ while looking down (Bochicchio et al., 2022). As a result, they appear to be more challenged to meet and interact with other people face-to-face or by phone as is reflected in the survey data that Generation Z is dating much less and more lonely than the previous generations (Cox et al., 2023).
What to do:
- Put the smartphone away so that you do not see it in social settings such as during meals or classes. This means that other people can be present with you and the activity of eating or learning.
- Do not permit smartphones in the classroom including universities unless it is required for a class assignment.
- In classrooms and in the corporate world, create activities that demands face-to-face synchronous communication.
- Unplug from the audio programs when walking and explore with your eyes what is going on around you.
(4) Looking down increases risk of injury and death
Looking down at a close screen reduces peripheral awareness and there by increases the risk of accidents and pedestrian deaths. Pedestrian deaths are up 69% since 2011 (Cova, 2024) and have consistently increased since the introduction of the iPhone in 2007 as shown in Figure 3.
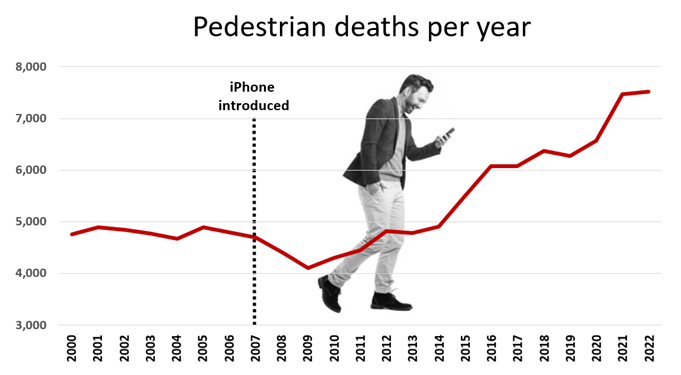
Figure 3. Increase in pedestrian death since the introduction of the iphone (data plotted from https://www.iihs.org/topics/fatality-statistics/detail/pedestrians)
In addition, the increase use of mobile phones is also associated with hand and wrist pain from overuse and with serious injuries such as falls and texting while driving due to lack of peripheral awareness. McLaughlin et al (2023) reports an increase in hand and wrist injuries as well serious injuries related to distracted behaviors, such as falls and texting while driving. The highest phone related injuries (lacerations) as reported from the 2011 to 2020 emergency room visits were people in the age range from 11–20 years followed by 21–30 years.
What to do:
- Do not walk while looking at your smartphone. Attend to the environment around you.
- Unplug from the audio podcasts when walking and explore with your eyes what is going on around you.
- Sit or stop walking when answering the smartphone to reduce the probability of an accident.
- For more pragmatic suggestions, see the book, TechStress: How Technology is Hijacking Our Lives, Strategies for Coping, and Pragmatic Ergonomics, by Peper, Harvey and Faass (2020).
(5) Looking at screens increases the risk of myopia
Looking at a near screen for long periods of time increases the risk of myopia (near sightedness) which means that distant vision is more blurry. Myopia has increased as children predominantly use computers or, smartphones with smaller screen at shorter distances. By predominantly focusing on nearby screens without allowing the eye to relax remodels the eyes structure. Consequently, myopia has increase in the U.S. from 25 percent in the early 1970s to nearly 42 percent three decades later (OHSU, 2022).
Looking only at nearby screens, our eyes converge and the ciliary muscles around the lens contract and remain contracted until the person looks at the far distance. The less opportunity there is to allow the eyes to look at distant vision, the more myopia occurs. in Singapore 80 per cent of young people aged 18 or below have nearsightedness and 20 % of the young people have high myopia as compared to 10 years ago (Singapore National Eye Centre, 2024). The increase in myopia is a significant concern since high myopia is associated with an increased risk of vision loss due to cataract, glaucoma, and myopic macular degeneration (MMD). MMD is rapidly increasing and one of the leading causes of blindness in East Asia that has one of the highest myopia rates in the world (Sankaridurg et al., 2021).
What to do:
- Every 20 minutes stop looking at the screen and look at the far distance to relax the eyes for 20 seconds.
- Do not allow young children access to cellphones or screens. Let them explore and play in nature where they naturally alternate looking at far and near objects.
- Implement the guided eye regenerating practices descrubed in the article, Resolve eyestrain and screen fatigue, by Peper (2021).
- Read Meir Schneider’s (2016) book, Vision for Life, for suggestions how to maintain and improve vision.
(6) Looking down increases tech neck discomfort
Looking down at the phone while standing or sitting strains the neck and shoulder muscles because of the prolonged forward head posture as illustrated in the YouTube video, Tech Stress Symptoms and Causes (DeWitt, 2018). Using a smartphone while standing or walking causes a significant increase in thoracic kyphosis and trunk (Betsch et al., 2021). When the head is erect, the muscle of the neck balance a weight of about 10 to 12 pounds or, approximately 5 kilograms; however, when the head is forward at 60 degrees looking at your cell phone the forces on the muscles are about 60 pound or more than 25 kilograms, as illustrated in Figure 4 (Hansraj, 2014).
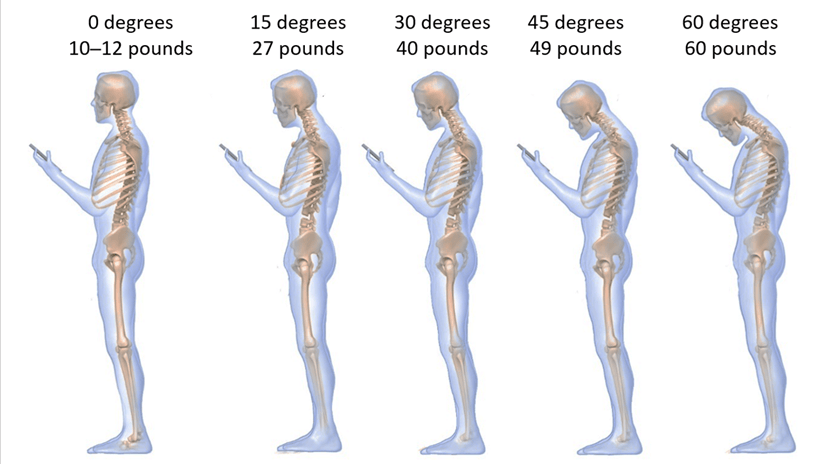
Figure 4. The head forward position puts as much as sixty pounds of pressure on the neck muscles and spine (by permission from Dr. Kenneth Hansraj, 2014).
This process is graphically illustrated in the YouTube video, Text Neck Symptoms and Causes Video, produced by Veritas Health (2020).
What to do:
- Keep the phone in front of you so that you do not slouch down by having your elbow support on the table.
- Every ten minutes stretch, look up and roll your shoulders backwards.
- Wear a posture feedback device such as the UpRight Go 2 to remind you when you slouch to change posture and activity (Peper et al., 2019; Stuart, Godfrey & Mancini, 2022).
- Take Alexander Technique lessons to improve your posture (Cacciatore, Johnson, & Cohen, 2020; AmAT, 2024; STAT, 2024).
(7) Looking down increases negative memory recall and depression
In our previous research, Peper et al. (2017) have found that recalling hopeless, helpless, powerless, and defeated memories is easier when sitting in a slouched position than in an upright position. Recalling positive memories is much easier when sitting upright and looking slightly upward than sitting slouched position. If attempting to recall positive memories the brain has to work hard as indicated by an significantly higher amplitudes of beta2, beta3, and beta4 EEG (i.e., electroencephalograph) when sitting slouched then when sitting upright (Tsai et al., 2016).
Not only does the postural position affect memory recall, it also affects mental math under time-pressure performance. When students sit in a slouched position, they report that is much more difficult to do mental math (serial 7ths) than when in the upright position (Peper et al., 2018). The effect of posture is most powerful for the 70% of students who reported that they blanked out on exams, were anxious, or worried about class performance or math. For the 30% who reported no performance anxiety, posture had no significant effect. When students become aware of slouching thought posture feedback and then interrupt their slouching by sitting up, they report an increase in concentration, attention and school performance (Peper et al., 2024).
How we move and walk also affects our subjective energy. In most cases, when people sit for a long time, they report feeling more fatigue; however, if participants interrupt sitting with short movement practices they report becoming less fatigue and improved cognition (Wennberg et al., 2016). The change in subjective energy and mood depends upon the type of movement practice. Peper & Lin (2012) reported that when students were asked to walk in a slow slouching pattern looking down versus to walk quickly while skipping and looking up, they reported that skipping significantly increased their subjective energy and mood while the slouch walking decreased their energy. More importantly, student who had reported that they felt depressed during the last two years had their energy decrease significantly more when walking very slowly while slouched than those who did not report experiencing depression. Regardless of their self-reported history of depression, when students skipped, they all reported an increase in energy (Peper & Lin, 2012; Miragall et al., 2020).
What to do:
- Walk with a quick step while looking up and around.
- Wear a posture feedback device such as the UpRight Go 2 to remind you when you slouch to change posture and activity (Peper et al., 2019; Roggio et al., 2021).
- When sitting put a small pillow in the mid back so that you can sit more erect (for more suggestions, see the article by Peper et al., 2017a, Posture and mood: Implications and applications to therapy).
- Place photo and other objects that you like to look a slightly higher on your wall so that you automatically look up.
(8) Shallow breathing increases the risk for anxiety
When slouching we automatically tend to breathe slightly faster and more shallowly. This breathing pattern increases the risk for anxiety since it tends to decrease pCO2 (Feinstein et al., 2022; Meuret, Rosenfield, Millard & Ritz, 2023; Paulus, 2013; Smits et al., 2022; Van den Bergh et al., 2013). Sitting slouched also tends to inhibit abdominal expansion during the inhalation because the waist is constricted by clothing or a belt –sometimes labeled as ‘designer jean syndrome’ and may increase abdominal symptoms such as acid reflux and irritable bowel symptoms (Engeln & Zola, 2021; Peper et al., 2016; Peper et al., 2020). When students learn diaphragmatic breathing and practice diaphragmatic breathing whenever they shallow breathe or hold their breath, they report a significant decrease in anxiety, abdominal symptoms and even menstrual cramps (Haghighat et al., 2020; Peper et al., 2022; Peper et al., 2023).
What to do:
- Loosen your belt and waist constriction when sitting so that the abdomen can expand.
- Learn and practice effortless diaphragmatic breathing to reduce anxiety.
Conclusion
There are many topics related to postural health and technology overuse that were addressed in this article. Some topics are beyond the scope of the article, and therefore seen as limitations. These relate to diagnosis and treatment of attentional deficits, or dependency leading to tolerance, withdrawal and cravings (e.g., addiction-like symptoms), or of modeling relationships between factors that contribute to the increasing epidemic of mental and physical illness associated with smartphone use and social media, such as hypotheses examining the extent to which digital technologies (a) displace/ replace; (b) compete/ interfere with; and/or, (c) complement/ enhance in-person activities and relationships. Typical pharmaceutical ‘treat-the-symptom’ approaches for addressing ‘tech stress’ related to technology overuse includes prescribing ‘anxiolytics, pain-killers and muscle relaxants’ (Kazeminasab et al., 2022; Kim, Seo, Abdi, & Huh, 2020). Although not usually included in diagnosis and treatment strategies, suggesting improving posture and breathing practices can significantly affect mental and physical health. By changing posture and breathing patterns, individuals may have the option to optimize their health and well-being.
See the book, TechStress-How Technology is Hijacking our Lives, Strategies for Coping and Pragmatic Ergonomics by Erik Peper, Richard Harvey and Nancy Faass. Available from: https://www.amazon.com/Beyond-Ergonomics-Prevent-Fatigue-Burnout/dp/158394768X/

Explore the following blogs for more background and useful suggestions
References
Abbasi, G. A., Jagaveeran, M., Goh, Y. N., & Tariq, B. (2021). The impact of type of content use on smartphone addiction and academic performance: Physical activity as moderator. Technology in Society, 64, 101521. https://doi.org/10.1016/j.techsoc.2020.101521
Abusamak, M., Jaber, H. M., & Alrawashdeh, H. M. (2022). The effect of lockdown due to the COVID-19 pandemic on digital eye strain symptoms among the general population: a cross-sectional survey. Frontiers in Public Health, 10, 895517. https://doi.org/10.3389/fpubh.2022.895517
Akulwar-Tajane, I., Parmar, K. K., Naik, P. H., & Shah, A. V. (2020). Rethinking screen time during COVID-19: impact on psychological well-being in physiotherapy students. Int J Clin Exp Med Res, 4(4), 201-216. https://doi.org/10.26855/ijcemr.2020.10.014
Aliberti, S., Invernizzi, P. L., Scurati, R., & D’Isanto, T. (2020). Posture and skeletal muscle disorders of the neck due to the use of smartphones. Journal of Human Sport and Exercise , 15 (3proc), S586-S598. https://www.jhse.ua.es/article/view/2020-v15-n3-proc-posture-skeletal-muscle-disorders-neck-smartpho; https://air.unimi.it/retrieve/handle/2434/774436/1588570/HSE%20-%20Posture%20and%20skeletal%20muscle%20disorders.pdf
AmSAT. (2024). American Society for the Alexander Technique. Accessed July 27, 2024. https://alexandertechniqueusa.org/
Arundell, L., Salmon, J., Koorts, H. et al. (2019). Exploring when and how adolescents sit: cross-sectional analysis of activPAL-measured patterns of daily sitting time, bouts and breaks. BMC Public Health 19, 653. https://doi.org/10.1186/s12889-019-6960-5
Bhargava, V. R., & Velasquez, M. (2021). Ethics of the attention economy: The problem of social media addiction. Business Ethics Quarterly, 31(3), 321-359. https://doi.org/10.1017/beq.2020.32
Betsch, M., Kalbhen, K., Michalik, R., Schenker, H., Gatz, M., Quack, V., Siebers, H., Wild, M., & Migliorini, F. (2021). The influence of smartphone use on spinal posture – A laboratory study. Gait Posture, 85, 298-303. https://doi.org/10.1016/j.gaitpost.2021.02.018
Blodgett, J.M., Ahmadi, M.N., Atkin, A.J., Chastin, S., Chan, H-W., Suorsa, K., Bakker, E.A., Hettiarcachchi, P., Johansson, P.J., Sherar,L. B., Rangul, V., Pulsford, R.M…. (2024). ProPASS Collaboration , Device-measured physical activity and cardiometabolic health: the Prospective Physical Activity, Sitting, and Sleep (ProPASS) consortium, European Heart Journal, 45(6) 458–471, https://doi.org/10.1093/eurheartj/ehad717
Bochicchio, V., Keith, K., Montero, I., Scandurra, C., & Winsler, A. (2022). Digital media inhibit self-regulatory private speech use in preschool children: The “digital bubble effect”. Cognitive Development, 62, 101180. https://doi.org/10.1016/j.cogdev.2022.101180
Braghieri, L., Levy, R., & Makarin, A. (2022). Social Media and Mental Health (July 28, 2022). Available at SSRN: https://ssrn.com/abstract=3919760 or http://dx.doi.org/10.2139/ssrn.3919760
Cacciatore, T. W., Johnson, P. M., & Cohen, R. G. (2020). Potential mechanisms of the Alexander technique: Toward a comprehensive neurophysiological model. Kinesiology Review, 9(3), 199-213. https://doi.org/10.1123/kr.2020-0026
Chandrasekaran, B., & Ganesan, T. B. (2021). Sedentarism and chronic disease risk in COVID 19 lockdown–a scoping review. Scottish Medical Journal, 66(1), 3-10. https://doi.org/10.1177/0036933020946336
Childers, C., & Boatwright, B. (2021). Do digital natives recognize digital influence? Generational differences and understanding of social media influencers. Journal of Current Issues & Research in Advertising, 42(4), 425-442. https://doi.org/10.1080/10641734.2020.1830893
Cox, D.A., Hammond, K.E., & Gray, K. (2023). Generation Z and the Transformation of American Adolescence: How Gen Z’s Formative Experiences Shape Its Politics, Priorities, and Future. Survey Center of American Life, November 23, 2023. Accessed July 4, 2024. https://www.americansurveycenter.org/research/generation-z-and-the-transformation-of-american-adolescence-how-gen-zs-formative-experiences-shape-its-politics-priorities-and-future/
Crain, M. (2021). Profit over privacy: How surveillance advertising conquered the internet. U of Minnesota Press. https://www.amazon.com/Profit-over-Privacy-Surveillance-Advertising/dp/1517905044
Cova, E. (2024). Pedestrian fatalities at historic high. Smart Growth America (data from U.S. Department of Transportation (USDOT). Accessed July 2, 2024. https://smartgrowthamerica.org/pedestrian-fatalities-at-historic-high/
Duarte, F. (2023). Average Screen Time for Teens (2024). Exploding Topics. Accessed July 5, 2024. https://explodingtopics.com/blog/screen-time-for-teens#average
DeWitt, D. (2018). How Does Text Neck Cause Pain? Spine-Health October 26, 2018. Accessed July 5, 2024. https://www.spine-health.com/conditions/neck-pain/how-does-text-neck-cause-pain
Dockrill, P. (2020). Your laptop charger is more powerful than Apollo11’s computer, says apple developer. Science Alert, Janural 12, 2020. Accessed July 4, 2024. https://www.sciencealert.com/apollo-11-s-computer-was-less-powerful-than-a-usb-c-charger-programmer-discovers
Elsayed, W. (2021). Covid-19 pandemic and its impact on increasing the risks of children’s addiction to electronic games from a social work perspective. Heliyon, 7(12). https://doi.org/10.1016/j.heliyon.2021.e08503
Engeln, R., & Zola, A. (2021). These boots weren’t made for walking: gendered discrepancies in wearing painful, restricting, or distracting clothing. Sex roles, 85(7), 463-480. https://doi.org/10.1007/s11199-021-01230-9
Fainmesser, I. P., Galeotti, A., & Momot, R. (2023). Digital privacy. Management Science, 69(6), 3157-3173. https://doi.org/10.1287/mnsc.2022.4513
Feinstein, J. S., Gould, D., & Khalsa, S. S. (2022). Amygdala-driven apnea and the chemoreceptive origin of anxiety. Biological psychology, 170, 108305. https://10.1016/j.biopsycho.2022.108305
Fiebert, I., Kistner, F., Gissendanner, C., & DaSilva, C. (2021). Text neck: An adverse postural phenomenon. Work, 69(4), 1261-1270. https://doi.org/10.3233/WOR-213547
Goodwin, R. D., Weinberger, A. H., Kim, J. H., Wu. M., & Galea, S. (2020). Trends in anxiety among adults in the United States, 2008–2018: Rapid increases among young adults. Journal of Psychiatric Research. 130, 441–446. https://doi.org/10.1016/j.jpsychires.2020.08.014
Gupta, N. (2023). Impact of smartphone overuse on health and well-being: review and recommendations for life-technology balance. Journal of Applied Sciences and Clinical Practice, 4(1), 4-12. https://doi.org/10.4103/jascp.jascp_40_22
Haghighat, F., Moradi, R., Rezaie, M., Yarahmadi, N., & Ghaffarnejad, F. (2020). Added Value of Diaphragm Myofascial Release on Forward Head Posture and Chest Expansion in Patients with Neck Pain: A Randomized Controlled Trial. Research Square. https://doi.org/10.21203/rs.3.rs-53279/v1
Haidt, J. (2024). The Anxious generation: How the great rewiring of childhood is causing an epidemic of mental illness. New York: Penguin Press. https://www.anxiousgeneration.com/book
Hansraj, K.K. (2014). Assessment of stresses in the cervical spine caused by posture and position of the head. Surg Technol Int. 25, 277-279. https://pubmed.ncbi.nlm.nih.gov/25393825/
Hernandez-de-Menendez, M., Escobar Díaz, C. A., & Morales-Menendez, R. (2020). Educational experiences with Generation Z. International Journal on Interactive Design and Manufacturing (IJIDeM), 14(3), 847-859. https://doi.org/10.1007/s12008-020-00674-9
Huh-Yoo, J., & Rader, E. (2020). It’s the Wild, Wild West: Lessons learned from IRB members’ risk perceptions toward digital research data. Proceedings of the ACM on Human-Computer Interaction, 4(CSCW1), 1-22. https://doi.org/10.1145/3392868
IIHS (2024). Fatality Facts 2022Pedestrians. The Insurance Institute for Highway Safety (IIHS). Accessed July 2, 2024. https://www.iihs.org/topics/fatality-statistics/detail/pedestrians
Kazeminasab, S., Nejadghaderi, S. A., Amiri, P., Pourfathi, H., Araj-Khodaei, M., Sullman, M. J., … & Safiri, S. (2022). Neck pain: global epidemiology, trends and risk factors. BMC musculoskeletal disorders, 23, 1-13. https://doi.org/10.1186/s12891-021-04957-4
Kim, K. H., Seo, H. J., Abdi, S., & Huh, B. (2020). All about pain pharmacology: what pain physicians should know. The Korean journal of pain, 33(2), 108-120. https://doi.org/10.3344/kjp.2020.33.2.108
Kushlev, K., & Leitao, M. R. (2020). The effects of smartphones on well-being: Theoretical integration and research agenda. Current opinion in psychology, 36, 77-82. https://doi.org/10.1016/j.copsyc.2020.05.001
Lewis, H.R. (2024). Mechanical intelligence and counterfeit humanity. Harvard Magazine, 126(6), 38-40. https://www.harvardmagazine.com/2024/07/harry-lewis-computers-humanity#google_vignette
Mark, G. (2023). Attention Span: A Groundbreaking Way to Restore Balance, Happiness and Productivity. Toronto, Canada: Hanover Square Press. https://www.amazon.com/Attention-Span-Finding-Fighting-Distraction-ebook/dp/B09XBJ29W9
Mason, M. C., Zamparo, G., Marini, A., & Ameen, N. (2022). Glued to your phone? Generation Z’s smartphone addiction and online compulsive buying. Computers in Human Behavior, 136, 107404. https://doi.org/10.1016/j.chb.2022.107404
McLaughlin, W.M., Cravez, E., Caruana, D.L., Wilhelm, C., Modrak, M., & Gardner, E.C. (2023). An Epidemiological Study of Cell Phone-Related Injuries of the Hand and Wrist Reported in United States Emergency Departments From 2011 to 2020. J Hand Surg Glob, 5(2),184-188. https://doi.org/10.1016/j.jhsg.2022.11.009
Meuret, A. E., Rosenfield, D., Millard, M. M., & Ritz, T. (2023). Biofeedback Training to Increase Pco2 in Asthma With Elevated Anxiety: A One-Stop Treatment of Both Conditions?. Psychosomatic medicine, 85(5), 440-448. https://doi.org/10.1097/PSY.0000000000001188
Miragall, M., Borrego, A., Cebolla, A., Etchemendy, E., Navarro-Siurana, J., Llorens, R., … & Baños, R. M. (2020). Effect of an upright (vs. stooped) posture on interpretation bias, imagery, and emotions. Journal of Behavior Therapy and Experimental Psychiatry, 68, 101560. https://doi.org/10.1016/j.jbtep.2020.101560
Mohan, A., Sen, P., Shah, C., Jain, E., & Jain, S. (2021). Prevalence and risk factor assessment of digital eye strain among children using online e-learning during the COVID-19 pandemic: Digital eye strain among kids (DESK study-1). Indian journal of ophthalmology, 69(1), 140-144. https://doi.org/10.4103/ijo.IJO_2535_20
Muchacka-Cymerman, A. (2022). ‘I wonder why sometimes I feel so angry’ The associations between academic burnout, Facebook intrusion, phubbing, and aggressive behaviours during pandemic Covid 19. Polish Psychological Bulletin, 53(4). https://doi.org/10.24425/ppb.2022.143376
Nakshine, V. S., Thute, P., Khatib, M. N., & Sarkar, B. (2022). Increased screen time as a cause of declining physical, psychological health, and sleep patterns: a literary review. Cureus, 14(10). https://doi.org/10.7759/cureus.30051
Nawaz, S., Bhowmik, J., Linden, T., & Mitchell, M. (2024). Validation of a modified problematic use of mobile phones scale to examine problematic smartphone use and dependence. Heliyon, 10(2). https://doi.org/10.1016/j.heliyon.2024.e24832
Nicholas, A. J. (2020). Preferred learning methods of generation Z. Faculty and Staff – Articles & Papers. Digital Commons @ Salve Regina. Salve Regina University. https://digitalcommons.salve.edu/fac_staff_pub/74
OHSU. (2022). Myopia on the rise, especially among children. Casey Eye Institute. Oregan Health and Science University. Accessed July 7, 2024. https://www.ohsu.edu/casey-eye-institute/myopia-rise-especially-among-children
Orsolini, L., Longo, G., & Volpe, U. (2023). The mediatory role of the boredom and loneliness dimensions in the development of problematic internet use. International Journal of Environmental Research and Public Health, 20(5), 4446. https://doi.org/10.3390/ijerph20054446
Pandey, R., Gaur, S., Kumar, R., Kotwal, N., & Kumar, S. (2020). Curse of the technology-computer related musculoskeletal disorders and vision syndrome: a study. International Journal of Research in Medical Sciences, 8(2), 661. https://doi.org/10.18203/2320-6012.ijrms20200253
Park, J. C., Kim, S., & Lee, H. (2020). Effect of work-related smartphone use after work on job burnout: Moderating effect of social support and organizational politics. Computers in human behavior, 105, 106194. https://doi.org/10.1016/j.chb.2019.106194
Paulus, M.P. (2013). The breathing conundrum-interoceptive sensitivity and anxiety. Depress Anxiety.30(4), 315-20. https://doi.org/10.1002/da.22076
Peper, E. (2021). Resolve eyestrain and screen fatigue. Well Being Journal, 30(1), 24-28. https://wellbeingjournal.com/resolve-eyestrain-and-screen-fatigue/
Peper, E., Booiman, A., Lin, I-M, Harvey, R., & Mitose, J. (2016). Abdominal SEMG Feedback for Diaphragmatic Breathing: A Methodological Note. Biofeedback. 44(1), 42-49. https://doi.org/10.5298/1081-5937-44.1.03
Peper, E., Chen, S., Heinz, N. & Harvey, R. (2023). Hope for menstrual cramps (dysmenorrhea) with breathing. Biofeedback, 51(2), 44–51. https://doi.org/10.5298/1081-5937-51.2.04
Peper, E., Harvey, R., Cuellar, Y., & Membrila, C. (2022). Reduce anxiety. NeuroRegulation, 9(2), 91–97. https://doi.org/10.15540/nr.9.2.91
Peper, E., Harvey, R. & Faass, N. (2020). TechStress: How Technology is Hijacking Our Lives, Strategies for Coping, and Pragmatic Ergonomics. Berkeley: North Atlantic Books. https://www.amazon.com/Beyond-Ergonomics-Prevent-Fatigue-Burnout/dp/158394768X
Peper, E., Harvey, R., & Mason, L. (2019). “Don’t slouch!” Improve health with posture feedback. Townsend Letter-The Examiner of Alternative Medicine, 436, 58-61. https://www.researchgate.net/publication/337424599_Don%27t_slouch_Improve_health_with_posture_feedback
Peper, E., Harvey, R., Mason, L., & Lin, I.-M. (2018). Do better in math: How your body posture may change stereotype threat response. NeuroRegulation, 5(2), 67–74. http://dx.doi.org/10.15540/nr.5.2.67
Peper, E., Harvey, R. & Rosegard, E. (2024). Increase attention, concentration and school performance with posture feedback. Biofeedback, 52(2). https://doi.org/10.5298/1081-5937-52.02.07
Peper, E. & Lin, I-M. (2012). Increase or decrease depression-How body postures influence your energy level. Biofeedback, 40 (3), 126-130. https://doi.org/10.5298/1081-5937-40.3.01
Peper, E., Lin, I-M, & Harvey, R. (2017a). Posture and mood: Implications and applications to therapy. Biofeedback, 35(2), 42-48. https://doi.org/10.5298/1081-5937-45.2.03
Peper, E., Lin, I-M., Harvey, R., & Perez, J. (2017). How posture affects memory recall and mood. Biofeedback.45 (2), 36-41. https://doi.org/10.5298/1081-5937-45.2.01
Peper, E., Mason, L., Harvey, R., Wolski, L, & Torres, J. (2020). Can acid reflux be reduced by breathing? Townsend Letters-The Examiner of Alternative Medicine, 445/446, 44-47. https://www.townsendletter.com/article/445-6-acid-reflux-reduced-by-breathing/
Quach, S., Thaichon, P., Martin, K. D., Weaven, S., & Palmatier, R. W. (2022). Digital technologies: tensions in privacy and data. Journal of the Academy of Marketing Science, 50(6), 1299-1323. https://doi.org/10.1007/s11747-022-00845-y
Resnik, D. B. (2021). Standards of evidence for institutional review board decision-making. Accountability in research, 28(7), 428-455. https://doi.org/10.1080/08989621.2020.1855149
Roggio, F., Ravalli, S., Maugeri, G., Bianco, A., Palma, A., Di Rosa, M., & Musumeci, G. (2021). Technological advancements in the analysis of human motion and posture management through digital devices. World journal of orthopedics, 12(7), 467. https://doi.org/10.5312/wjo.v12.i7.467
Sankaridurg, P., Tahhan, N., Kandel, H., Naduvilath, T., Zou, H., Frick,K.D., Marmamula, S., Friedman, D.S., Lamoureux, e. Keeffe, J. Walline, J.J., Fricke, T.R., Kovai, V., & Resnikoff, S. (2021) IMI Impact of Myopia. Invest. Ophthalmol. Vis. Sci, 62(5), 2. https://doi.org/10.1167/iovs.62.5.2
Satılmış, S. E., Cengız, R., & Güngörmüş, H. A. (2023). The relationship between university students’ perception of boredom in leisure time and internet addiction during social isolation process. Bağımlılık Dergisi, 24(2), 164-173. https://doi.org/10.51982/bagimli.1137559
Schenarts, P. J. (2020). Now arriving: surgical trainees from generation Z. Journal of surgical education, 77(2), 246-253. https://doi.org/10.1016/j.jsurg.2019.09.004
Schneider, M. (2016). Vision for life. Ten Steps to Natural Eyesight Improvement. Berkeley: North Atlantic books. https://www.amazon.com/Vision-Life-Revised-Eyesight-Improvement/dp/1623170087
Singapore National Eye Centre. (2024). Severe myopia cases among children in Singapore almost doubled in past decade. CAN. Accessed July 4, 2024. https://www.channelnewsasia.com/singapore/myopia-children-cases-almost-double-glasses-eye-checks-4250266
Smits, J. A., Monfils, M. H., Otto, M. W., Telch, M. J., Shumake, J., Feinstein, J. S., … & Exposure Therapy Consortium. (2022). CO2 reactivity as a biomarker of exposure-based therapy non-response: study protocol. BMC psychiatry, 22(1), 831. https://doi.org/10.1186/s12888-022-04478-x
STAT (2024). The society of teachers of the Alexander Technique. Assessed July 27, 2024. https://alexandertechnique.co.uk/
Stuart, S., Godfrey, A., & Mancini, M. (2022). Staying UpRight in Parkinson’s disease: A pilot study of a novel wearable postural intervention. Gait & Posture, 91, 86-93. https://doi.org/10.1016/j.gaitpost.2021.09.202
Swatzyna, R. (2023). Personal communications.
Szymkowiak, A., Melović, B., Dabić, M., Jeganathan, K., & Kundi, G. S. (2021). Information technology and Gen Z: The role of teachers, the internet, and technology in the education of young people. Technology in Society, 65, 101565. https://doi.org/10.1016/j.techsoc.2021.101565
Tsai, H. Y., Peper, E., & Lin, I. M.*(2016). EEG patterns under positive/negative body postures and emotion recall tasks. NeuroRegulation, 3(1), 23-27. https://doi.org/10.15540/nr.3.1.23
Van den Bergh, O., Zaman, J., Bresseleers, J., Verhamme, P., Van Diest, I. (2013). Anxiety, pCO2 and cerebral blood flow, International Journal of Psychophysiology, 89 (1), 72-77. https://doi.org/10.1016/j.ijpsycho.2013.05.011
Veritas Health. (2020). Text Neck Symptoms and Causes Video. YouTube video, accessed August 29, 2024. https://www.spine-health.com/conditions/neck-pain/how-does-text-neck-cause-pain?source=YT
Wennberg, P., Boraxbekk, C., Wheeler, M., et al. (2016). Acute effects of breaking up prolonged sitting on fatigue and cognition: a pilot study. BMJ Open, 6, e009630. https://doi.org/10.1136/bmjopen-2015-009630
Yang, K. H. (2022). Selling consumer data for profit: Optimal market-segmentation design and its consequences. American Economic Review, 112(4), 1364-1393. https://www.aeaweb.org/articles/pdf/doi/10.1257/aer.20210616
[1] Correspondence should be addressed to: Erik Peper, Ph.D., Institute for Holistic Health Studies, Department of Recreation, Parks, Tourism and Holistic Health, San Francisco State University, 1600 Holloway Avenue, San Francisco, CA 94132 Email: epeper@sfsu.edu; web: www.biofeedbackhealth.org; blog: www.peperperspective.com
[2] I thank Ronald Swatzyna (2023), Licensed Clinical Social Worker for sharing this exercise with me. He discovered that a difference in the number of eye contacts depending how he walked. When he walked a 3.1 mile loop around the park in a poor posture- shoulders forward, head down position- and then reversed direction and walked in good posture with the shoulders back and the head level, that that he make about 5 times as many eye contacts with good posture compared to the poor posture. He observed that he make about five times as many eye contacts with good posture as compared to the poor posture.