From Mutation to Metabolism: A Broader View of Cancer Development
Posted: August 18, 2026 Filed under: behavior, cancer, Evolutionary perspective, healing, health, lifestyle, self-healing | Tags: cancer, environmental toxins, genetics, glucose, health, Metabolic Theory, metabolism, mitochondria, nutrition, Somatic Mutation Theory, Warburg effect, wellness 2 CommentsErik Peper, PhD, BCB1 and Richard Harvey, PhD2
1 Biofeedback Health, Berkeley, CA and 2 Institute for Holistic Health, San Francisco State University
My aunt died of breast cancer and my mother was an identical twin. She and her sister resembled each other so closely that family members often couldn’t tell them apart. For the first 26 years of their lives, they both lived in Amsterdam. After they married, they moved to different cities. At the age of 82, my mother’s twin was diagnosed with breast cancer with metastasis to the brain and died that year. For my mother, this was one of the most devastating experiences of her life. It was as if half of her had died. Even with this loss, my mother never developed cancer and lived to the age of 95. The situation became even more complicated when my cousin (the daughter of my mother’s twin) also died of breast cancer at the age of 53, while my mother’s two daughters remained cancer-free. -Erik Peper, PhD. Reproduced by permission from Peper, Gorter and Faass (2026).
Cancer, with a capital ‘C’ along with each of the many kinds of malignant cellular processes is often understood primarily in terms of a disease driven by genetic mutations. This blog begins with observations from twin studies along with ongoing and emerging research suggests that genetics may represent susceptibility rather than destiny. In the case of identical twins, the experience of developing different cancer outcomes illustrates the importance of environmental exposures, lifestyle choices, specific metabolism interactions, immune functions, and particular cellular physiology.
The blog examines prevalent hypotheses about cancer processes which acknowledge interactions and functions such as immune, metabolic and evolutionary pressures. In particular, the paper argues in favor of revisiting the Warburg effect and the role of mitochondrial dysfunction in cancer development. The Warburg metabolic theory proposes that impaired mitochondrial energy production may drive cells toward an ancient survival pathway characterized by increased glucose fermentation, loss of specialized cellular function, and uncontrolled or unregulated proliferation. This perspective does not reject the strong role of genetics in cancer processes but rather places DNA and RNA within a broader biological context influenced by metabolism, epigenetics, and the environment. Understanding cancer as a systemic metabolic disorder may expand prevention strategies and complement existing treatments by emphasizing lifestyle, environmental, and metabolic interventions.
Twin Studies: Genetics as Predisposition, Not Destiny
For decades, research on cancer causes and treatments has been dominated by the Somatic Mutation Theory (SMT), which proposes that cancers arise through the accumulation of DNA mutations (Weinberg, 2023; Huang et al., 2025). This SMT framework has guided the “War on Cancer” and has led to remarkable advances in targeted therapies, chemotherapy, immunotherapy, and radiation treatments. These strategies have saved countless lives, yet they primarily focus on eliminating malignant cells rather than understanding why normal cells become malignant in the first place. While a variety of mutation-focused approaches has yielded remarkable therapeutic successes, one could expect that genetically identical individuals would develop the same or similar cancers.
Decades of twin research suggests otherwise. In the landmark Nordic Twin Study of Cancer, Lichtenstein and colleagues (2000) analyzed nearly 45,000 pairs of monozygotic (identical) and dizygotic (fraternal) twins from Sweden, Denmark, and Finland. If one identical twin developed cancer, the co-twin’s probability of developing the same cancer was about 10% which is much lower than expected if inherited genes alone determined cancer risk. Heritable factors accounted for only a portion of susceptibility (approximately 27% for breast cancer, 35% for colorectal cancer, and 42% for prostate cancer). The remaining risk was attributed largely to environmental influences, lifestyle, aging, and biological processes that occur during life (Lichtenstein et al., 2000; Mucci et al., 2016; Harris et al., 2019).
Both specific cancer investigations along with epidemiological findings across many places, people, and types of cancers suggest that genes create a predisposition, but they do not inevitably determine whether cancer develops. Instead, the cellular environment, metabolic health, environmental exposures, and epigenetic regulation strongly influence whether that predisposition is expressed. Simplistically stated, Genetics loads the gun and lifestyle and environment pulls the trigger (Peper et al., 2026).

The success of cancer treatments based on current oncology theories means that the Somatic Mutation Theory (SMT) provides a partial explanation of cancer processes. Extending the SMT of carcinogenesis to include Warburg-like theories has led to increasing evidence which suggests that metabolic dysfunction, mitochondrial injury, chronic inflammation, immune dysregulation, and environmental exposures all contribute to carcinogenesis. A useful framing of cancer risk related to inherent or heritable factors in comparison to non-intrinsic or non-genetic factors has been described by others (Brennan & Davey-Smith, 2022; Karras et al., 2024; Rahman et al., 2018; Wu et al., 2018).
For example, Wu et al., (2018) suggest that it is not possible to modify ‘random errors in DNA replication’ as an intrinsic risk factor, it is possible to partially modify endogenous risk factors related to inflammation or hormone production or fully mediate or modify directly and indirectly moderate non-genetic exogenous risk factors associated with toxic carcinogenic exposures that include exposures to some products from carcinogenic interactions with bacterial, viral, fungal and parasitic products, tobacco products, ultra-processed food and beverage products and chemicals (e.g., preservatives, pesticides, contaminants, dyes, non-nutritive chemicals such as sweeteners), industrial pollutant and chemical products (e.g. endocrine disrupting ‘forever’ chemicals such as in plastics), and lifestyle moderators such as lack of sleep, exercise, relaxation from mental ruminations and strain. A simplified model pathway would be: Risk of cancer is based on intrinsic genetic factors plus non-intrinsic endogenous and exogenous ‘epigenetic’ factors moderated by individual adaptive capacity to reduce endogenous or mitigate exogenous non-intrinsic factors.
Rather than competing explanations, mechanisms of cancerous disease processes may interact to determine whether genetically susceptible cells remain healthy or progress toward malignancy. These factors may explain that the overall cancer mortality has declined substantially over the past several decades and is predominantly due to the decreased tobacco use, earlier detection, and improvements in treatment. At the same time, the incidence of several cancers, including colorectal and breast cancer, has increased among younger adults (Siegel et al., 2025; American Cancer Society, 2024; Ugai et al., 2022; Lee, 2026). These trends suggest that additional biological and environmental factors deserve closer examination. Beyond regulating exposure to lifestyle factors such as tobacco products as a mediator of reduced cancer mortality, theories by Warburg and colleagues have pointed to metabolic regulation, including regulation of sugars, as a mediator in cancer mortality.
The Metabolic Origin: Revisiting the Warburg Effect
An alternative framework proposes that cancer is fundamentally a disorder of cellular metabolism. This concept dates back to Otto Warburg, who received the 1931 Nobel Prize in Physiology or Medicine for discovering that cancer cells exhibit a distinctive pattern of energy metabolism (Bononi et al., 2022; Otto, 2016; Nobel Prize Outreach, 2026). He showed that cancer cells rely predominantly on glucose fermentation, an anerobic process for making energy without oxygen (e.g. glucose splits into pyruvate and makes two adenosine triphosphate molecules) which is much less efficient than making energy through oxidative phosphorylation, even when oxygen is abundant in a cancer cell. The vast majority of cancerous cell growth depends on a less efficient glucose metabolism form of energy (Kim, 2017; Warburg, Negelein & Posener, 1924). The Warburg effect has been recognized as a hallmark of cancer for nearly a century (Seyfried & Chinopoulos, 2021).
Non-cancerous healthy cells mainly generate energy by producing ATP through oxidative phosphorylation within the mitochondria. Healthy cells are metabolically flexible and can generate energy from both glucose and free fatty acid oxidation (FAO). During periods of fasting, exercise, or carbohydrate restriction, triglycerides stored in adipose tissue are broken down into free fatty acids and glycerol (Eberle, 2013). The liver also converts free fatty acids into ketone bodies, which provide an efficient alternative fuel for the brain and many other tissues when glucose availability is reduced (Wakil & Abu-Elheiga, 2009; Edwards & Mohiuddin, 2023).
When mitochondrial respiration is chronically impaired by environmental toxins, oxidative stress, metabolic dysfunction, or other factors associated with carcinogenesis, cells may shift from efficient oxidative phosphorylation to a more primitive, glycolytic mode of energy production that can generate ATP in the absence of oxygen. Mitochondrial function can decline as people age when accumulation of reactive oxygen species which can directly harm mitochondrial DNA (Bondy, 2024; Cui et al., 2012; Madamanchi & Runge, 2007). In addition, mitochondrial function can also decline due to the indirect moderating effects of lifestyle choices (Caturano et al., 2025; Lemos et al., 2023; San-Millán, 2023).
As described by Miwa et al., (2022), when mitochondrial function declines, mitochondrial dysfunction can contribute to cellular senescence which is the hallmarks of aging. As a response healthy cells can progressively relinquishes their specialized role within the tissue and adopts characteristics of a more ancestral, less differentiated state (Zhang et al., 2025).
Zhang et al. (2025) suggests a few mechanisms which explain the shift of healthy cells away from specialized states towards a less differentiated state, such as shifts in the tricarboxylic acid cycle (TCA) which rely on healthy mitochondria to produce cofactors such as acetyl-CoA and positively charged Nicotinamide Adenine Dinucleotide (NAD+), along with drops in chromatin, inhibiting DNA and histone demthylases (locking chromatin in a hyper-methylated state, and an upregulation of glycolysis. Additionally, cells ‘sense’ when mitochondria have low energy production such as a high ratio of adenosine mono-phosphate or di-phosphate (AMP/ADP) to adenosine tri-phosphate (ATP), which then leads to the AMP-activated protein kinase (AMP-K) pathway (Mihaylova & Shaw, 2011). Finally, hypoxia-inducing factor (HIF) signaling is how cells ‘sense’ and adapt to changes in available oxygen, and HIF binds to DNA, activating specific genes (Huang et al., 2023). The Warburg theory suggests that when mitochondrial dysfunction directly or indirectly reduces oxidative phosphorylation, the cells shift energy production from the mitochondria to cytoplasmic glycolysis which is a hallmark of unicellular ‘ancestral’ organisms or more embryonic or stem-like cellular activity (Suomalainen, & Nunnari, 2024; Zong et al., 2024).
It is as if your cells suddenly forget they’re part of a team. Instead of working together like citizens in a well-organized society, they revert to their most primitive programming; the “me first” mentality of our single-celled ancestors. This is what happens in cancer where sophisticated multicellular cooperation gets hijacked by an ancient survival script buried deep in our biological software. Sonnenschein and Soto (1999) describe this process in their book The Society of Cells (1999), “the default state of cells is proliferation.” In other words, multiplication isn’t some aberrant behavior; it’s actually the factory setting when single cells began. Every cell carries this “go forth and multiply” command like prehistoric programming code.
In healthy tissue, cells have learned to override this ancient impulse. They’ve evolved sophisticated “stop” signals, quality control mechanisms, and cooperative protocols that keep the peace. Cancer occurs when these civilized controls break down, and cells revert to their evolutionary factory settings—endless growth, damn the consequences.
It’s as if your cells suddenly decide to ignore millions of years of evolutionary teamwork and go back to playing by the rules that worked when life was just lone microbes floating in primordial soup.
Under Survival Threat, Organisms Revert to Their Oldest Survival Mechanisms
The same regression process can be observed in human beings. When children experience overwhelming stress, they often revert to earlier developmental behaviors, such as becoming incontinent or seeking protection by hiding behind a parent. Similarly, when adults perceive an immediate threat to survival, the stress response is not always fight or flight. Instead, the body may enter a freeze response characterized by profound immobilization.
This freeze response represents an ancient survival strategy that is activated when the nervous system perceives extreme, life-threatening danger. In this state, heart rate slows, metabolism is reduced, and movement is inhibited through activation of the dorsal vagal complex which is the evolutionarily older branch of the vagus nerve according to polyvagal theory, (Porges, 2023). For reptiles and other primitive vertebrates, this physiological strategy can increase the likelihood of survival until the danger has passed.
Metabolic Theory in Context
A ‘metabolic perspective’ related to carcinogenicity, or related to reversion to more primitive types of behaviors, does not dismiss the importance of genetics. Rather, a metabolic perspective places genetic mutations within a broader biological framework in which metabolism, mitochondrial integrity, immune surveillance, environmental exposures, and epigenetic regulation interact to determine whether a cell remains healthy, or progresses toward malignancy. From this perspective, cancer represents more than the accumulation of genetic mutations. It reflects a regression to an ancient cellular survival program in which energy production and reproduction, rather than specialized function and cooperation with neighboring cells, becomes the overriding priority. Genetic mutations may therefore be viewed not only as the initiating a set of complex interactions that reflect causes of cancer but also as downstream consequences of chronic metabolic dysfunction and mitochondrial damage.
If cancer represents the activation of an evolutionarily ancient cellular survival program triggered by metabolic dysfunction, then interventions that improve metabolic health can reduce risk associated with carcinogenesis which complement conventional treatment. As Dang (2012) points out, “excessive caloric intake is associated with an increased risk for cancers, while caloric restriction is protective, perhaps through clearance of mitochondria or mitophagy, thereby reducing oxidative stress.”
One practical implication is for people to follow often repeated advice: decrease the availability of rapidly absorbed carbohydrates by minimizing the consumption of sugar-sweetened beverages, refined starches, and ultra-processed foods while emphasizing whole, nutrient-dense foods. Broadly stated, such dietary changes in sugar intake can improve metabolic resilience, reduce chronic inflammation, and create a physiological environment that is less favorable for the metabolic adaptations observed in many cancers. Although additional clinical research continues to provide evidence supporting the effectiveness of ‘lifestyle’ and epigenetic strategies across different cancer types, the metabolic perspective offers a compelling framework for prevention and adjunctive therapy.
The metabolic theory of cancer based upon the Warburg effect offers hope in treatment by reducing glucose availability may help slow the growth of some cancers. The process is described clearly by Professor Thomas Seyfried of Boston College (Seyfried et al., 2014; Seyfried et al., 2021). His metabolic theory remains an active area of research, however is not the current consensus view on cancer biology. Consider watching the compelling overview of this metabolic theory presented by Professor Thomas Seyfried’s in his YouTube lecture, Cancer as a Metabolic Disease,
What can you do to reduce cancer risk and support healing
The metabolic theory of cancer presented in this paper suggests behavioral and lifestyle strategies to reduce cancer risk and slow or prevent cancer growth. Simply stated, reduce excessive glucose availability which becomes the main energy source for cancer cells. Clinical improvement may be possible if cancer cells are put on a diet (Stetka, 2016). Changing diet is one component to optimize what you can do to reduce cancer risk, support our immune system to promote healing and optimize health although the outcome is not totally in our hands. Implement the following environmental and lifestyle behaviors promote health and healing.
Reduce and eliminate ultra-processed foods, simple carbohydrates and sugar. These increase the risk of cancers by 20 to 50 percent. Sadly, many patients undergoing chemo and radiation therapy and have difficulty with swallowing, are recommended to drink oral caloric rich supplements (such as Ensure Plus or Boost Very High Calorie) that are specially formulated to provide dense calories and protein in a small volume. They contain between 15 to 22 grams of sugar (1 to 2 tablespoons of sugar) in an 8 ounce serving– the sugar which paradoxically encourages cancer growth.
Reduce and eliminate exposure to endocrine disruptors. These are chemicals that can mimic, block, or interfere with the body’s hormones, due to higher estrogen levels (in milk and beef, for example) and pesticides (some of which act as estrogen mimics). This means eliminating as much as possible all plastics and eat mainly organic foods that do not contain herbicides or pesticides. If possible, eat organic foods.
Reduce air and water pollution that are known factors to cause cancers. This means use air and water filters at home since more than 50% of drinking water in the United States contain cariogenic substances and air pollution from car or fires are harmful.
Increase physical activity. Movement/exercise is important because that reduces lymphatic circulation and blood flow, impacting the immune system in the long term.
For detailed information and recommendations what you can use to reduce cancer risk and optimize health, see our book, Cancer Reconsidered-Why Environment, Lifestyle and Immunity Matter more than we thought.
Additional relevant blogs
References
American Cancer Society. (2024). Cancer facts & figures 2024. https://doi.org/10.3322/caac.21820
Bondy, S. C. (2024). Mitochondrial dysfunction as the major basis of brain aging. Biomolecules, 14(4), 402. https://doi.org/10.3390/biom14040402
Bononi, G., Masoni, S., Di Bussolo, V., Tuccinardi, T., Granchi, C., & Minutolo, F. (2022). Historical perspective of tumor glycolysis: A century with Otto Warburg. Seminars in Cancer Biology, 86, 325–333. https://doi.org/10.1016/j.semcancer.2022.07.003
Brennan, P., & Davey-Smith, G. (2022). Identifying novel causes of cancers to enhance cancer prevention: New strategies are needed. Journal of the National Cancer Institute, 114(3), 353–360. https://doi.org/10.1093/jnci/djab204
Caturano, A., Rocco, M., Tagliaferri, G., Piacevole, A., Nilo, D., Di Lorenzo, G., Iadicicco, I., Donnarumma, M., Galiero, R., Acierno, C., Sardu, C…., (2025). Oxidative stress and cardiovascular complications in type 2 diabetes: From pathophysiology to lifestyle modifications. Antioxidants, 14(1), Article 72. https://doi.org/10.3390/antiox14010072
Cui, H., Kong, Y., & Zhang, H. (2012). Oxidative stress, mitochondrial dysfunction, and aging. Journal of Signal Transduction, 2012, Article 646354. https://doi.org/10.1155/2012/646354
Dang, C. V. (2012). Links between metabolism and cancer. Genes & Development, 26(9), 877–890. https://doi.org/10.1101/gad.189365.112
Eberle, S. G. (2013). The body’s fuel sources. In Endurance sports nutrition (3rd ed., pp. 31–53). Human Kinetics.https://us.humankinetics.com/blogs/excerpt/the-bodys-fuel-sources
Edwards, M., & Mohiuddin, S. S. (2023, July 17). Biochemistry, lipolysis. In StatPearls. StatPearls Publishing. https://www.ncbi.nlm.nih.gov/books/NBK560564/
Hanahan, D. (2026). The hallmarks of cancer: 25 years guiding discovery and therapy. Cell, 189. https://www.cell.com/cell/fulltext/S0092-8674(26)00334-X
Hanahan, D., & Weinberg, R. A. (2011). Hallmarks of cancer: The next generation. Cell, 144(5), 646–674. https://doi.org/10.1016/j.cell.2011.02.013
Harris, J. R., Hjelmborg, J., Adami, H.-O., Czene, K., Mucci, L., & Kaprio, J. (2019). The Nordic Twin Study on Cancer (NorTwinCan). Twin Research and Human Genetics, 22(6), 817–823. https://doi.org/10.1017/thg.2019.71
Huang, S., Soto, A. M., & Sonnenschein, C. (2025). The end of the genetic paradigm of cancer. PLOS Biology, 23(3), Article e3003052. https://doi.org/10.1371/journal.pbio.3003052
Huang, X., Zhao, L., & Peng, R. (2023). Hypoxia-inducible factor 1 and mitochondria: An intimate connection. Biomolecules, 13(1), Article 50. https://doi.org/10.3390/biom13010050
Karras, P., Black, J. R. M., McGranahan, N., & Marine, J.-C. (2024). Decoding the interplay between genetic and non-genetic drivers of metastasis. Nature, 629(8012), 543–554. https://doi.org/10.1038/s41586-024-07302-6
King, M.-C., Marks, J. H., & Mandell, J. B. (2003). Breast and ovarian cancer risks due to inherited mutations in BRCA1 and BRCA2. Science, 302(5645), 643–646. https://doi.org/10.1126/science.1088759
Kim, S. Y. (2017). Cancer energy metabolism: Shutting power off cancer factory. Biomolecules & Therapeutics, 26(1), 39–44. https://doi.org/10.4062/biomolther.2017.184
Lee, I. (2026). The increase of early-onset colorectal cancer: New insights and emerging hypotheses. Cancer Control, 33, Article 10732748261432271. https://doi.org/10.1177/10732748261432271
Lemos, G. O., Torrinhas, R. S., & Waitzberg, D. L. (2023). Nutrients, physical activity, and mitochondrial dysfunction in the setting of metabolic syndrome. Nutrients, 15(5), Article 1217. https://doi.org/10.3390/nu15051217
Lichtenstein, P., Holm, N. V., Verkasalo, P. K., Iliadou, A., Kaprio, J., Koskenvuo, M., Pukkala, E., Skytthe, A., & Hemminki, K. (2000). Environmental and heritable factors in the causation of cancer: Analyses of cohorts of twins from Sweden, Denmark, and Finland. New England Journal of Medicine, 343(2), 78–85. https://doi.org/10.1056/NEJM200007133430201
Madamanchi, N. R., & Runge, M. S. (2007). Mitochondrial dysfunction in atherosclerosis. Circulation Research, 100(4), 460–473. https://doi.org/10.1161/01.RES.0000258450.44413
Mihaylova, M. M., & Shaw, R. J. (2011). The AMPK signalling pathway coordinates cell growth, autophagy and metabolism. Nature Cell Biology, 13, 1016–1023. https://doi.org/10.1038/ncb2329
Miwa, S., Kashyap, S., Chini, E., & von Zglinicki, T. (2022). Mitochondrial dysfunction in cell senescence and aging. Journal of Clinical Investigation, 132(13), Article e158447. https://doi.org/10.1172/JCI158447
Mucci, L. A., Hjelmborg, J. B., Harris, J. R., et al. (2016). Familial risk and heritability of cancer among twins in Nordic countries: The Nordic Twin Study of Cancer (NorTwinCan) collaboration. JAMA, 315(1), 68–78. https://doi.org/10.1001/jama.2015.17703
Mukherjee, S. (2025). The emperor of all maladies: A biography of cancer. Scribner. https://www.amazon.com/Emperor-All-Maladies-Biography-Cancer/dp/1668047039/
National Institutes of Health. (2025, April 21). Annual report to the nation: Cancer deaths continue to decline [Media advisory]. NIH News Releases. https://www.nih.gov/news-events/news-releases/annual-report-nation-cancer-deaths-continue-decline
Nobel Prize Outreach. (2026). Otto Warburg—Biographical. NobelPrize.org. Retrieved August 11, 2026, from https://www.nobelprize.org/prizes/medicine/1931/warburg/biographical/
Otto, A. M. (2016). Warburg effect(s)—A biographical sketch of Otto Warburg and his impacts on tumor metabolism. Cancer & Metabolism, 4(1), Article 5. https://doi.org/10.1186/s40170-016-0145-9
Peper, E., Gorter, R., & Faass, N. (2026). Cancer reconsidered: Why environment, lifestyle, and immunity matter more than we thought. BiofeedbackHealth/Regent Press. https://www.amazon.com/Cancer-Reconsidered-Environment-Lifestyle-Immunity/dp/1587907402
Porges, S. W. (2023). The vagal paradox: A polyvagal solution. Comprehensive Psychoneuroendocrinology, 16, Article 100200. https://doi.org/10.1016/j.cpnec.2023.100200
Rahman, M. S., Suresh, S., & Waly, M. I. (2018). Risk factors for cancer: Genetic and environment. In Bioactive Components, Diet and Medical Treatment in Cancer Prevention (pp. 1-23). Springer International Publishing. https://doi.org/10.1007/978-3-319-75693-6_1
San-Millán, I. (2023). The key role of mitochondrial function in health and disease. Antioxidants, 12(4), Article 782. https://doi.org/10.3390/antiox12040782
Seyfried, T. N., & Chinopoulos, C. (2021). Can the mitochondrial metabolic theory explain better the origin and management of cancer than can the somatic mutation theory? Metabolites, 11(9), Article 572. https://doi.org/10.3390/metabo11090572
Seyfried, T. N., Flores, R. E., Poff, A. M., & D’Agostino, D. P. (2014). Cancer as a metabolic disease: Implications for novel therapeutics. Carcinogenesis, 35(3), 515–527. https://doi.org/10.1093/carcin/bgt480
Seyfried, T. N., Lee, D. C., Duraj, T., et al. (2025). The Warburg hypothesis and the emergence of the mitochondrial metabolic theory of cancer. Journal of Bioenergetics and Biomembranes, 57, 57–83. https://doi.org/10.1007/s10863-025-10059-w
Siegel, R. L., Kratzer, T. B., Giaquinto, A. N., Sung, H., & Jemal, A. (2025). Cancer statistics, 2025. CA: A Cancer Journal for Clinicians, 75(1), 10–45. https://doi.org/10.3322/caac.21871
Sonnenschein, C., & Soto, A. M. (1999). The society of cells: Cancer and control of cell proliferation. BIOS Scientific Publishers. https://www.amazon.com/Society-Cells-Carlos-Sonnenschein/dp/1859962769
Stetka, B. (2016, March 5). Fighting cancer by putting tumor cells on a diet. NPR. https://www.npr.org/sections/health-shots/2016/03/05/468285545/fighting-cancer-by-putting-tumor-cells-on-a-diet
Suomalainen, A., & Nunnari, J. (2024). Mitochondria at the crossroads of health and disease. Cell, 187(11), 2601–2627. https://doi.org/10.1016/j.cell.2024.04.037
Ugai, T., Sasamoto, N., Lee, H. Y., Ando, M., Song, M., Tamimi, R. M., … Ogino, S. (2022). Is early-onset cancer an emerging global epidemic? Current evidence and future implications. Nature Reviews Clinical Oncology, 19(10), 656–673. https://doi.org/10.1038/s41571-022-00672-8
Wakil, S. J., & Abu-Elheiga, L. A. (2009). Fatty acid metabolism: Target for metabolic syndrome. Journal of Lipid Research, 50(Suppl.), S138–S143. https://doi.org/10.1194/jlr.R800079-JLR200
Warburg, O., Negelein, E. & Posener, K. Versuche an Überlebendem Carcinomgewebe. Klin Wochenschr 3, 1062–1064 (1924). https://doi.org/10.1007/BF01736087
Weinberg, R. A. (2023). The biology of cancer. W. W. Norton & Company. https://www.amazon.com/Biology-Cancer-Robert-Weinberg/dp/0393887650
Wu, S., Zhu, W., Thompson, P., & Hannun, Y. A. (2018). Evaluating intrinsic and non-intrinsic cancer risk factors. Nature Communications, 9(1), Article 3490. https://doi.org/10.1038/s41467-018-05467-z
Zhang, Y., Tang, J., Jiang, C., Yi, H., Guang, S., Yin, G., & Wang, M. (2025). Metabolic reprogramming in cancer and senescence. MedComm, 6(3), Article e70055. https://doi.org/10.1002/mco2.70055
Zong, Y., Li, H., Liao, P., et al. (2024). Mitochondrial dysfunction: Mechanisms and advances in therapy. Signal Transduction and Targeted Therapy, 9, 124. https://doi.org/10.1038/s41392-024-01839-8
Edited with the help of ChatGPT
Can Your Daily Choices Influence Cancer Risk and Recovery?
Posted: June 27, 2026 Filed under: behavior, Breathing/respiration, cancer, emotions, healing, health, lifestyle, Nutrition/diet, Pain/discomfort, self-healing, stress management, Uncategorized | Tags: diet, endocrine disregulators, environmental toxins, glucose monitors, health, Immune function, mental-health, nutrition, pollution, Quality of life, regeneration, resilience, social support, wellness 1 CommentWhat if the way you eat, move, sleep, manage stress, and connect with others could influence your body’s ability to prevent disease and support healing?
Most of us have been taught to think of cancer primarily as a genetic disease. Yet an expanding body of scientific research tells a more hopeful story: while genes matter, they are only part of the picture. Our environment, lifestyle, immune system, and even the quality of our relationships can profoundly influence health.
These are the questions explored in the newly published book Cancer Reconsidered: Why Environment, Lifestyle, and Immunity Matter More than We Thought, by Erik Peper, Robert Gorter, and Nancy Faass.

Written for people living with cancer, their families, healthcare professionals, and anyone interested in optimizing health, the book translates decades of scientific research into practical, evidence-based strategies that readers can use in everyday life.
Rather than viewing cancer through a single lens, Cancer Reconsidered brings together insights from conventional medicine with evidence-based complementary approaches. The authors explore how nutrition, physical activity, stress, sleep, environmental exposures, immune function, and social support interact to influence both cancer risk and the body’s remarkable capacity for repair and resilience.
One of the book’s central messages is both simple and empowering: although we cannot change our genes, we can often change the conditions in which our genes are expressed. Daily choices matter. Healthy habits can strengthen the body’s natural defenses, reduce inflammation, support immune function, and improve quality of life.
A particularly practical chapter explores blood sugar regulation and metabolism. Using continuous glucose monitors (CGMs) together with smartphone apps, readers can observe in real time how different foods, exercise, stress, and sleep affect their glucose levels. Instead of following one-size-fits-all advice, they become active investigators of their own health, discovering what works best for their unique physiology.
Throughout the book, the emphasis is not on fear, but on possibility. Scientific evidence increasingly shows that hope, meaningful social connections, regular movement, nourishing food, restorative sleep, effective stress management, and resilience are not simply “nice ideas”—they are biological factors that can significantly influence health and well-being.
Cancer Reconsidered invites readers to move beyond the question, “What causes cancer?” and instead ask, “What can I do today to create the best possible conditions for health?” It offers a thoughtful, scientifically grounded roadmap for anyone seeking to answer that question.
Cancer Reconsidered: Why Environment, Lifestyle, and Immunity Matter More than We Thought is now available on Amazon in paperback and and affordable ebook Kindle editions. https://www.amazon.com/s?k=cancer+reconsidered
Improve fertility and decrease cancer risk: THE PLASTIC DETOX
Posted: May 7, 2026 Filed under: behavior, cancer, health, Uncategorized | Tags: bisphenols, BPA, endocrine disruptors, environment, environmental pollution, fertility, health, microplastics, plastics, polution, pregnancy, sperm, sustainability, wellness 4 CommentsAre you concerned about your or your children’s future fertility, or do you want to get pregnant?
Do you want to reduce your cancer risk?
In 1962, Rachel Carson published the seminal, groundbreaking book Silent Spring, which brought public awareness to the harmful effects of environmental pollution (Carson, 1962). In many cases, public awareness of environmental pollution has been driven by observations and research involving people living near or on toxic waste sites, such as the infamous Love Canal in Niagara Falls, New York. Residents living in this area experienced a significantly higher risk of developing bladder, kidney, and other cancers due to contaminated water and soil (Gensburg et al., 2009).
Equally important is the impact of environmental pollution, including ongoing exposure to plastics, on health and embryological development. Many studies report that downstream pollution from agriculture, chemical plants, and sewage causes significant harm, ranging from limb deformities in amphibians (Taylor et al., 2005) to disruptions in human reproductive health. For example, microplastics have been shown to impair ovarian function, decrease fertility rates, and disrupt hormone levels in female subjects and their offspring’s health (Inam, 2025).
Research findings suggest that many human-made chemicals reduce fertility and increase cancer risk. Many chemicals in plastics (e.g., bisphenols (BPA, BPS, BPF), phthalates, flame retardants, and nonylphenol) are endocrine disruptors contributing to reduced fertility and can act as carcinogenic initiators or promoters (NIH, 2026). Ongoing exposure to plastics is one of several factors that may contribute to declines in fertility and earlier onset of cancers such as breast and prostate cancer in younger populations.
The recently released Netflix documentary The Plastic Detox offers an eye-opening exploration of the hidden dangers of the chemicals in plastics in our homes and daily lives and how it may impact fertility. It highlights concerns ranging from hormone disruption—which may contribute to declining fertility worldwide—to increasing rates of cancer and earlier occurrences of heart attack and stroke.
In the documentary, Professor Shanna H. Swan, a research scientist at the Icahn School of Medicine at Mount Sinai in New York City, explains how microplastics and their associated chemicals may affect our health—and what steps we can take to reduce our exposure. Although the documentary is not a randomized controlled trial and it doesn’t disentangle the possible placebo effects that arise when people shift their beliefs about the cause of infertility (for example, “it’s not my fault; it’s the plastics”), its central message is valid. From a psychophysiological perspective, how we interpret the causes of our health challenges can shape both our stress responses and our sense of agency.
Even with its scientific limitations, the film points toward an important concern: that environmental exposures, including plastics, play an important role in reproductive health. I also wonder whether some of the sharp “scientific critiques” of the documentary reflect more than scientific caution alone. History reminds us that industries whose profits are threatened have often worked to amplify uncertainty and delay regulation as the tobacco industry famously did for decades despite mounting evidence of harm (Maani et al., 2022; Oreskes & Conway, 2010).
I strongly recommend watching the documentary and taking steps to reduce exposure to plastics and other environmental toxins (such as glyphosate and the chemicals in air and water pollution) to support your health and that of your children. Watch it on Netflix: https://www.netflix.com/title/82074244

Listen to the in-depth discussion of this blog created with Google NotebookLM
References
Carson, R. (1962). Silent Spring. Houghton Mifflin Co. https://www.amazon.com/Silent-Spring-Rachel-Carson/dp/0395075068
Gensburg, L. J., Pantea, C., Fitzgerald, E., Stark, A., Hwang, S. A., & Kim, N. (2009). Mortality among former Love Canal residents. Environmental Health Perspectives, 117(2), 209–216. https://doi.org/10.1289/ehp.11350
Inam, Ö. (2025). Impact of microplastics on female reproductive health: Insights from animal and human experimental studies: A systematic review. Archives of Gynecology and Obstetrics, 312(1), 77–92. https://doi.org/10.1007/s00404-024-07929
Maani, N., van Schalkwyk, M. C. I., Filippidis, F. T., Knai, C., & Petticrew, M. (2022). Manufacturing doubt: Assessing the effects of independent vs. industry-sponsored messaging about the harms of fossil fuels, smoking, alcohol, and sugar-sweetened beverages. SSM – Population Health, 17, 101009. https://doi.org/10.1016/j.ssmph.2021.101009
NIH. (2026). Endocrine disruptors. National Institute of Environmental Health Sciences. Retrieved May 7, 2026, from https://www.niehs.nih.gov/health/topics/agents/endocrine/index.cfm
Oreskes, N., & Conway, E. M. (2010). Merchants of doubt: How a handful of scientists obscured the truth on issues from tobacco smoke to global warming. Bloomsbury Press. https://www.amazon.com/Merchants-Doubt-Handful-Scientists-Obscured/dp/1608193942/
Taylor, B., Skelly, D., Demarchis, L. K., Slade, M. D., Galusha, D., & Rabinowitz, P. M. (2005). Proximity to pollution sources and risk of amphibian limb malformation. Environmental Health Perspectives, 113(11), 1497–1501. https://doi.org/10.1289/ehp.7585
Tell Me Where It Hurts
Posted: April 24, 2026 Filed under: attention, behavior, biofeedback, Breathing/respiration, cancer, education, emotions, healing, health, Neck and shoulder discomfort, Pain/discomfort, self-healing, surgery | Tags: health, meditation, mental-health, mindfulness, wellness 2 Comments
In my biofeedback practice, I’ve repeatedly seen that healing rarely comes from a single technique. It emerges from observation, integration and practicing and integrating skills in daily life. When clients learn to combine biofeedback with other strategies to make it their own such as slower, more coherent breathing, guided imagery, shifts in internal dialogue, and practical lifestyle changes, something important happens: the body begins to reorganize itself toward health.
Again and again, clients report meaningful changes. Stress symptoms, headaches, eye problem, neck shoulder and back pain decrease or disappear. Gastrointestinal symptoms often fade out. Anxiety loosens its grip. Asthma improves. Chronic neck, shoulder, and pelvic pain diminish. These are not isolated outcomes; they reflect a pattern. When people gain the skills to regulate their physiology and reinterpret their internal experience, decrease in symptoms often follow (see the list of articles that describe successful outcomes).
Even though many of my clients benefit, I am continually searching for strategies and approaches that can improve their health and reduce suffering and for materials that I can recommend to them.
Now when I see a client who reports pain or who takes care of someone with pain, the first thing I do is to recommend the book, Tell Me Where It Hurts, by Rachel Zoffness, PhD, a leading pain expert and psychologist. The book offers a clear, science-based framework grounded in modern neuroscience, yet conveyed through compelling human stories. Her work aligns closely with what we observe in biofeedback: pain is not simply a signal from injured tissue. It is an experience shaped by the interaction of body, brain, emotions, beliefs, culture and context.
She makes a crucial point that pain may begin with injury or illness, but it is always modulated by factors such as physiological state, emotional meaning, cognitive interpretation, and social and cultural influences. In other words, pain is real, but it is also dynamic and changeable.
The first step she emphasizes is education. When people understand how pain actually works, fear often decreases. From there, the task becomes identifying what amplifies pain and what reduces it and then systematically strengthening the factors and behaviors and skills that support recovery.
One striking story captures this perfectly: a construction worker jumps from a plank onto what appears to be a 7” nail, which is driven through his boot. He experiences excruciating pain and is rushed to the emergency room. Yet when the boot is removed, the nail is found to have passed cleanly between his toes—there is no tissue damage. The pain was real, but it was driven by perception and expectation. This is not an anomaly; it is a powerful illustration of how the brain constructs pain.
Equally compelling are the recovery stories. Patients with severe chronic pain that continue and got worse after failed surgeries, long-term disability, or even amputation, find relief not through more invasive procedures or medication alone, but through learning how to retrain their nervous system. In many of these cases, even opioids had failed to provide meaningful relief. What made the difference was a shift in understanding, combined with evidence-based self-regulation strategies. They are no longer abstract ideas; they are lived experiences.
The larger message is both simple and profound: pain can change. And when people are given the right framework and tools, they can actively participate in that change. For anyone living with pain, or working professionally with those who do, this book is not just informative. It is practical, empowering, and, in many cases, transformative.
This is the book to read if you have pain or care for someone with pain. It is also the book every therapist who works with people with pain should read and recommend to their clients.

Zoffness, R. (2026). Tell me where it hurts. Grand Central. https://www.amazon.com/Tell-Me-Where-Hurts-Science/dp/1538758148/
I recommend listening to the excellent podcast generated with Google NotebookLM, which thoughtfully expands upon and clarifies the underlying research.isten to the expanded podcast based on this blog and created with Google Notebook LM.
The following blog has a link to a superb podcast featuring Rachel Zoffness.
Then listen to the podcast from Dolorology (PAIN) Encore with Dr. Rachel Zoffness. https://www.alieward.com/ologies/dolorologyencore
Examples of integrated biofeedback outcomes
Peper, E. (2015). Pain as a Contextual Experience. Townsend Letter-The Examiner of Alternative Medicine, 388, 63-66. https://townsendletter.com/peper-contextual-pain-09-11-15/
Peper, E., Booiman, A. & Harvey, R. (2025a). Pain-There is Hope. Biofeedback, 53(1), 1-9. http://doi.org/10.5298/1081-5937-53.01.16 Also, republished in Townsend Letter-Innovative Health Perspectives. https://townsendletter.com/pain-there-is-hope/
Peper, E., Chen, S., Heinz, N. & Harvey, R. (2023). Hope for menstrual cramps (dysmenorrhea) with breathing. Biofeedback,. 51(2), 44–51. https://doi.org/10.5298/1081-5937-51.2.04
Peper, E. & Cohen, T. (2017). Inhale to breathe away pelvic floor pain and enjoy intercourse. Biofeedback, 45(1), 21–24. https://doi.org/10.5298/1081-5937-45.1.04
Peper, E., Cosby, J., & Almendras, M. (2022a). Healing chronic back pain. NeuroRegulation, 9(3), 164–172. https://doi.org/10.15540/nr.9.3.164
Peper, E., Covell, A., & Matzembacker, N. (2021). How a chronic headache condition became resolved with one session of breathing and posture coaching. NeuroRegulation, 8(4), 194–197. https://doi.org/10.15540/nr.8.4.194
Peper, E. & Harvey, R. (2008). From technostress to technohealth. Japanese Journal of Biofeedback Research, 35(2), 107-114. https://www.jstage.jst.go.jp/article/jjbf/35/2/35_KJ00005060045/_pdf
Peper, E., Harvey, R., Chen, S., & Heinz, N. (2025b). Practicing diaphragmatic breathing reduces menstrual symptoms both during in-person and synchronous online teaching. Applied Psychophysiology and Biofeedback. https://do.org/10.1007/s10484-025-09745-7
Peper, E., Harvey, R., Cuellar, Y., & Membrila, C. (2022b). Reduce anxiety. NeuroRegulation, 9(2), 91–97. https://doi.org/10.15540/nr.9.2.91
Peper, E., Martinez Aranda, P., & Moss, E. (2015). Vulvodynia treated successfully with breathing biofeedback and integrated stress reduction: A case report. Biofeedback. 43(2), 103-109. https://doi.org/10.5298/1081-5937-43.2.04
Peper, E., Mason, L., Harvey, R., Wolski, L, & Torres, J. (2020). Can acid reflux be reduced by breathing? Townsend Letters-The Examiner of Alternative Medicine, 445/446, 44-47. https://www.townsendletter.com/article/445-6-acid-reflux-reduced-by-breathing/
Peper, E., Oded, Y., & Harvey, R. (2024). Quick somatic rescue techniques when stressed. Biofeedback, 52(1), 18–26. https://doi.org/10.5298/982312
Peper, E. & Tibbitts, V. (2003). Protocol for the treatment of asthma. In: Zheng, Y. (ed). Clinical Practice of Biofeedback. Beijing: High Education Press (HEP). 163-176. ISBN 7-04-011420-8 https://biofeedbackhealth.org/wp-content/uploads/2011/01/protocol-for-asthma-treatemtn2001-china.pdf
Peper, E. & Yirmiyahu, D. (2023). Transforming a “bad eye” to an “amazing eye”: a case report and protocol. Townsend Letters. The Examiner of Alternative Medicine, Saturday, July 29, 2023 https://townsendletter.com/transforming-a-bad-eye-to-an-amazing-eye-a-case-report-and-protocol/
Breathing for Health: Four Part Audio Series for Regeneration and Well-Being
Posted: March 12, 2026 Filed under: attention, behavior, Breathing/respiration, CBT, emotions, healing, health, meditation, mindfulness, Pain/discomfort, relaxation, self-healing, stress management, Uncategorized | Tags: audio files, health, meditation, mental-health, mindfulness, wellness 1 CommentAdapted from Peper, E. (1990). Breathing for Health with Biofeedback. Montreal: Thought Technology Ltd and produced by Larry Klein.

Breathing is the most intimate rhythm of life. From the moment we are born until our last breath, our breath is always there—quietly sustaining us. And yet, most of the time, we are unaware of how we breathe or how profoundly it shapes our health. Learn how to use your breath to optimize your health and enhance your well-being.
Dysfunctional breathing patterns contribute significantly to a range of illnesses, ranging from chronic pain and anxiety to fatigue and stress-related disorders. For example, when anxious, breathing often becomes rapid and shallow; when calm, breathing tends to slow and deepen. Symptoms can often be reduced, and health, resilience, and a deep sense of well-being can be enhanced after mastering and implementing effortless breathing. Breathing affects the mind, body, emotions, and spirit; when you change your breathing, you change your state of being.
The audio series by Erik Peper was conceived and produced by Larry Klein co-founder of Thought Technology, Ltd in 1990 to make the science and practice of breathing with biofeedback accessible to everyone. Although it was recorded more than 35 years ago, the principles and instructions remain as relevant and evidence-based today as they were then.
It was designed to help you observe your own breathing patterns and cultivate the foundational skill of effortless diaphragmatic breathing. Even more importantly, it guides you in integrating this breathing pattern into daily activities so that it becomes your default—whether you are working, speaking, exercising, or resting.
The discussion and guided practices are both simple and profound. When you change how you breathe, you change how you regulate yourself. Breathing both reflects and influences your physiology, emotions, and cognitions—often outside of conscious awareness.
As you listen to and practice the techniques in this four-part audio series, you will develop greater awareness, appreciation, and mastery of effortless breathing. Enjoy applying these practices in everyday life until they become automatic. Like any skill, effortless breathing is learned through gentle, consistent practice—practice makes permanent.
Part 1: Background Information on Breathing
Listen once to understand the scientific foundations and underlying rationale
Part 2: Learning Slow Diaphragmatic Breathing
Listen repeatedly and practice consistently until the skill becomes natural, effortless, and reliable.
Part 3: Integrating Breathing in All Conditions
Alternate between Parts 2 and 3. Practice during everyday activities so the skill generalizes beyond formal sessions and becomes your default way of breathing.
Part 4: Integrating Breathing, Imagery and Meditation for Health
Experience how guided imagery and meditative awareness deepen and amplify the benefits of effortless breathing.
Additional Recommended Blogs to Support the Learning and Generalization of Effortless Breathing
Additional Recommended Blogs: How Breathing Can Help Relieve Pain
Corporations: The new(old) disease vectors as they choose profits over health
Posted: February 24, 2026 Filed under: Breathing/respiration, cancer, health | Tags: cancer, environment, environmental toxins, food, health, herbicides, investigative reporting, nutrition, pollution, public health, smoking, wellness 1 Comment
“We can invest in preventing illness now by reducing our exposure to environmental toxins — or we can pay a far higher price later trying to treat the resulting chronic and often debilitating diseases.”
Ever since the 1962 publication of Rachel Carson’s groundbreaking book, Silent Spring, which documented the harm environmental pollution caused, government has, often reluctantly, set limits intended to protect Americans from exposure to harmful chemicals in our food, air and water (Carson, 1964). These regulations did not emerge easily. As the governmental regulations were being proposed and implemented, they were consistently challenged by the very large corporations that manufactured and profited from these chemicals.
History reminds us how slowly public health protections can unfold. Consider how long it took for smoking to be prohibited in public spaces even though the harmful effects had been documented since the 1950s (Doll and Hill, 1954; Doll & Hill, 1964; Wynder & Graham,1985). For decades, the science was clear, yet policy and governmental actions were delayed. Only in the early 2000s did many states began banning smoking in workplaces, restaurants, and bars. The shift in public policy saved many lives and the reduction in smoking has been the major reason for the decrease in cancer mortality over the last twenty-five years.
We are going backwards
The Trump administration has rescinded the 2009 U.S. Environmental Protection Agency endangerment finding on greenhouse gases, loosening vehicle emission standards, and weakening pollution controls on power plants and oil and gas operations (Tabuchi, 2026). The health consequences may not appear immediately; however, they are predictable. The increased exposure today will again contribute to increased rates of cancer, respiratory illness, cardiovascular disease, and developmental disorders tomorrow.
To understand how the government regulations have been revised so that once again Americans will be more exposed to toxins in their food, air, and water, read the superb investigative report published by U.S. Right to Know whose mission is to pursuing truth and transparency for public health.
Their most recent report, Tracing Bayer’s ties to power in Trump’s Washington, describes in detail the hidden social connections, lobbying and political donations that lead “The White House to invokes the Defense Production Act to guarantee supplies of elemental phosphorus and glyphosate-based herbicides. Regulators reapprove dicamba, a Bayer herbicide twice blocked by federal courts, and clear the way for new pesticides containing toxic, persistent PFAS “forever” chemicals (Malkan, 2026).“
When regulatory safeguards weaken, corporations can once again function as disease vectors-not through infection, but through environmental exposure. By loosening the pollution standards, federal policy will negatively affect the health of both present and future generations.
I encourage you to explore many superb investigative reports and practical suggestions how to avoid these toxins exposure that are available on U.S. Right to Know website:
One exposure. Twenty generations later, the damage is still unfolding
Glyphosate: Cancer, liver disease, endocrine disruption and other health concerns
Big Food ‘transparency’ campaign seeks to block tough new food safety laws
Ultra-processed foods damage health in ways that calories don’t explain, new study says
Listen to the expanded podcast based upon this blog and created by Google Notebook LM.
See also the following blogs
References
Carson, R. (1962). Silent spring. Houghton Mifflin. https://www.amazon.com/Silent-Spring-Rachel-Carson/dp/B002E8JF6G/
Doll, R., & Hill, A. B. (1954). The mortality of doctors in relation to their smoking habits: A preliminary report. British Medical Journal, 1(4877), 1451–1455. https://doi.org/10.1136/bmj.1.4877.1451
Doll, R., & Hill, A. B. (1964). Mortality in relation to smoking: Ten years’ observations of British doctors. British Medical Journal, 1(5396), 1460–1467. https://doi.org/10.1136/bmj.1.5396.1460
Malkan, S. (2026). Tracing Bayer’s ties to power in Trump’s Washington. U.S. Right to Know. Accessed February 24, 2026. https://usrtk.org/pesticides/tracing-bayers-ties-to-power-in-trumps-washington/
Tabuchi, H. (2026). Historic Climate Rollback Makes U.S. a Global Outlier on Tailpipe Rules. The New York Times, February 16, 2026. Accessed February 24, 2026 https://www.nytimes.com/2026/02/16/climate/endangerment-finding-auto-emissions-regulations.html
Wynder, E.L., & Graham, A. (1985). JAMA, 253 (20), 2986-2994. https://doi.org/10.1001/jama.1985.03350440064033
Reduce Interpersonal Stress*
Posted: December 4, 2025 Filed under: attention, behavior, Breathing/respiration, CBT, emotions, Exercise/movement, healing, health, meditation, mindfulness, Pain/discomfort, stress management | Tags: health, mental-health, nutrition, wellness 4 CommentsAdapted from: Peper, E. & Harvey, R. Adjunctive techniques to reduce interpersonal stress at home. Biofeedback. 53(3), 54-57. https://rdcu.be/eMJqt

Stress often triggers defensive reactions—manifesting as anger, frustration, or anxiety that may mirror fight-or-flight responses. These reactions can reduce rational thinking, increase long-term health risks, and contribute to psychological and physiological disorders. and complicate the management of specific symptoms. Outlined are some pragmatic techniques that can be implemented during the day to interrupt and reduce stress.
After we had been living in our house for a few years, a new neighbor moved in next door. Within months, she accused us of moving things in her yard, blamed us when there was a leak in her house, claimed we were blowing leaves from her property onto other neighbors’ properties, and even screamed at her tenants to the extent that the police were called numerous times. Just looking at her house through the window was enough to make my shoulders tighten and leave me feeling upset.
When I drove home and saw her standing in front of her house, I would drive around the block one more time to avoid her while . . . feeling my body contract. Often, when I woke up in the morning, I would already anticipate conflict with my neighbor. I would share stories of my disturbing neighbor and her antics with my friends. They were very supportive and agreed with me that she was crazy. However, the acknowledgment and validation from my friends did not resolve my anger or indignation or the anxiety that was triggered whenever I saw my neighbor or thought of her. I spent far too much time anticipating and thinking about her, which resulted in tension in my own body—my heart rate would increase, and my neck and shoulders would tighten.
I decided to change. I knew I could not change her; however, I could change my reactivity and perspective. Thus, I practiced a “pause and recenter” technique. At the first moment of awareness that I was thinking about her or her actions, I would change my posture by sitting up straight, begin looking upward, breathe lower and slower, and then, in my mind’s eye, send a thought of goodwill streaming to her like an ocean wave flowing through and around her in the distance. I chose to do this series of steps because I believe that within every person, no matter how crazy or cruel, there is a part that is good, and it is that part I want to support.
I repeated this pause and recenter technique many times, especially whenever I looked in the direction of her house or saw her in her yard. I also reframed and reappraised her aggressive, negative behavior as her way of coping with her own demons. Three months later, I no longer reacted defensively. When I see her, I can say hello and discuss the weather without triggering my defensive reaction. I feel so much more at peace living where I am.
When stressed, angry, rejected, frustrated, or hurt, we so often blame the other person (Leary, 2015). The moment we think about that person or event, our anger, indignation, resentment, and frustration are triggered. We keep rehashing what happened. As we relive the experiences in our mind, we are unaware that we are also reliving bodily reactions to past events.
We are often unaware of the harm we are doing to ourselves until we experience physical symptoms such as high blood pressure, gastrointestinal distress, and muscle tightness along with behavioral and psychological symptoms such as insomnia, anxiety, or depression (Carney et al., 2006; Gerin et al., 2012). As we think of past events or interact again with a person involved in those past events, our body automatically responds with a defense reaction as if we were being threatened again in the present moment.
This defense reaction to memory of past threats from a “crazy” neighbor activates our fight-or-flight responses and increases sympathetic activation so that we can run faster and fight more ferociously to survive; however, this reaction also reduces blood flow through the frontal cortex—a process that reduces our ability to think rationally (van Dinther et al., 2024; Willeumier, et al., 2011). When we become so upset and stressed that our mind is captured by the other person, this reaction contributes to symptoms of chronic stress such as an increase in hypertension, myofascial pain, depression, insomnia, cardiovascular disease, and other chronic disorders (Duan et al., 2022; Russell et al., 2015; Suls, 2013).
Sharing our frustrations with friends and others is normal. It feels good to blame people for their personal limitations or mental illness; however, over time, blaming others avoids building adaptive capacity in strengthening skills that reduce chronic stress reactions (Fast & Tiedens, 2010; Lou et al., 2023). The time spent rehashing and justifying our feelings diminishes the time we spend in the present moment and our focus on upcoming opportunities.
In the moment of an encounter with a difficult neighbor, we may not realize that we have a choice. Some people keep living and reacting to past hurts or losses perpetually. Some people can learn to let go and/or forgive and make space in favor of considering new opportunities for learning and growth. Although the choice is ours, it is often very challenging to implement—even with the best intentions—because we react automatically when reminded of past hurts (seeing that person, anticipating meeting or actually meeting that person who caused the hurt, or being triggered by other events that evoke memories of the pain).
What Can You Do
Choose to change your response. Choose to reduce reactivity. Choosing adaptive reactions does not mean you condone what happened or agree that the other person was right. You are just choosing to live your life and not continue to be captured by nor react to the previous triggers. Many people report that after implementing some of the practices described below along with many other stress management techniques, their automatic reactivity was noticeably decreased. They report that their chronic stress symptoms were reduced and they have the freedom to live in present instead of being captured by the painful past.
Pause and Recenter by Sending Goodwill
Our automatic reaction to the trigger elicits a defense reaction that reduces our ability to think rationally. Therefore, the moment you anticipate or begin to react, take three very slow diaphragmatic breaths, inhaling for approximately 4–5 seconds and exhaling for about 5–6 seconds, where one in-and-out breath takes about 10 seconds to complete. As you inhale, allow your abdomen to expand; then as you exhale, slowly make yourself tall and look up. Looking up allows easier access to empowering and positive memories (Peper et al., 2017).
Continue looking up, inhaling slowly to allow the abdomen to expand. Repeat this slow breath again. On the third long, slow breath, while looking up, evoke a memory of someone in whose presence you felt at peace and who loves you, such as your grandmother, aunt, uncle, or even a pet. Reawaken positive feelings associated with memories of being loved. Allow a smile inwardly or outwardly and soften your eyes as you experience the loving memory.
Next, put your hands on your chest, take another long slow breath as your abdomen expands, and as you exhale bring your hands away from your chest and stretch them out in front of you. At the same time in your mind’s eye, imagine sending goodwill to that person involved in the interpersonal conflict that previously evoked your stress response. As if you are sending an ocean wave that is streaming outward to the person.
As you do the pause and recenter technique, remember you are not condoning what happened; instead, you are sending goodwill to that person’s positive aspect. From this perspective, everyone has an intrinsic component—however small—that some label as the individual’s human potential, Christ nature or Buddha nature.

Why would this be effective? This practice short-circuits the automatic stress response and provides time to recenter, interrupting ongoing rumination by shifting the mind away from thoughts about the person or event that induced stress toward a positive memory. By evoking a loving memory from the past, we facilitate a reduction in arousal, evoke a positive mood, and decrease sympathetic nervous system activation (Speer & Delgado, 2017). Slower diaphragmatic breathing also reduces sympathetic activation (Birdee et al., 2023; Siedlecki et al., 2022). By combining body-centered and mind-centered techniques, we can pause and create the opportunity to respond positively rather than reacting with anger and hurt.
Practice Sending Goodwill the Moment You Wake Up
So often when we wake up, we anticipate the challenges, and even the prospect of interacting with a person or event heightens our defense reaction. Therefore, as soon as you wake up, sit at the edge of the bed, repeat the previous practice, pause, and center. Then, as you sit at the edge of the bed, slightly smile with soft eyes, look up, and inhale as your abdomen expands. Then, stamp a foot into the floor while saying, “Today is a new day.” Next, inhale, allowing your abdomen to expand; as you look up, stamp the opposite foot on the floor while saying, “Today is a new day.” Finally, send goodwill to the person who previously triggered your defensive reaction.
Why would this be effective? Looking up makes it easier to access positive memories and thoughts. Stamping your foot on the ground is a nonverbal expression of determination and anchors the thought of a new day, thereby focusing on new opportunities (Feldman, 2022).
Interrupt the Stress Response with the ABCs
The moment you notice discomfort, pain, stress, or negative thoughts, interrupt the cycle with a simple ABC strategy (Peper, 2025):
- Adjust posture and look up
- Breathe by allowing your abdomen to relax and expand while inhaling
- Change your internal dialogue, smile and focus on what you want to do
Why would this be effective? By shifting your posture and gently looking upward, you make it easier to access positive and empowering memories and thoughts (Peper et al., 2019). This simple change in body position can interrupt habitual stress responses and open the doorway to more constructive states.
Slow, diaphragmatic breathing further supports this process by reducing sympathetic arousal and restoring a sense of calm. As your breathing deepens, clarity of mind increases, allowing you to respond rather than react (Peper et al, 2024b; Matto et al, 2025).
Equally important is transforming critical, judgmental, or negative self-talk into affirmative, supportive statements. Describe what you want to do—rather than what you want to avoid. This reframing creates a clear internal guide and significantly increases the likelihood that you will achieve your desired goals.
Complete the Alarm Reaction a Burst of Physical Activity
When you feel overwhelmed and fully captured by a stress reaction, one of the most effective strategies is to complete the fight-flight response with a brief burst of intense physical activity. This momentary action such as running in place, vigorously shaking your arms, or doing a few rapid push-offs from a wall (Peper et al., 2024a). After completing the physical activity implement your stress management strategies such as breathing, cognitive reframing, meditation, etc.
Why would this be effective? The intense physical activity discharges the excessive physiological arousal and interrupts the cycle of rumination. For practical examples and step-by-step guidance, see the article Quick Rescue Techniques When Stressed (Peper et al., 2024a) or the accompanying blog post: https://peperperspective.com/2024/02/04/quick-rescue-techniques-when-stressed/
Discuss Your Issue from the Third-Person Perspective
When thinking, ruminating, talking, texting, or writing about the event, discuss it from the third-person perspective. Replace the first-person pronoun “I” with “she” or “he.” For example, instead of saying “I was really pissed off when my boss criticized my work without giving any positive suggestions for improvement,” say “He was really pissed off when his boss criticized his work without offering any positive suggestions for improvement.”
Why would this be effective? The act of substituting the third-person pronoun for the first-person pronoun interrupts our automatic reactivity because it requires us to observe and change our language, which activates parts of the frontal cortex. This third-person/first-person process creates a psychological distance from our feelings, allowing for a more objective and calmer perspective on the situation, effectively reducing stress by stepping back from the immediate emotional response (Moser et al., 2017). This process can be interpreted as meaning that you are no longer fully captured by the emotions, as you are simultaneously the observer of your own inner language and speech.
Compare Yourself with Others Who are less Fortunate
When you feel sorry for yourself or hurt, take a breath, look upward, and compare yourself with others who are suffering much more. In that moment, consider yourself incredibly lucky compared with people enduring extreme poverty, bombings, or severe disfigurement. Be grateful for what you have.
Why would this be effective? Research shows that when we compare ourselves with people who are more successful, we tend to feel worse—especially when we have low self-esteem. However, when we compare ourselves with others who are suffering more, we tend to feel better (Aspinwall, & Taylor, 1993). This comparison relativizes our perspective on suffering, making our own hardships and suffering seem less significant compared with the severe suffering of others.
Conclusion
It is much easier to write and talk about these practices than to implement them. Reminding yourself to implement them can be very challenging. It requires significant effort and commitment. In some cases, the benefits are not experienced immediately; however, when practiced many times during the day for six to eight weeks, many people report feeling less resentment and experience a reduction in symptoms and improvements in health and relationships.
*This blog was inspired by the podcast “No Hard Feelings,” an episode on Hidden Brain produced by Shankar Vedantam (2025) that featured psychologist Fred Luskin, and the wisdom taught by Dora Kunz (Kunz & Peper, 1983, 1984a, 1984b, 1987).
See the following posts for more relevant information
References
Aspinwall, L. G., & Taylor, S. E. (1993). Effects of social comparison direction, threat, and self-esteem on affect, self-evaluation, and expected success. Journal of Personality and Social Psychology, 64(5), 708–722. https://doi.org/10.1037/0022-3514.64.5.708
Birdee, G., Nelson, K.,Wallston, K., Nian, H., Diedrich, A., Paranjape, S., Abraham, R., & Gamboa, A. (2023). Slow breathing for reducing stress: The effect of extending exhale. Complementary Therapies in Medicine, 73. https://doi.org/10.1016/j.ctim.2023.102937
Carney, C. E., Edinger, J. D., Meyer, B., Lindman, L., & Istre, T. (2006). Symptom-focused rumination and sleep disturbance. Behavioral Sleep Medicine, 4(4), 228–241. https://doi.org/10.1207/s15402010bsm0404_3
Defayette, A. B., Esposito-Smythers, C., Cero, I., Harris, K. M.,Whitmyre, E. D., & López, R. (2023). Interpersonal stress and proinflammatory activity in emerging adults with a history of suicide risk: A pilot study. Journal of Mood and Anxiety Disorders, 2. https://doi.org/10.1016/j.xjmad.2023.100016
Dienstbier, R. A. (1989). Arousal and physiological toughness: Implications for mental and physical health. Psychological Review, 96(1), 84. https://doi.org/10.1037/0033-95x.96.1.84
Duan, S., Lawrence, A., Valmaggia, L., Moll, J., & Zahn, R. (2022). Maladaptive blame-related action tendencies are associated with vulnerability to major depressive disorder. Journal of Psychiatric Research, 145, 70–76. https://doi.org/10.1016/j.jpsychires.2021.11.043
Fast, N. J., & Tiedens, L. Z. (2010). Blame contagion: The automatic transmission of self-serving attributions. Journal of Experimental Social Psychology, 46(1), 97–106. https://doi.org/10.1016/j.jesp.2009.10.007
Feldman, Y. (2022). The dialogical dance–A relational embodied approach to supervision. In C. Butte & T. Colbert (Eds.), Embodied approaches to supervision: The listening body (chap. 2). Routledge. https://www.amazon.com/Embodied-Approaches-Supervision-C%C3%A9line-Butt%C3%A9/dp/0367473348
Gerin,W., Zawadzki,M. J., Brosschot, J. F., Thayer, J. F., Christenfeld, N. J., Campbell, T. S., & Smyth, J. M. (2012). Rumination as a mediator of chronic stress effects on hypertension: A causal model. International Journal of Hypertension, 2012, 453465. https://doi.org/10.1155/2012/453465
Hase, A., O’Brien, J., Moore, L. J., & Freeman, P. (2019). The relationship between challenge and threat states and performance: A systematic review. Sport, Exercise, and Performance Psychology, 8(2), 123. https://doi.org/10.1037/spy0000132
Hassamal, S. (2023). Chronic stress, neuroinflammation, and depression: An overview of pathophysiological mechanisms and emerging anti-inflammatories. Frontiers in Psychiatry,
14, 1130989. https://doi.org/10.3389/fpsyt.2023.1130989
Kunz, D., & Peper, E. (1983). Fields and their clinical implications—Part III: Anger and how it affects human interactions. The American Theosophist, 71(6), 199–203. https://www.researchgate.net/publication/280777019_Fields_and_their_clinical_implications-Part_III_Anger_and_how_it_affects_human_interactions
Kunz, D., & Peper, E. (1984a). Fields and their clinical implications IV: Depression from the energetic perspective: Etiological underpinnings. The American Theosophist, 72(8), 268–275. https://www.researchgate.net/publication/280884054_Fields_and_their_clinical_implications_Part_IV_Depression_from_the_energetic_perspective-Etiological_underpinnings
Kunz, D., & Peper, E. (1984b). Fields and their clinical implications V: Depression from the energetic perspective: Treatment strategies. The American Theosophist, 72(9), 299–306. https://www.researchgate.net/publication/280884158_Fields_and_their_clinical_implications_Part_V_Depression_from_the_energetic_perspective-Treatment_strategies
Kunz, D., & Peper, E. (1987). Resentment: A poisonous undercurrent. The Theosophical Research Journal, IV(3), 54–59. Also in: Cooperative Connection, IX(1), 1–5. https://www.researchgate.net/publication/387030905_Resentment_Continued_from_page_4
Leary, M. R. (2015). Emotional responses to interpersonal rejection. Dialogues in Clinical Neuroscience, 17(4), 435–441. https://doi.org/10.31887/DCNS.2015.17.4/mleary
Lou, Y., Wang, T., Li, H., Hu, T. Y., & Xie, X. (2023). Blame others but hurt yourself: Blaming or sympathetic attitudes toward victims of COVID-19 and how it alters one’s health status. Psychology & Health, 39(13), 1877–1898. https://doi.org/10.1080/08870446.2023.2269400
Matto, D., Peper, E., & Harvey, R. (2025). Monitoring and coaching breathing patterns and rate. Townsend Letter-Innovative Health Perspectives. https://townsendletter.com/monitoring-and-coaching-breathing-patterns-and-rate/
Moser, J. S., Dougherty, A., Mattson, W. I., Katz, B., Moran, T. P.,Guevarra, D., Shablack, H.,Ayduk,O., Jonides, J., Berman, M. G., & Kross, E. (2017). Third-person self-talk facilitates emotion regulation without engaging cognitive control: Converging evidence from ERP and fMRI. Scientific Reports, 7(1), 4519. https://doi.org/10.1038/s41598-017-04047-3
Peper, E. (2025). Breathe Away Menstrual Pain- A Simple Practice That Brings Relief. the peper perspective-ideas on illness, health and well-being from Erik Peper. https://peperperspective.com/2025/11/22/6825/
Peper, E., Harvey, R., & Hamiel, D. (2019). Transforming thoughts with postural awareness to increase therapeutic and teaching efficacy. NeuroRegulation, 6(3), 153-169. https://doi.org/10.15540/nr.6.3.1533-1
Peper, E., Lin, I.-M., Harvey, R., & Perez, J. (2017). How posture affects memory recall and mood. Biofeedback, 45(2), 36–41. https://doi.org/10.5298/1081-5937-45.2.01
Peper, E., Oded, Y., & Harvey, R. (2024a). Quick somatic rescue techniques when stressed. Biofeedback, 52(1), 18–26. https://doi.org/10.5298/982312
Peper, E., Oded, Y., Harvey, R., Hughes, P., Ingram, H., & Martinez, E. (2024b). Breathing for health: Mastering and generalizing breathing skills. Townsend Letter-Innovative Health Perspectives. November 15, 2024. https://townsendletter.com/suggestions-for-mastering-and-generalizing-breathing-skills/
Russell, M. A., Smith, T. W., & Smyth, J. M. (2015). Anger expression, momentary anger, and symptom severity in patients with chronic disease. Annals of Behavioral Medicine, 50(2), 259–271. https://doi.org/10.1007/s12160-015-9747-7
Siedlecki, P., Ivanova, T. D., Shoemaker, J. K., & Garland, S. J. (2022). The effects of slow breathing on postural muscles during standing perturbations in young adults. Experimental Brain Research, 240, 2623–2631. https://doi.org/10.1007/s00221-022-06437-0
Speer, M. E., & Delgado, M. R. (2017). Reminiscing about positive memories buffers acute stress responses. Nature Human Behaviour, 1, 0093. https://doi.org/10.1038/s41562-017-0093
Suls, J. (2013). Anger and the heart: Perspectives on cardiac risk, mechanisms and interventions. Progress in Cardiovascular Diseases, 55(6), 538–547. https://doi.org/10.1016/j.pcad.2013.03.002
van Dinther, M., Hooghiemstra, A. M., Bron, E. E., Versteeg, A., et al. (2024). Lower cerebral blood flow predicts cognitive decline in patients with vascular cognitive impairment. Alzheimer’s & Dementia: The Journal of the Alzheimer’s Association, 20(1), 136–144. https://doi.org/10.1002/alz.13408
Vedantam, S. (2025). No hard feelings. Hidden brain. Accessed February 5, 2025. https://hiddenbrain.org/podcast/no-hard-feelings/
Willeumier, K., Taylor, D. V., & Amen, D. G. (2011). Decreased cerebral blood flow in the limbic and prefrontal cortex using SPECT imaging in a cohort of completed suicides. Translational Psychiatry, 1(8), e28. https://doi.org/10.1038/tp.2011.28
Zannas, A. S., & West, A. E. (2014). Epigenetics and the regulation of stress vulnerability and resilience. Neuroscience, 264, 157–170. https://doi.org/10.1016/j.neuroscience.2013.12.003
Breathe Away Menstrual Pain- A Simple Practice That Brings Relief *
Posted: November 22, 2025 Filed under: attention, behavior, biofeedback, Breathing/respiration, cognitive behavior therapy, education, emotions, Neck and shoulder discomfort, Pain/discomfort, posture, relaxation, self-healing, stress management, Uncategorized | Tags: dysmenorrhea, health, meditation, menstrual cramps, mental-health, mindfulness, wellness 3 CommentsAdapted from: Peper, E. Harvey, R., Chen, & Heinz, N. (2025). Practicing diaphragmatic breathing reduces menstrual symptoms both during in-person and synchronous online teaching. Applied Psychophysiology and Biofeedback, Published online: 25 October 2025. https://rdcu.be/eMJqt https://doi.org/10.1007/s10484-025-09745-7
“Once again, the pain starts—sharp, deep, and overwhelming—until all I can do is curl up and wait for it to pass. There’s no way I can function like this, so I call in sick. The meds take the edge off, but they don’t really fix anything—they just mask it for a little while. I usually don’t tell anyone it’s menstrual pain; I just say I’m not feeling well. For the next couple of days, I’m completely drained, struggling just to make it through.
Many women experience discomfort during menstruation, from mild cramps to intense, even disabling pain. When the pain becomes severe, the body instinctively responds by slowing down—encouraging rest, curling up to protect the abdomen, and often reaching for medication in hopes of relief. For most, the symptoms ease within a day or two, occasionally stretching into three, before the body gradually returns to balance.
Another helpful approach is to practice slow abdominal breathing, guided by a breathing app FlowMD. In our study led by Mattia Nesse, PhD, in Italy, the response of one 22-year-old woman illustrated the power of this simple practice.
“Last night my period started, so I was a bit discouraged because I knew I’d get stomach pain, etc. On the other hand, I said, “Okay, let’s see if the breathing works,” and it was like magic — incredible. I’ll need to try it more times to understand whether it consistently has the same effect, but right now it truly felt magical. Just 3 minutes of deep breathing with the app were enough, and I’m not saying I don’t feel any pain anymore, but it has decreased a lot, so thank you! Thank you again for this tool… I’m really happy!”
The Silent Burden of Menstrual Pain
Menstrual pain, or dysmenorrhea, affects most women at some point in their lives — often silently. For many, the monthly cycle brings not only physical discomfort but also shame, fatigue, and interruptions to work or school. It is one of the leading causes of absenteeism and reduced productivity worldwide (Itani et al., 2022; Thakur & Pathania, 2022). In addition, the estimated health cost ranged from US $1367 to US$ 7043 per year (Huang et al., 2021). Yet, despite its prevalence, most women are never taught how to use their own physiology to ease these symptoms.
The Study (Peper et al, 2025)
Seventy-five university women participated across two upper-division Holistic Health courses. Forty-nine practiced 30 minutes per day of breathing and relaxation over five weeks as well as practicing the moment they anticipated or felt discomfort; twenty-six served as a comparison group without a specific daily self-care routine. Students rated change in menstrual symptoms on a scale from –5 (“much worse”) to +5 (“much better”). For the detailed steps in training, see the blog: https://peperperspective.com/2023/04/22/hope-for-menstrual-cramps-dysmenorrhea-with-breathing/ (Peper et al., 2023).
What changed
The results were striking. Women who practiced breathing and relaxation showed significant decrease in menstrual symptoms compared to the non-intervention group (p = 0.0008) as shown in Figure 1.
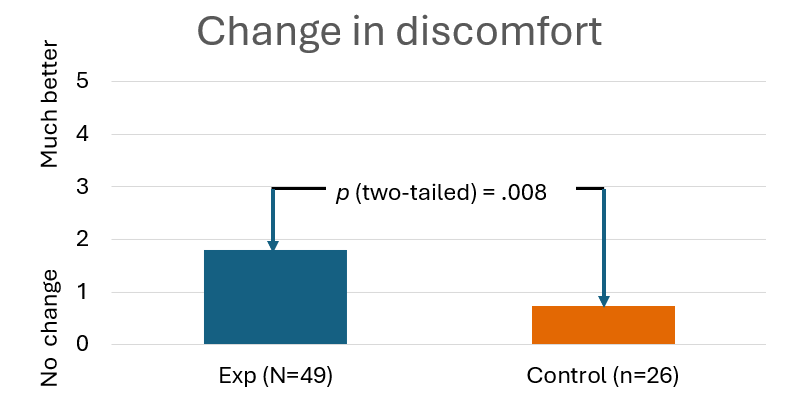
Figure 1. Decrease in menstrual symptoms as compared to the control group after implementing slow diaphragmatic breathing.
Why does breathing and posture change have a beneficial effect?
When you stay curled up, your abdomen becomes compressed, leaving little room for the lower belly to relax or for the diaphragm to move freely. The result? Tension builds, and pain often increases.
To reverse this, create space for relaxation. Gently loosen your waist and let your abdomen expand as you inhale. Uncurl your body—lengthen your spine and open your chest, as shown in Figure 2. With each easy breath, you invite calm and allow your body to shift from tension to ease.
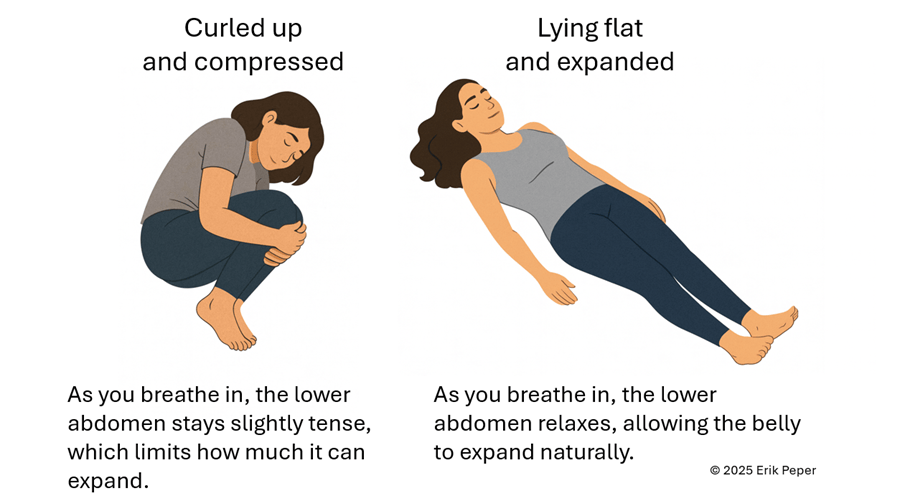
Figure 2. Curling up compresses the abdomen and prevents relaxation of the lower belly. In contrast, lying flat with the body gently expanded allows the abdomen to move freely with each breath, which can help reduce menstrual discomfort.
In contrast, slow abdominal or diaphragmatic breathing activates the body’s natural relaxation response. It quiets the stress-driven sympathetic nervous system, calms the mind, and improves circulation in the abdominal area. With each slow breath in, the abdomen gently expands while the pelvic floor and abdominal muscles relax. As you exhale, these muscles naturally tighten slightly, helping to massage and move blood and lymph through the abdominal region. This rhythmic movement supports healing and ease, as illustrated in Figure 3.
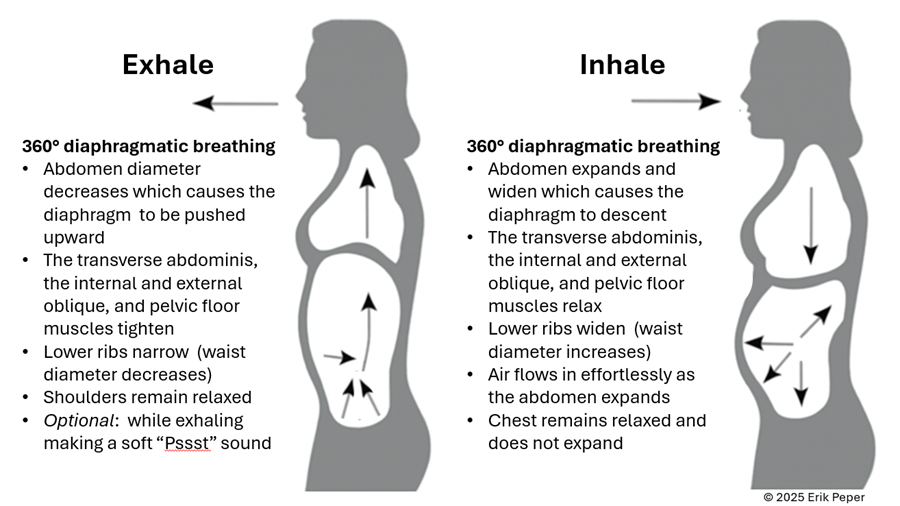
Figure 3. The dynamic process of diaphragmatic breathing.
The process of slower, lower diaphragmatic breathing
When lying down, rest comfortably on your back with your legs slightly apart. Allow your abdomen to rise naturally as you inhale and fall as you exhale. As you breathe out, imagine the air flowing through your abdomen, down your legs, and out through your feet. To deepen this sensation, you can ask a partner to gently stroke from your abdomen down your legs as you exhale—helping you sense the flow of release through your body.
Gently focus on slow, effortless diaphragmatic breathing. With each inhalation, your abdomen expands, and the lower belly softens. As you exhale, the abdomen gently goes down pushing the diaphragm upward and allowing the air to leave easily. Breathing slowly—about six breaths per minute—helps engage the body’s natural relaxation response.
If you notice that your breath is staying high in your chest instead of expanding through the abdomen, your symptoms may not improve and can even increase. One participant experienced this at first. After learning to let her abdomen expand with each inhalation while keeping her shoulders and chest relaxed, her next menstrual cycle was markedly easier and far less uncomfortable. The lesson is clear: technique matters.
“During times of pain, I practiced lying down and breathing through my stomach… and my cramps went away within ten minutes. It was awesome.” — 22-year-old college student
“Whenever I felt my cramps worsening, I practiced slow deep breathing for five to ten minutes. The pain became less debilitating, and I didn’t need as many painkillers.” — 18-year-old college student
These successes point out that it’s not just breathing — it’s how you breathe by providing space for the abdomen to expand during inhalation.
Practice: How to Do Diaphragmatic Breathing
- Find a quiet space. Lie on your back or sit comfortably erect with your shoulders relaxed.
- Place one hand on your chest and one on your abdomen.
- Inhale slowly through your nose for about 3–4 seconds. Let your abdomen expand as you breathe in — your chest should remain relaxed.
- Exhale gently through your mouth for 4—6 seconds, allowing the abdomen to fall or constrict naturally.
- As you exhale imagine the air moving down your arms, through your abdomen, down your legs, and out your feet
- Practice daily for 20 minutes and also for 5–10 minutes during the day when menstrual discomfort begins.
- Add warmth. Placing a warm towel or heating pad over your abdomen can enhance relaxation while lying on your back and breathing slowly.
With regular practice and implementing it during the day when stressed, this simple method can reduce cramps, promote calm, and reconnect you with your body’s natural rhythm.
Implement the ABCs during the day
The ABC sequence—adapted from the work of Dr. Charles Stroebel, who developed The Quieting Reflex (Stroebel, 1982)—teaches a simple way to interrupt stress reactions in real time. The moment you notice discomfort, pain, stress, or negative thoughts, interrupt the cycle with a simple ABC strategy:
A — Adjust your posture
Sit or stand tall, slightly arch your lower back and allowing the abdomen to expand while you inhale and look up. This immediately shifts your body out of the collapsed “defense posture’ and increases access to positive thoughts (Tsai et all, 2016; Peper et al., 2019)
B — Breathe
Allow your abdomen to expand as you inhale slowly and deeply. Let it get smaller as you exhale. Gently make a soft hissing sound as you exhale while helps the abdomen and pelvic floor to tighten. Then allow the abdomen to relax and widen which without effort draws the air in during inhalation. As you exhale, stay tall and imagine the air flowing through you and down your legs and out your feet.
C — Concentrate
Refocus your attention on what you want to do and add a gentle smile. This engages positive emotions, the smile helps downshift tension.
The video clip guides you through the ABCs process.
Integrate the breathing during the day by implementing your ABCs
When students practice relaxation technique and this method, they reported greater reductions in symptoms compared with a control group. By learning to notice tension and apply the ABC steps as soon as stress arises, they could shift their bodies and minds toward calm more quickly, as shown in Figure 4.
Figure 4. Change in symptoms after practicing a sequential relaxation and breathing techniques for four weeks.
Takeaway
Menstrual pain doesn’t have to be endured in silence or masked by medication alone. By practicing 30 minutes of slow diaphragmatic breathing daily and many times during the day, women may be able to reduce pain, stress, and discomfort — while building self-awareness and confidence in their body’s natural rhythms thereby having the opportunity to be more productive.
We recommend that schools and universities include self-care education—especially breathing and relaxation practices—as part of basic health curricula as this approach is scalable. Teaching young women to understand their bodies, manage stress, and talk openly about menstruation can profoundly improve well-being. It not only reduces physical discomfort but also helps dissolve the stigma that still surrounds this natural process,
Remember: Breathing is free—available anytime, anywhere and is helpful in reducing pain and discomfort. (Peper et al., 2025; Joseph et al., 2022)
See the following blogs for more in-depth information and practical tips on how to learn and apply diaphragmatic breathing:
REFERENCES
Itani, R., Soubra, L., Karout, S., Rahme, D., Karout, L., & Khojah, H.M.J. (2022). Primary Dysmenorrhea: Pathophysiology, Diagnosis, and Treatment Updates. Korean J Fam Med, 43(2), 101-108. https://doi.org/10.4082/kjfm.21.0103
Huang, G., Le, A. L., Goddard, Y., James, D., Thavorn, K., Payne, M., & Chen, I. (2022). A systematic review of the cost of chronic pelvic pain in women. Journal of Obstetrics and Gynaecology Canada, 44(3), 286–293.e3. https://doi.org/10.1016/j.jogc.2021.08.011
Joseph, A. E., Moman, R. N., Barman, R. A., Kleppel, D. J., Eberhart, N. D., Gerberi, D. J., Murad, M. H., & Hooten, W. M. (2022). Effects of slow deep breathing on acute clinical pain in adults: A systematic review and meta-analysis of randomized controlled trials. Journal of Evidence-Based Integrative Medicine, 27, 2515690X221078006. https://doi.org/10.1177/2515690X221078006
Peper, E., Booiman, A. & Harvey, R. (2025). Pain-There is Hope. Biofeedback, 53(1), 1-9. http://doi.org/10.5298/1081-5937-53.01.16
Peper, E., Chen, S., Heinz, N., & Harvey, R. (2023). Hope for menstrual cramps (dysmenorrhea) with breathing. Biofeedback, 51(2), 44–51. https://doi.org/10.5298/1081-5937-51.2.04
Peper, E., Harvey, R., Chen, S., & Heinz, N. (2025). Practicing diaphragmatic breathing reduces menstrual symptoms both during in-person and synchronous online teaching. Applied Psychophysiology and Biofeedback. Published online: 25 October 2025. https://rdcu.be/eMJqt https://doi.org/10.1007/s10484-025-09745-7
Peper, E., Harvey, R., & Hamiel, D. (2019). Transforming thoughts with postural awareness to increase therapeutic and teaching efficacy. NeuroRegulation, 6(3),153-169. https://doi.org/10.15540/nr.6.3.1533-1
Stroebel, C. (1982). The Quieting Reflex. New York: Putnam Pub Group. https://www.amazon.com/Qr-Quieting-Charles-M-D-Stroebel/dp/0399126570/
Thakur, P. & Pathania, A.R. (2022). Relief of dysmenorrhea – A review of different types of pharmacological and non-pharmacological treatments. MaterialsToday: Proceedings.18, Part 5, 1157-1162. https://doi.org/10.1016/j.matpr.2021.08.207
Tsai, H. Y., Peper, E., & Lin, I. M. (2016). EEG patterns under positive/negative body postures and emotion recall tasks. NeuroRegulation, 3(1), 23-27. https://doi.org/10.15540/nr.3.1.23
*Edited with the help of ChatGPT 5
Ensorcelled: Breaking the Digital Enchantment
Posted: October 7, 2025 Filed under: ADHD, attention, behavior, cellphone, computer, digital devices, education, emotions, healing, health, laptops, techstress, Uncategorized | Tags: anxiety, depression, health, human connection, life, loneliness, media addictdion, mental-health, storytelling 2 Comments
My mom called, “Stop playing on your computer and come for dinner!” I heard her, but I was way too into my game. It felt like I was actually inside it. I think I yelled “Yeah!” back, but I didn’t move.
A few seconds later, I was totally sucked into this awesome world where I was conquering other galaxies. My avatar was super powerful, and I was winning this crazy battle.
Then, all of a sudden, my mom came into my room and just turned off the computer. I was so mad. I was about to win! The real world around me felt boring and empty. I didn’t even feel hungry anymore. I didn’t say anything, I just wanted to go back to my game.
For some, the virtual world feels more real and exciting than the actual one. It can seem more vivid precisely because they have not yet tasted the full, multi-dimensional richness of real human connection, those moments when you feel seen, touched, and understood.
This theme comes vividly alive in my son Eliot Peper’s new novella, Ensorcelled. I am so proud of him. He has crafted a story in which a young boy, captured by the spell of the immersive digital world, discovers that real-life experiences carry far deeper meaning. I won’t give away the plot, but the story creates the experience, it doesn’t just tell it. It reminds us that meaning and belonging arise through genuine connection, not through screens. As Eliot writes, “Sometimes a story is the only thing that can save your life.” It’s a story everyone should read.
The effects of our immersive digital world
Our new world of digital media can take over the reality of actual experiences. It is no wonder that more young people feel stressed and have social anxiety when they have to make an actual telephone call instead of texting (Jin, 2025). They also experience a significant increase in anxiety and depression and feel more awkward initiating in-person social communication with others. The increase in mental health problems and social isolation affects predominantly those who are cellphone and social media natives; namely, those who started to use social media after Facebook was released in 2004 and the iPhone in 2007 (Braghieri et al., 2022).
Students who are most often on their phone whether streaming videos, scrolling, texting, watching YouTube, Instagram or TikTok, and more importantly responding to notifications from phones when they are socializing, report higher levels of loneliness, depression and anxiety as shown inf Figure 1 (Peper & Harvey 2018). They also report less positive feelings and energy when they communicate with each other online as compared to in person (Peper & Harvey, 2024).
Figure 1. The those with the highest phone use were the most lonely, depressed and anxious (Peper and Harvey, 2018).
Even students’ sexual activity has decreased in U.S. high-school from 2013 to 2023 and young adults (ages 18-44) from 2000-2018 (CDC, 2023; Ueda et al., 2020). Much of this may be due to the reality that adolescents have reduced face-to-face socializing (dating, parties, going out) while increasing their time on digital media (Twenge et al., 2019).
What to do
As a parent it often feels like a losing battle to pull your child, or even yourself, away from the intoxicating digital media, since the digital world is supercharged with AI-generated media. It is all aimed at capturing eyeballs (your attention and time), resulting reducing genuine human social connection. (Peper at al., 2020; Haidt, 2024). To change behavior is challenging and yet rewarding. If possible, implement the following (Peper at al., 2020; Twenge, 2025; Haidt, 2024):
- Create tech-free zones. Keep phones and devices out of bedrooms, the dinner table, and family gatherings. Make these spaces sacred for real connection.
- Avoid screens before bedtime. Turn off screens at least an hour before bed. Replace scrolling with quiet reflection, reading, or gentle stretching. Read or tell actual stories before bedtime.
- Explore why we turn to digital media. Before you open an app, ask: Why am I doing this? Am I bored, anxious, or avoiding something? Awareness shifts behavior.
- Provide unstructured time. Let yourself and your children be bored sometimes. Boredom sparks creativity, imagination, and self-discovery.
- Create shared experiences. Plan family activities that don’t involve screens—cooking, hiking, playing music, or simply talking. Real connection satisfies what digital media only mimics.
- Implement social support. Coordinate with other parents, friends, or colleagues to agree on digital limits. Shared norms make it easier to follow through.
- Model what you want your children to do. Children imitate what they see. When adults practice digital restraint, kids learn that real life matters more than screen life.
We have a choice.
We can set limits now and experience real emotional connection and growth or become captured, enslaved, and manipulated by the corporate creators, producers and sellers of media.
Read Ensorcelled. which uses storytelling, the traditional way to communicate concepts and knowledge. Read it, share it. It may change your child’s life and your own.

Available from
Signed copy by author: https://store.eliotpeper.com/products/ensorcelled
Paperback: https://www.amazon.com/Ensorcelled-Eliot-Peper/dp/1735016535/
Kindle: https://www.amazon.com/Ensorcelled-Eliot-Peper-ebook/dp/B0FLGQC3BS/
References
Braghieri, L., Levy, R., & Makarin, A. (2022). Social Media and Mental Health (July 28, 2022) http://dx.doi.org/10.2139/ssrn.3919760
CDC. (2023). Centers for Disease Control and Prevention. (2023). Youth Risk Behavior Survey: Data summary & trends report 2011–2021. U.S. Department of Health and Human Services. https://www.cdc.gov/healthyyouth/data/yrbs/index.htm
Haidt, J. (2024). The Anxious Generation: How the Great Rewiring of Childhood Is Causing an Epidemic of Mental Illness. New York: Penguin Press. https://www.amazon.com/Anxious-Generation-Rewiring-Childhood-Epidemic/dp/0593655036
Jin, B. (2025). Avoidance and Anxiety About Phone Calls in Young Adults: The Role of Social Anxiety and Texting Controllability. Communication Reports, 1–14. https://doi.org/10.1080/08934215.2025.2542562
Peper, E. & Harvey, R. (2018). Digital addiction: increased loneliness, depression, and anxiety. NeuroRegulation. 5(1),3–8. doi:10.15540/nr.5.1.3 5(1),3–8. http://www.neuroregulation.org/article/view/18189/11842
Peper, E. & Harvey, R. (2024). Smart phones affects social communication, vision, breathing, and mental and physical health: What to do! Townsend Letter-Innovative Health Perspectives, September 15, 2024. https://townsendletter.com/smartphone-affects-social-communication-vision-breathing-and-mental-and-physical-health-what-to-do/
Peper, E., Harvey, R. & Faass, N. (2020). TechStress: How Technology is Hijacking Our Lives, Strategies for Coping, and Pragmatic Ergonomics. Berkeley: North Atlantic Books.
Ueda, P., Mercer, C. H., Ghaznavi, C., & Herbenick, D. (2020). Trends in frequency of sexual activity and number of sexual partners among adults aged 18 to 44 years in the US, 2000–2018. JAMA Network Open, 3(6), e203833. https://doi.org/10.1001/jamanetworkopen.2020.3833
Twenge, J.M. (2025). 10 Rules for Raising Kids in a High-Tech World: How Parents Can Stop Smartphones, Social Media, and Gaming from Taking Over Their Children’s Lives. New York: Atria Books. https://www.amazon.com/Rules-Raising-Kids-High-Tech-World/dp/1668099993
Twenge, J. M., Spitzberg, B. H., & Campbell, W. K. (2019). Less in-person social interaction with peers among U.S. adolescents in the 21st century and links to loneliness. Journal of Social and Personal Relationships, 36(6), 1892-1913. https://doi.org/10.1177/0265407519836170
This May Save Your Life! Bacteriophage Treatment for Bacterial Diseases*
Posted: September 11, 2025 Filed under: Evolutionary perspective, healing, health, Pain/discomfort, self-healing | Tags: antibiotic resistance, antibiotics, bacteria, bacteriohage, health, Medicine Leave a commentRecently, I listened to a special episode featuring Lina Zeldovich on her book The Living Medicine, from This Podcast Will Kill You. I was totally inspired because it discussesd the healing power of bacteriophages, which apparently treat antibiotic-resistant bacterial infections successfully, reportedly without side effects. (Bacterial phages are viruses that selectively kill specific bacteria and have been used to treat multi-antibiotic-resistant conditions).
This emerging therapy is an aspect of individualized treatment. Zeldovich reports that it can not only be used to treat, but also to prevent the occurrence of bacterial illnesses. I rushed out to buy the book, The Living Medicine: How a lifesaving cure was nearly lost and why it will rescue us when antibiotics fail. Zeldovich is a great science storyteller and the book really captured me. I read it in two evenings and wanted to share this information, since a day may come when it could save your life.
This is a must-read for all of us, particularly for health professionals. It offers hope through a non-toxic strategy in the fight against antibiotic-resistant disease. The book provides a perspective on the challenges of bringing this effective healing strategy to acceptance and implementation when cultural biases and financial disincentives have stood in the way.;

Zeldovich, describes the development and history of bacterial phage medicine and why it has taken so many years to become accepted in the West. Only after several high-profile cases has this approach become of interest. A prime example is the 2016 treatment of Dr. Tom Patterson, a professor at UC San Diego, who contracted a life-threatening Acinetobacter baumannii infection while traveling (Garnett, 2019). The bacteria that caused his infection was resistant to every available antibiotic. After he slipped into a coma, his doctors feared the worst. As a last resort, his wife, Dr. Steffanie Strathdee, worked with scientists to identify phages that could target the infection. Within 48 hours of receiving intravenous phage therapy, Patterson woke up. He went on to make a full recovery, one of the first documented cases in the U.S. in which phages saved a patient’s life.
Pros and cons of antibiotics
Until antibiotics were discovered, bacterial infections were often fatal. This changed with the discovery of penicillin by Alexander Fleming in 1928. During World War II, antibiotics saved countless solders’ lives in the treatment of infected wounds, pneumonia, and blood poisoning. The antibiotic approach was quickly adopted in the United States, beginning in the early 1940’s, since penicillin could be mass-produced and thus was highly profitable for the pharmaceutical companies. Despite the initial success of the drug, bacteria quickly developed antibiotic resistance to penicillin due to the ability of bacteria to produce β-lactamase, an enzyme capable of breaking down the drug.
Antibiotics were and are extraordinary drugs. When a patient is becoming sicker and sicker as a bacterial infection spreads, the infection can be stopped in its tracks with an effective antibiotic. Before the era of antibiotic resistance, patients recovered as if by magic, simple by giving an antibiotic orally or intravenously,
I still remember when our son developed pneumonia at the age of 12, initially with coughing, a high fever, chest pain, and a great deal of congestion. But as the infection progressed, he began to have difficulty breathing and his energy was fading. We were initially hesitant to give the prescribed antibiotic because we hoped his immune system would be able to fight the infection. My hesitancy was based upon the fact that antibiotics do not selectively kill the bacteria causing the illness, but also destroy beneficial bacteria that are part of the human biome.
Millions of women who have taken an antibiotic for an infection subsequently experience chronic vaginal yeast infections. This occurs because antibiotics such as tetracyclines, which are used to treat UTIs, intestinal tract infections, eye infections, sexually transmitted infections, acne, and gum disease, also kill the healthy bacteria of the human biome in the vagina. Since nature abhors a vacuum, yeast then overgrow where healthy bacteria used to predominate, thus allowing a vaginal infection (candidiasis) to occur (Spinillo et al., 1999)
In the case of my son, as it became clear that he was getting weaker and his immune system was not successfully clearing the infection, we followed his doctor’s advice and gave him the antibiotic. Magically, within two days he was better, and we continued with the course of antibiotics to clear his body of all the bacteria that was causing the pneumonia. Treatment is always a decision that involves balancing risk and benefit, getting sicker or getting well, given the possible negative side effects of the treatment. At the same time, it was possible that the antibiotic would not work since there was no time to run a lab test for that specific bacteria. If it had not worked, he would have needed another, different antibiotic, and if that had failed, a third drug.
Today, antibiotic resistance has grown into a worldwide crisis. The World Health Organization estimates that antimicrobial resistance directly caused 1.27 million deaths and contributed to another 5 million deaths globally in 2019. In the United States alone, the CDC reports over 2.8 million antibiotic-resistant infections occur every year, leading to at least 35,000 deaths and more than 3 million cases of infection by Clostridioides difficile (C. diff) occur (CDC, 2019).
Potentially fatal diseases that have become antibiotic resistant include Staphylococcus aureus (such as methicillin-resistant Staph aureus or MRSA) and Streptococcus pneumoniae (strep), as well as Klebsiella pneumoniae, Acinetobacter baumannii, Escherichia coli, and Pseudomonas aeruginosa. These six pathogens alone were responsible for nearly 1 million deaths in 2019. Other dangerous resistant infections include multidrug-resistant tuberculosis (MDR-TB), extensively drug-resistant typhoid fever, and carbapenem-resistant Enterobacteriaceae (CRE), sometimes described as “nightmare bacteria” (Murray, et al., 2022).
Bacterial resistance develops because bacteria, like all living organisms, evolve. Antibiotics, which are typically chemicals produced by molds or other organisms, work by killing or interfering with the life cycle of specific types of bacteria. However, antibiotics are often a blunt instrument: they resemble a form of what has been referred to as carpet bombing in warfare, in which the enemy is destroyed, but the whole neighborhood is also destroyed. While antibiotics may eliminate the bacteria causing the infection, they can also damage or destroy many beneficial bacteria in the gut, on the skin, and other areas of the body.
One in five medication-related visits to the emergency room are from reactions to antibiotics (CDC, 2025). This collateral damage can disrupt the gut microbiome, weaken immunity, and create opportunities for other harmful microbes to flourish. In addition, frequent antibiotic use could possibly contribute to obesity, as evidenced by the fact that low dosages of antibiotics are often given to farm animals, not only to prevent disease, but to increase their weight. Antibiotics appear to alter the gut microbiome to make it more efficient at extracting nutrients and energy from feed (Cox, 2016).
Antibiotics have been one of the major focuses of pharmaceutical drug development; however, they can cause serious side effects and tend to become less effective over time as the bacteria develop antibiotic resistance. Many bacteria can develop antibiotic resistance in less than a 6 month time period (Poku et al., 2023). Once bacteria develop antibiotic resistance to one drug, a new antibiotic drug needs to be discovered, developed, and produced. Even the newer and stronger antibiotics rapidly loose their efficacy as the bacteria develop resistance to it. In the long term, it is a loosing battle, and a totally new approach is needed.
Bacteriophage therapy
One new approach worth closer consideration is bacteriophage therapy. In nature, bacteria and viruses have been locked in a constant evolutionary battle for billions of years. Bacteria are vulnerable to specific viruses, so a bacteriophage, or phage, refers to a virus that specifically infects and kills a particular strain of bacteria. As bacteria change to evade attack, phages evolve to counter them, maintaining an ongoing balance to some degree. The theory is that because phages are very specific and only act on one particular type of bacteria, that potentially makes them a uniquely precise form of medicine.
The challenge involves matching the phage to the pathogenic bacterium, and there are an astonishing number of different phages and bacteria. In two patients with the same symptoms or diagnosis, the causal bacteria could be a slightly different subspecies. When used clinically, bacteriophages work only against specific type of bacterium. This makes phage therapy a useful form of individualized medicine.
To be successful, the bacteria that causes the patient’s infection must first be identified. This is different from the way in which antibiotics are commonly used in primary care. When a patient develops symptoms, often an antibiotic is given before the bacteria has been identified, and if it does not work, another antibiotic is given.
In contrast, phage therapy depends on matching the specific disease-causing bacteria to a specific phage. Phage medicine requires a library of thousands of known phages as an essential prerequisite to treatment. Clinical care involves identifying the phage that can target and destroy that specific bacterium. Then the phage is cultured, purified, and administered in either a liquid preparation, capsule, ointment, intravenously or at a wound site depending on the type of infection.
Unlike antibiotics, which often damage beneficial microbes, phages only target the bacteria they evolved to destroy, leaving the rest of the human biome intact. Because viruses are capable of reproduction, once a phage reaches its bacterial host, it multiplies rapidly and produces hundreds of new phages that continue to attack the specific disease-causing bacteria as shown in Figure 1. According to reports from phage medicine, symptoms improve dramatically within 24 hours. The phages are self-limiting and their numbers naturally decline once the infection is cleared.
Figure 1. Electron micrograph of a phage attaching and injecting it viral genome into the cell and its life cycle
At present, phage therapy has already shown success against a variety of resistant infections, including methicillin-resistant Staphylococcus aureus (MRSA), Acinetobacter baumannii wound infections (a major problem in military medicine), multidrug-resistant Klebsiella pneumoniae, and even certain cases of tuberculosis. Instead of being the last line of defense, in the future this may become the first line of defense.
The initial research and clinical use has been concentrated in Russia and Eastern Europe. The United States largely abandoned phage therapy after the discovery of antibiotics. Several factors contributed to this trend.
- Funding barriers. Funding agencies in the West have not seen phage therapy as a credible option. In many cases, the review committees that decided which grant applications to approve have tended to fund research that supported their own biases and their interests in antibiotic research. As a result, research money was rarely allocated to study or develop phage therapies. Generally, high- risk, novel research ideas are almost never funded by federal agencies except DARPA which is more open to new concepts when they offer a high potential of success.
- Economic realities discourage investment. Unlike antibiotics, which can be mass-produced as a single chemical and sold at high volume for profit, phage therapy requires maintaining large, evolving phage libraries and tailoring treatments to each patient. This individualized model offered little appeal to large pharmaceutical companies seeking standardized products with a high payout.
- Development is not scalable. A specific bacteriophage must be selected for each specific pathogenic bacteria, and a large phage collection must be maintained to identify the correct phage.
- Scientific and cultural bias. American researchers have tended to dismiss work coming out of Russia and Georgia, failing to recognize the rigor and effectiveness of decades of phage therapy practiced there. Limited scientific exchange was also a factor during the Cold War. A similar bias, for example, has influenced the adoption of psychological treatment strategies developed in Russia. In the U.S., the focus was more on using instrumental learning while neglecting the power of Pavlov’s classical condition.
These scientific prejudices, financial disincentives, and geopolitical divides have meant that phage therapy was almost totally absent in Western medicine although it continued in Eastern Europe, where it has saved countless lives. Phage therapy is currently becoming recognized and desperately needed because of the increase in multi-drug-resistant infections.
Phage treatment challenges
The greatest challenge with phage therapy is that it must be individualized to the pathogen. Each patient’s infection may require a different phage, because phages are exquisitely specific to the bacterium they target. A phage that destroys one strain of E. coli, for example, may have no effect on another subspecies of E. coli. While the same phage can sometimes be used for multiple patients with the same infection, in most cases treatment must be customized to the individual patient.
This requires maintaining vast phage libraries that researchers and clinicians must be able to screen rapidly in order to find the right match. The scale of this challenge is staggering, although AI technology may be part of the solution. Scientists estimate that there are 10³¹ (ten million trillion trillion) specific phages on Earth, making them the most abundant biological entities known. Only a tiny fraction of these have been studied, and only a relatively smaller number are currently catalogued for medical use.
Specialized research institutes, particularly in Georgia, Poland, and Russia (and now in the U.S. and Europe) have developed large collections of phages that can be tested against samples of specific bacterium. Building, maintaining, and updating these libraries is labor-intensive and requires constant monitoring, since both bacteria and phages evolve. Phage therapy does not lend itself easily to large-scale commercialization. Nevertheless, phage therapy represents one of the most promising approaches to resistant infections.
Summary
Unlike antibiotics, which disrupt the human microbiome and can cause significant side effects, phages are naturally occurring, highly targeted, and generally well tolerated. Because they attack only a specific bacterium, without disturbing beneficial microbes, phages have the potential to be used not only as a treatment but also for prevention, helping to control bacterial populations before they cause disease. Harnessing this form of living medicine could mark an evolutionary shift in modern healthcare, offering a sustainable, balanced way to prevent and treat infections. Read the outstanding book by Lina Zeldovich, The Living Medicine: How a lifesaving cure was nearly lost and why it will rescue us when antibiotics fail.
References
admin. (2025, August 28). Special Episode: Lina Zeldovich & The Living Medicine. This Podcast Will Kill You. Accessed September 1, 2025. https://thispodcastwillkillyou.com/2025/08/28/special-episode-lina-zeldovich-the-living-medicine/
CDC. (2019). Antibiotic Resistance Threats in the United States, 2019. Atlanta, GA: U.S. Department of Health and Human Services, CDC. https://www.cdc.gov/antimicrobial-resistance/media/pdfs/2019-ar-threats-report-508.pdf
CDC. (2025). Do antibiotics have side effects. Atlanta, GA: U.S. Department of Health and Human Services, CDC Accessed September 5, 2025. https://www.cdc.gov/antibiotic-use/media/pdfs/Do-Antibiotics-Have-Side-Effects-508.pdf
Cox, L.M. (2016). Antibiotics shape microbiota and weight gain across the animal kingdom, Animal Frontiers, 6(3), 8–14. https://doi.org/10.2527/af.2016-0028
Garnett, C. (2019). Personal quest resurrects phage therapy in infection fight. NIH Record, LXXI(6). https://nihrecord.nih.gov/2019/03/22/personal-quest-resurrects-phage-therapy-infection-fight
Murray, C. J. L. et al. (2022). Global burden of bacterial antimicrobial resistance in 2019: a systematic analysis. The Lancet, 399(103250, 629 – 655. https://doi.org/10.1016/S0140-6736(21)02724-0
Poku, E., Cooper, K., Cantrell, A., Harnan, S., Sin, M.A., Zanuzdana, A., & Hoffmann, A. (2023). Systematic review of time lag between antibiotic use and rise of resistant pathogens among hospitalized adults in Europe. JAC Antimicrob Resist, 5(1), dlad001. https://doi.org/10.1093/jacamr/dlad001
Spinillo, A., Capuzzo, E., Acciano, S., De Santolo, A., & Zara, F. (1999). Effect of antibiotic use on the prevalence of symptomatic vulvovaginal candidiasis. Am J Obstet Gynecol, 180(1 Pt 1),14-7. https://doi.org/10.1016/s0002-9378(99)70141-9
Zeldovich, L. (2024). The Living Medicine: How a lifesaving cure was nearly lost and why it will rescue us when antibiotics fail. New York: St. Martin’s Press. https://www.amazon.com/Living-Medicine-Lifesaving-Lost_and-Antibiotics/dp/1250283388
*Created in part from the information in the book, The Living Medicine-How a lifesaving cure was nearly lost-and why it will rescue Us When Antibiotics Fail, by Linda Zeldovich and with the editorial help of ChatGPT5.